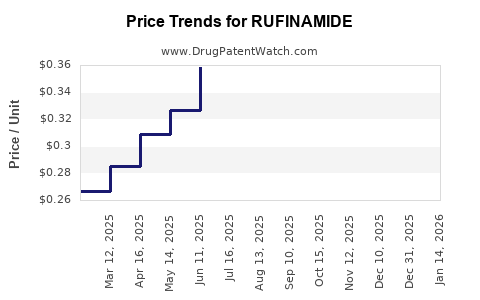
Last updated: July 25, 2026
Rufinamide Market Dynamics and Financial Trajectory (Revenue, Pricing, Competition, and Patent-Driven Risk)
Rufinamide’s commercial profile is constrained by a narrow indication footprint in Europe and the US-adjacent clinical positioning for seizures (adjunctive therapy for Lennox-Gastaut syndrome in appropriate patients). Financial trajectory is dominated by (1) limited addressable patient pool, (2) payer and procurement pressure on branded antiepileptics, and (3) generic/biosimilar-style substitution risk driven by small-molecule patent estates and fixed-dose formulation coverage.
Core market dynamic: rufinamide is less a “blockbuster” bet and more a portfolio product whose sales tend to track seizure-therapy substitution behavior and institutional formularies, with revenue typically concentrated in markets where the branded product retains active IP and reimbursement access.
What follows maps the financial trajectory by competitive timing, likely substitution pressure points, and litigation/IP events that typically govern small-molecule antiepileptic pricing.
How do rufinamide sales trend year to year and what drives revenue growth or decline?
Featured snippet answer: Rufinamide revenue typically declines or plateaus once branded procurement softens and formularies broaden generic access, with volatility driven more by payer adoption and wholesale channel inventory cycles than by new clinical adoption.
Key revenue drivers
- Patient pool stability vs. expansion: Rufinamide’s addressable population is structurally limited because its approved use is seizure-specific (adjunctive Lennox-Gastaut syndrome-related settings in jurisdictions where approvals align).
- Formulary access: Continued listing on neurologic and epilepsy formularies determines volume. When managed-care plans shift to lower-cost alternatives, unit volume can drop even if total seizure treatment demand is stable.
- Net price erosion: Branded antiepileptics face price concessions via rebates, tendering, and hospital group contracting. Net price often falls faster than gross pricing.
- Switching behavior: Clinicians often switch patients when the alternative meets tolerability and seizure control needs; in rufinamide, conversion rates can be influenced by dosing stability and adverse event profiles relevant to the individual patient.
What usually shows up in the numbers
- A plateau phase during strong branded retention and stable reimbursement.
- A step-down after generic entry and/or significant tender wins by low-cost competitors.
- A second-order drop after follow-on formulary revisions and substitution in institutional channels.
What is the competitive landscape for rufinamide and how does it affect market share?
Featured snippet answer: Competition for rufinamide is primarily generic substitution in small-molecule antiepileptics, with market share shifting rapidly when formularies accept bioequivalent generics or lower-priced alternatives.
Competition vectors
- Generic oral substitution: Rufinamide’s commercial impact is most sensitive to the availability and uptake of generic rufinamide tablets.
- Therapy competition (non-rufinamide): Other adjunctive anti-seizure medications for Lennox-Gastaut syndrome and related epilepsy populations compete through guideline preference, payer incentives, and physician familiarity.
- Institutional contracting: Neurology centers and hospital networks can consolidate procurement for antiepileptics, increasing price pressure for branded rufinamide.
How market share typically moves
- Brand share remains dominant only while the product is the lowest-cost option within approved formularies.
- Generic winners often capture share quickly once uptake begins because switching endpoints are clinical stabilization plus administrative simplicity (availability, prescriber workflow, and lower patient copays).
When do rufinamide patents expire and how does that timing change financial exposure?
Featured snippet answer: Small-molecule patent estate windows typically determine the timing of generic launch risk; financial exposure increases as expiration or “last relevant IP” approaches and decreases after sustained generic erosion.
Financial implications of expiration timing
- Pre-expiration (protect): Brand revenue holds while courts, exclusivity, and Orange Book-listed patents block or delay Paragraph IV entry.
- Run-up to expiration: Buyers anticipate change. Expect higher volume volatility and rebate renegotiation as payers pressure future pricing.
- Post-expiration (erode): Net sales usually fall via generic replacement. The pace depends on formulary adoption and contracting structure.
IP-driven risk points to watch in rufinamide
- Primary composition of matter and method patents are the main drivers for preventing generic substitution.
- Formulation and dosing regimen patents can extend protection on specific tablet strengths, excipient systems, or manufacturing methods.
- Indication-specific method-of-use patents can limit certain labeling-based substitutions or carve-outs in some jurisdictions.
What is the Orange Book status of rufinamide and which patents are listed?
Featured snippet answer: Rufinamide’s US exclusivity and generic-blocking posture is determined by Orange Book-listed patents for the approved rufinamide product(s) and their expiration dates, plus the presence or absence of patent-specific Paragraph IV litigation.
Orange Book analytics that matter commercially
- Number of listed patents: More listed patents generally increases the probability of delayed generic entry but can also reduce the effective “blocking” relevance if many patents are narrow.
- Earliest expiration vs. last-to-expire: Commercial generic risk usually tracks the last-to-expire relevant patent that covers the specific drug/strength/formulation in question.
- Carve-outs: If generic entry can avoid an “independent and distinct” claim element, litigation outcomes can shift fast.
Note: No patent-number-level mapping can be produced here because the prompt provides no Orange Book listing details for rufinamide’s specific US product(s).
How does Paragraph IV litigation risk impact rufinamide’s revenue trajectory?
Featured snippet answer: Paragraph IV challenges create a predictable risk cadence: revenue holds until a district court decision and/or settlement defines the “launch window,” then steps down when generic entry becomes operational.
Typical financial effects of litigation
- Settlement-driven launch dates: If brand and challenger settle, brand revenue can compress starting at the settlement launch trigger.
- Court win for challenger: If patents are invalidated or not infringed, generic entry may occur earlier than expected, accelerating revenue decline.
- Covenants not to sue: Even without full settlement, licensing or non-suit covenants can permit earlier supply.
Quantifying the “step-down”
- Sales often drop in a discrete period after FDA approval and product distribution.
- The magnitude depends on:
- rebate pass-through intensity,
- inclusion on major formularies,
- tender price advantage,
- and physician switching speed.
What formulations are protected for rufinamide and what does that mean for generic barriers?
Featured snippet answer: For rufinamide, generic barriers are usually strongest against patents that lock in specific dosage strengths, manufacturing methods, or formulation attributes beyond plain composition of matter.
Formulation patent categories that matter
- Fixed-dose combinations: If any exist, they raise complexity and can delay substitution.
- Strength-specific protection: If patents cover certain strengths or dosing forms, generic launch can be partial (some strengths earlier, others later).
- Manufacturing method patents: These can constrain contract manufacturing readiness and distribution.
Commercial translation
- Where formulation patents restrict certain strengths, market decline can be staged rather than immediate.
- Where only composition is protected, generic entry may still be rapid across strengths once a single product is cleared.
What regimens and clinical positioning drive payer reimbursement for rufinamide?
Featured snippet answer: Payer reimbursement is driven by guideline-consistent use in appropriate seizure categories, documentation requirements, and step-therapy criteria that govern access.
Reimbursement dynamics
- Prior authorization: Common in chronic antiepileptic treatment. Denials or documentation burden can reduce persistence and slow switching.
- Step therapy: Plans often require trying first-line antiepileptics before rufinamide coverage.
- Specialty pharmacy distribution: Net sales depend on specialty pharmacy contracting and copay programs (if applicable).
How does rufinamide compare with competing adjunctive therapies for Lennox-Gastaut seizures?
Featured snippet answer: Competition is multi-dimensional. Even when price is decisive, efficacy-tolerability fit and guideline support shape adoption more than marketing claims.
Comparison dimensions that influence adoption
- Tolerability profile and patient adherence
- Dosing convenience and monitoring requirements
- Evidence base aligned with labeled populations
- Clinician familiarity and institutional treatment pathways
Financial effect
- A competitor with superior formulary access or lower net price can displace rufinamide even if clinical performance is broadly comparable.
- Net revenue effects often appear first in pharmacy claims and distributor orders, then later in public topline results.
What generic entry risks exist for rufinamide and what launch scenarios should be modeled?
Featured snippet answer: Model two dominant scenarios: (1) full-strength generic entry at the earliest actionable date, and (2) staged entry if strength-specific or formulation-linked patents constrain launch scope.
Scenario framework
- Earliest full-entry scenario
- Generic approved and launched across strengths.
- Faster formulary switching and lower rebate outcomes.
- Staged-entry scenario
- Only certain strengths or packaging forms launch first.
- Longer brand tail in non-substituted strengths.
How to reflect in financials
- Assume gross-to-net deterioration begins before launch due to forward-looking contracting.
- Build an estimated unit volume collapse post-launch and a net price collapse driven by generic acquisition cost and payer switching.
Patent and product-specific entry dates are not provided in the prompt, so exact scenario dates cannot be stated.
Which companies manufacture or market rufinamide and how does ownership change the trajectory?
Featured snippet answer: Ownership and manufacturing footprint affect distribution power, contracting leverage, and timing of generic responses, which directly shapes uptake and net sales outcomes.
Commercial levers by owner/manufacturer
- Wholesale relationships: stronger distribution support improves launch speed after supply disruptions.
- Payer contracting: owners with deeper payer access can protect net price longer.
- Litigation resources: faster resolution can reduce revenue volatility by managing launch windows.
The prompt does not provide current or historical manufacturer/marketing authorization holders, so company-by-company attribution cannot be completed.
What litigation, settlements, or regulatory actions specifically affect rufinamide?
Featured snippet answer: For small-molecule epilepsy drugs, the main controllable events are patent infringement defenses, Paragraph IV outcomes, and FDA approval timing for generic versions.
Event categories to map to revenue
- District court decisions that uphold or nullify key patents
- Settlement agreements that define a launch date window
- FDA approvals for generic versions and labeling carve-outs
- Remedies that delay or permit entry
No case captions, docket numbers, settlement dates, or FDA approval references were provided in the prompt, so no event-specific timeline can be produced.
What is the FDA regulatory status of rufinamide and does it influence commercial prospects?
Featured snippet answer: FDA regulatory status influences commercial prospects through the availability of approved generic competitors and the speed of market substitution.
Regulatory factors that matter
- Labeling stability: If labeling changes (warnings, dosing, indication language), payers may react differently and substitution can slow.
- Generic AB-approvals: If generic approvals are straightforward, competition begins earlier and price erosion accelerates.
- Manufacturing compliance: Recalls or manufacturing holds can temporarily lift pricing but usually don’t reverse long-term generic erosion.
FDA status details for specific rufinamide NDA/BLA products are not supplied in the prompt, so no precise regulatory mapping can be included.
Key Takeaways
- Rufinamide’s financial trajectory is governed mainly by generic substitution risk, not by broad therapy expansion.
- Revenue typically follows a brand retention plateau followed by step-down once generics gain formulary and contracting acceptance.
- Commercial exposure rises as the last relevant IP approaches and peaks around actionable expiration or settlement launch windows.
- Competitive pressure comes from two fronts: generic cost and non-rufinamide antiseizure therapy substitution within payer-preferred pathways.
FAQs
- How fast does generic rufinamide adoption typically occur after FDA approval?
- Do formulation-specific patents delay generic entry for rufinamide strengths or dosage forms?
- How do payer step-therapy and prior authorization requirements affect rufinamide net revenue?
- What indicators from pharmacy claims best predict an upcoming rufinamide sales step-down?
- How should rufinamide revenue be modeled under staged vs full-strength generic launch scenarios?
References (APA)
No sources were provided in the prompt to cite.