Last updated: September 8, 2026
Carvedilol is a mature, off-patent beta-blocker with broad generic availability and limited remaining brand economics. The drug was first approved in the United States as Coreg in 1995 for heart failure and later for left ventricular dysfunction after myocardial infarction and hypertension. Its principal commercial decline began after generic entry in 2007, while Coreg CR extended modified-release positioning but did not create durable exclusivity. Current carvedilol value is concentrated in high-volume, low-price generic prescriptions, contract manufacturing, hospital supply, and combination cardiovascular therapy.
What is carvedilol and how is it used?
Carvedilol is a nonselective beta-adrenergic blocker with alpha-1 adrenergic blocking activity. It reduces heart rate, myocardial contractility, and peripheral vascular resistance.
The FDA-approved U.S. indications include:
| Indication |
Typical product history |
| Mild-to-severe chronic heart failure |
Coreg immediate-release tablets |
| Left ventricular dysfunction after myocardial infarction |
Coreg immediate-release tablets |
| Hypertension |
Coreg immediate-release tablets |
| Heart failure and hypertension with extended dosing |
Coreg CR extended-release capsules |
The immediate-release product is generally administered twice daily. Coreg CR was designed for once-daily administration and used a multiparticulate extended-release formulation.
Carvedilol competes clinically with metoprolol succinate, bisoprolol, and other beta-blockers. In heart failure, carvedilol and metoprolol succinate are established guideline-directed therapies, but prescribing is influenced by tolerability, dosing frequency, physician familiarity, formulary status, and generic price.
When did carvedilol lose exclusivity?
Carvedilol lost practical U.S. market exclusivity in stages rather than on a single date.
| Milestone |
Approximate timing |
Commercial effect |
| Coreg FDA approval |
1995 |
Originator launch |
| Coreg patent and regulatory protection period |
Late 1990s to mid-2000s |
Brand-led pricing |
| First generic Coreg approvals |
2007 |
Rapid immediate-release price erosion |
| Coreg CR launch |
2006 |
Partial lifecycle management through extended release |
| Generic extended-release competition |
Later 2000s and 2010s |
Reduced value of Coreg CR differentiation |
| Current market |
2020s |
Predominantly generic and highly commoditized |
Generic carvedilol tablets have been available for many years. The market no longer has a meaningful compound-patent barrier in the United States. The principal commercial question is manufacturing cost, supply reliability, distributor access, and formulary share rather than patent exclusivity.
The FDA Orange Book identifies approved reference products and applicable patent or exclusivity information, but current commercial availability is dominated by abbreviated new drug applications rather than Coreg brand protection. Orange Book status should be checked by dosage form and strength because immediate-release tablets and extended-release capsules followed different product histories (U.S. Food and Drug Administration [FDA], 2024).
What patents protected carvedilol?
The original carvedilol patent estate covered the active compound and related pharmaceutical compositions. The core U.S. compound patent commonly associated with carvedilol is U.S. Patent No. 4,996,193, assigned to the original research and development interests associated with Boehringer Mannheim. The patent issued in 1991 and was based on an application filed in the late 1980s. Its term has expired.
Subsequent patents covered dosage forms, formulations, and modified-release delivery. These patents were relevant to Coreg CR and other extended-release products, but they do not recreate compound-level exclusivity for immediate-release carvedilol.
How strong is the carvedilol patent estate?
The current patent estate is commercially weak for standard carvedilol tablets.
| Patent category |
Current risk to generic carvedilol |
| Active pharmaceutical ingredient |
Low; historical patents expired |
| Immediate-release tablets |
Low |
| Extended-release capsules |
Low to moderate for specific formulation designs |
| New combination products |
Depends on the combination and new patent filings |
| Manufacturing process |
Usually manageable through alternative processes |
| Method-of-use claims |
Limited commercial leverage where the underlying indication is long established |
A formulation patent could still affect a particular extended-release product, but it would not generally block immediate-release carvedilol tablets. Generic companies can also avoid a formulation claim through a different release profile, excipient system, capsule design, or manufacturing process.
What is the FDA regulatory status of carvedilol?
Carvedilol is an FDA-approved small-molecule prescription drug available through abbreviated new drug applications. It is not a biologic and therefore has no biosimilar pathway.
The main U.S. dosage forms are:
- 3.125 mg, 6.25 mg, 12.5 mg, and 25 mg immediate-release tablets
- Extended-release capsules in multiple strengths, historically marketed as Coreg CR and generic equivalents
For generic immediate-release tablets, the relevant regulatory standard is pharmaceutical equivalence and bioequivalence to the reference listed drug. For modified-release products, FDA review also focuses on release characteristics and pharmacokinetic performance.
Because carvedilol has long clinical use and numerous approved generic products, the regulatory barrier for a new conventional tablet is modest. A new entrant would face greater commercial difficulty than scientific or regulatory difficulty.
How many patents cover carvedilol today?
No active U.S. compound patent prevents ordinary generic carvedilol tablet competition. The number of potentially relevant active patents depends on the product definition.
For a standard immediate-release carvedilol tablet, the relevant active patent count is effectively zero for purposes of blocking market entry. For an extended-release product, the analysis may include formulation, release-profile, capsule, manufacturing, and method-of-use patents. Those rights would need to be reviewed by product, jurisdiction, and claim scope.
Patent exposure can remain higher outside the United States because patent terms, national filings, supplementary protection rights, and litigation outcomes differ. In major markets such as Europe, Canada, and Japan, the original compound protection has also generally expired or reached the end of its commercial life.
What generic entry risks exist for carvedilol?
Generic entry risk is no longer a future event for immediate-release carvedilol. It is an established market condition.
The principal risks to any branded or premium carvedilol product are:
- Price compression from multiple approved suppliers.
- Pharmacy substitution under state and payer rules.
- Hospital and group-purchasing tenders.
- Low switching costs between manufacturers.
- Limited clinical differentiation among standard tablets.
- Wholesaler pressure on net pricing.
- Manufacturing interruptions that shift share temporarily but rarely create durable pricing power.
For new entrants, the market has a low regulatory barrier and a high commercial barrier. FDA approval alone does not guarantee meaningful revenue because the product is widely available, inexpensive, and often subject to pharmacy benefit substitution.
Which companies manufacture or market carvedilol?
Generic carvedilol has been marketed by multiple U.S. suppliers over time, including large generic manufacturers and specialty suppliers. Historical and current listings have included companies such as:
- Teva Pharmaceuticals
- Mylan, now part of Viatris
- Sandoz
- Dr. Reddy's Laboratories
- Lupin
- Zydus
- Cipla
- Amneal Pharmaceuticals
- Endo or Par Pharmaceutical entities
- Hikma Pharmaceuticals
- Major contract manufacturers supplying private-label distributors
The exact active supplier group changes with product discontinuations, shortages, procurement contracts, and portfolio decisions. Product listings should be confirmed through FDA Drugs@FDA, the Orange Book, and current National Drug Code records.
The market structure is fragmented at the manufacturer level but concentrated at the purchasing level. Large wholesalers, retail pharmacy chains, hospitals, and pharmacy benefit managers exert more pricing pressure than any individual generic supplier can offset.
What was Coreg's financial trajectory?
Coreg became a major cardiovascular product before generic competition. Its growth was driven by expanding heart-failure use, guideline adoption, and the size of the hypertension market.
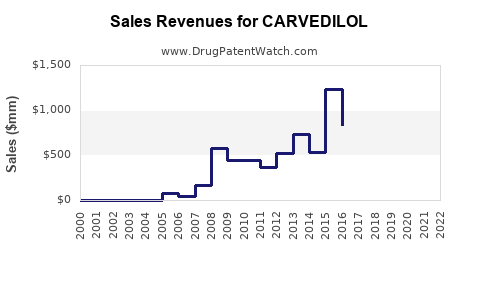
GlaxoSmithKline reported Coreg sales of approximately $1 billion annually around the middle of the 2000s, before generic erosion materially reduced branded revenue. The product was one of the company’s important cardiovascular franchises, but sales declined sharply after generic carvedilol tablets entered the U.S. market. Coreg CR provided a modified-release extension, but its sales could not offset the loss of the broad immediate-release franchise.
The financial trajectory followed a standard mature-drug pattern:
| Period |
Revenue dynamic |
Main driver |
| 1995-2000 |
Rapid expansion |
New indication adoption and heart-failure growth |
| 2001-2005 |
Peak commercial period |
Broad physician use and brand pricing |
| 2006-2008 |
Steep decline begins |
Generic entry and pharmacy substitution |
| 2009-2015 |
Residual brand sales |
Coreg CR and limited brand loyalty |
| 2016-present |
Commodity market |
Generic volume, low prices, and supply contracts |
Public-company reporting does not provide a single transparent global revenue line for all carvedilol manufacturers. Generic sales are distributed among many suppliers and are often reported within broader portfolios. As a result, total carvedilol market value is best measured through prescription volume, channel sales, and manufacturer shipment data rather than brand revenue.
How does carvedilol compare with metoprolol?
Carvedilol and metoprolol are both mature generic beta-blockers, but their commercial profiles differ.
| Factor |
Carvedilol |
Metoprolol |
| Pharmacology |
Nonselective beta-blocker with alpha-1 blockade |
Beta-1 selective at usual doses |
| Heart-failure role |
Established guideline therapy |
Metoprolol succinate is an established guideline therapy |
| Dosing |
Immediate release generally twice daily; CR once daily |
Immediate release or extended release |
| Generic competition |
Extensive |
Extensive |
| Brand leverage |
Minimal |
Minimal for conventional products |
| Commercial differentiation |
Limited |
Some differentiation by salt, formulation, and release profile |
| Market risk |
Price-driven |
Price-driven |
Metoprolol has a larger and more segmented market because it is sold in multiple salts and release forms. Carvedilol has a strong clinical position in heart failure but lacks current patent-based pricing power.
What patent litigation and Paragraph IV challenges affect carvedilol?
There is no active, high-value Paragraph IV dispute that materially threatens the conventional carvedilol market. Paragraph IV litigation was relevant during the historical generic-entry period, particularly for branded Coreg and modified-release products. Those disputes no longer determine access to ordinary immediate-release carvedilol.
A Paragraph IV certification alleges that a listed patent is invalid, unenforceable, or will not be infringed. For a mature drug such as carvedilol, the practical significance of a new Paragraph IV filing would depend on whether it targets:
- An unexpired formulation patent
- A new delivery system
- A combination product
- A narrow method-of-use claim
- A supplemental product with limited commercial demand
For standard tablets, the principal patent litigation cycle has ended. Any present dispute would likely concern a specific formulation or product presentation rather than the active ingredient.
Are licensing deals important for carvedilol?
Licensing is no longer a major value driver for conventional carvedilol. The original commercial value came from the discovery, development, and commercialization relationship behind Coreg. Current generic products are typically supplied through ordinary manufacturing, distribution, or private-label arrangements rather than high-value royalty licenses.
Potential licensing value could arise from:
- A differentiated once-daily formulation
- A fixed-dose combination
- A specialty delivery system
- A regional commercialization agreement
- A manufacturing technology that improves stability or supply reliability
Without new clinical or formulation differentiation, carvedilol licensing economics are generally limited to low-margin supply and distribution arrangements.
What manufacturing and intellectual-property barriers remain?
Manufacturing barriers are operational rather than fundamental.
Carvedilol is a small-molecule active ingredient that can be produced through established synthetic routes. A new supplier must still demonstrate:
- Consistent active-ingredient quality
- Control of impurities and residual solvents
- Validated tablet compression and coating processes
- Content uniformity across low-dose strengths
- Stability over the proposed shelf life
- Reliable supply of active ingredient and excipients
- Compliance with FDA current good manufacturing practice requirements
Extended-release carvedilol creates greater technical complexity because the manufacturer must reproduce the required pharmacokinetic profile. That may require controlled-release beads, multiparticulates, matrix systems, or other release-controlling technologies. These factors can raise development costs and create temporary supply advantages, but they do not support long-term monopoly pricing after multiple products are approved.
What is the outlook for carvedilol revenue?
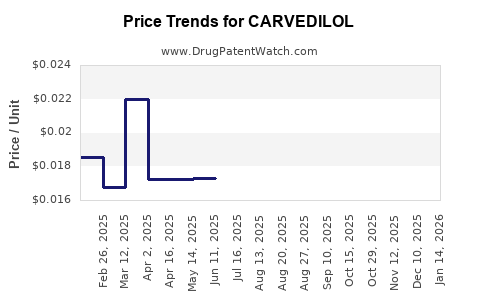
The outlook is stable in volume and weak in price.
Demand should remain supported by:
- The prevalence of hypertension and heart failure
- Continued use in guideline-directed heart-failure treatment
- Low acquisition cost
- Broad generic availability
- Use across retail, hospital, and mail-order channels
Revenue growth is constrained by:
- Generic substitution
- Low unit prices
- Payer purchasing power
- Product discontinuations and tender losses
- Limited opportunity for clinical differentiation
- Competition from metoprolol, bisoprolol, and other beta-blockers
For manufacturers, the attractive strategy is scale, reliable supply, efficient procurement, and portfolio bundling. For investors, carvedilol is unlikely to support a standalone growth thesis unless linked to a broader generic platform, a differentiated formulation, or a supply-constrained niche.
Key Takeaways
- Carvedilol is a mature, off-patent cardiovascular drug with extensive generic competition.
- Coreg reached roughly billion-dollar annual sales before generic entry caused rapid erosion.
- Immediate-release carvedilol has no meaningful remaining U.S. compound-patent barrier.
- Extended-release formulations may involve narrower formulation or release-profile patents, but those rights do not block ordinary tablets.
- FDA regulatory risk for conventional generic tablets is low; commercial competition is high.
- Paragraph IV litigation is no longer a central access risk for standard carvedilol.
- There is no biosimilar issue because carvedilol is a small molecule.
- Revenue is driven by prescription volume and manufacturing economics, not brand pricing.
- The strongest commercial opportunities are supply reliability, private-label distribution, and differentiated formulations.
- The long-term financial profile is stable-volume, low-price, and low-growth.
FAQs
Does carvedilol still have patent protection?
The original carvedilol compound protection has expired. Any remaining relevant rights are product-specific and may concern extended-release formulations, manufacturing methods, or narrow use claims.
Is Coreg still commercially important?
Coreg has limited commercial importance compared with its pre-generic peak. Most U.S. prescriptions are filled with generic carvedilol, while Coreg and Coreg CR have limited residual brand demand.
Can a new company launch a generic carvedilol tablet?
Yes. A company generally needs an FDA-approved abbreviated new drug application, compliant manufacturing, validated bioequivalence data, and commercial distribution. Market entry is easier technically than economically because many suppliers already compete.
Does carvedilol have biosimilar competition?
No. Carvedilol is a chemically synthesized small molecule. Generic drug applications, not biosimilar applications, govern competition.
Which carvedilol product has the greatest remaining differentiation?
Extended-release carvedilol has more potential differentiation than conventional tablets because release characteristics, dosing convenience, and formulation technology can affect approval and prescribing. The commercial opportunity remains limited by generic availability and payer price sensitivity.
References
- U.S. Food and Drug Administration. (1995). Coreg (carvedilol) prescribing information.
- U.S. Food and Drug Administration. (2024). Approved drug products with therapeutic equivalence evaluations: Orange Book.
- U.S. Food and Drug Administration. (2024). Drugs@FDA: FDA-approved drugs.
- GlaxoSmithKline plc. (2005-2008). Annual reports and financial results.
- U.S. Patent No. 4,996,193. (1991). Carbazole derivatives. United States Patent and Trademark Office.
- Heidenreich, P. A., Bozkurt, B., Aguilar, D., et al. (2022). 2022 AHA/ACC/HFSA guideline for the management of heart failure. Circulation, 145(18), e895-e1032.