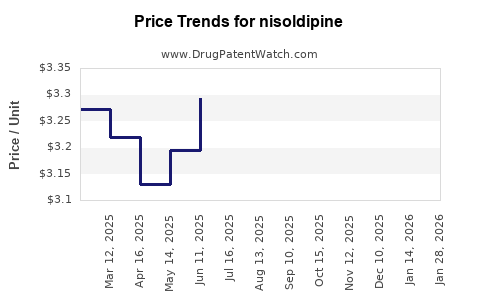
Last updated: September 7, 2026
Nisoldipine is a long-acting dihydropyridine calcium-channel blocker marketed in the United States under the Sular brand and as extended-release generic tablets. Its commercial trajectory is mature and declining: FDA approval dates to 1995, branded commercial differentiation has largely disappeared, and current value is concentrated in low-priced generic supply rather than proprietary innovation. No publicly reported company provides standalone revenue for nisoldipine.
What is nisoldipine used for?
Nisoldipine is an extended-release dihydropyridine calcium-channel blocker indicated for the treatment of hypertension. It reduces vascular smooth-muscle contraction by inhibiting calcium influx into arterial smooth muscle. The drug is administered once daily in extended-release tablet form.[1]
Nisoldipine competes pharmacologically with amlodipine, felodipine, nifedipine extended release, and other calcium-channel blockers. Amlodipine has become the dominant commercial comparator because of broad generic availability, extensive guideline use, long half-life, and low cost.
Key product characteristics
| Attribute |
Nisoldipine |
| Active ingredient |
Nisoldipine |
| Drug class |
Dihydropyridine calcium-channel blocker |
| U.S. brand |
Sular |
| Dosage form |
Extended-release tablet |
| U.S. strengths historically marketed |
8.5 mg, 17 mg, 25.5 mg, 34 mg |
| Primary indication |
Hypertension |
| FDA approval |
1995 |
| Administration |
Once daily |
| Regulatory pathway |
New Drug Application, NDA 019856 |
| Current commercial position |
Mature generic product with limited branded differentiation |
The extended-release formulation was commercially important because immediate-release calcium-channel blockers can produce greater peak-to-trough variability. Nisoldipine’s clinical and commercial value, however, was not sufficient to maintain a durable premium once competing calcium-channel blockers became widely generic.
When did nisoldipine lose exclusivity?
Nisoldipine lost meaningful U.S. market exclusivity after the expiration of the patents and regulatory protections associated with the original Sular product. The original approval dates to 1995, placing the product’s initial U.S. exclusivity period well behind the current market period.[1]
The principal commercial consequence was generic substitution. Once extended-release nisoldipine became available from multiple manufacturers, pharmacies and payers had limited incentive to preserve a premium-priced branded product.
Exclusivity timeline
| Period |
Market event |
Commercial effect |
| 1995 |
FDA approval of Sular extended-release nisoldipine |
Entry of a branded once-daily antihypertensive |
| Late 1990s to 2000s |
Expansion of generic calcium-channel blocker competition |
Reduced differentiation against amlodipine and felodipine |
| Post-exclusivity period |
Generic nisoldipine supply develops |
Pricing pressure and reduced branded value |
| 2010s onward |
Mature generic market and reduced promotional support |
Lower commercial visibility |
| Current market |
Limited standalone branded economics |
Revenue concentrated in commodity generic sales |
The exact original patent-family expiration dates should be distinguished from the commercial loss of exclusivity. Patent expiration may occur on different dates for active ingredient, formulation, manufacturing, or method-of-use claims. For nisoldipine, the practical commercial barrier has been absent for many years.
What is the Orange Book status of nisoldipine?
The FDA Orange Book historically listed Sular under NDA 019856 and identified the product as an extended-release nisoldipine tablet.[2] The Orange Book is the relevant source for approved multisource products, therapeutic-equivalence ratings, and any patents or exclusivity associated with an NDA.
The commercial importance of Orange Book-listed patents is now limited because nisoldipine’s original branded exclusivity period has passed. Generic applicants entering after the relevant patent term could rely on an abbreviated new drug application, subject to FDA requirements for pharmaceutical equivalence, bioequivalence, manufacturing quality, and labeling.
Regulatory status
Nisoldipine is not a biologic. Biosimilar analysis therefore does not apply. The relevant competitive pathway is the ANDA process for generic drugs.
For an ANDA applicant, the principal regulatory issues are:
- Demonstrating bioequivalence to the reference extended-release product.
- Matching the release profile of the extended-release dosage form.
- Controlling dissolution performance across the labeled strengths.
- Establishing manufacturing consistency.
- Addressing food-effect and drug-interaction considerations.
- Using an appropriate patent certification under the Hatch-Waxman framework.
The regulatory risk is lower than for a new molecular entity but can be higher than for a simple immediate-release tablet because modified-release products require more complex dissolution and pharmacokinetic control.
What patents protect nisoldipine formulations?
The commercially relevant intellectual-property protection historically centered on the extended-release formulation and product delivery profile rather than on an enduring new chemical entity monopoly.
Formulation and manufacturing barriers
Nisoldipine has limited aqueous solubility and is subject to metabolism through CYP3A pathways. Those properties create formulation considerations involving:
- Controlled release over a 24-hour dosing interval.
- Uniform drug distribution within the tablet.
- Dissolution control.
- Exposure variability caused by food or metabolic interactions.
- Stability and manufacturing reproducibility.
Those technical issues can support formulation patents or regulatory filing protections. They do not necessarily create a durable commercial moat after the core formulation patents expire.
Publicly available FDA labeling identifies the product, dosage form, strengths, contraindications, warnings, and pharmacokinetic properties, but the label is not a complete patent-family record.[1] The FDA Orange Book is the appropriate source for listed patents attached to the approved reference product.[2] No active, commercially material U.S. patent barrier is apparent from the mature generic availability of nisoldipine.
Method-of-use patents
Nisoldipine’s primary approved use is hypertension. Method-of-use patent risk is limited because:
- Hypertension is a broad and well-established indication.
- The drug has been marketed for decades.
- Generic labeling can be carved out where a valid patented method remains.
- Physicians may prescribe the drug for non-patented uses under ordinary medical practice, subject to applicable law.
No method-of-use patent appears to create a current market-wide barrier comparable to those affecting newer cardiovascular drugs.
How many patents cover nisoldipine?
The answer depends on whether the count includes expired composition-of-matter patents, formulation patents, foreign equivalents, continuations, and patents unrelated to the currently marketed dosage form.
For current U.S. commercial analysis, the relevant conclusion is that no known active patent portfolio materially prevents generic nisoldipine supply. Historical patent families may cover the active ingredient, pharmaceutical compositions, extended-release formulations, or manufacturing processes, but expired patent families do not support present-day exclusivity.
A patent count without family consolidation would overstate the strength of the estate because the same invention may appear in multiple national filings, continuations, divisionals, and abandoned applications.
Which companies are challenging nisoldipine exclusivity?
The competitive challenge to Sular came primarily through generic substitution rather than through a high-profile, publicly litigated Paragraph IV campaign.
Generic drug companies that have historically supplied cardiovascular products include Mylan, Teva, Glenmark, and other manufacturers. Product availability can vary by year, dosage strength, supplier, wholesaler inventory, and FDA approval status.
No major current Paragraph IV litigation or settlement materially changes the nisoldipine market outlook. The key competitive event was the transition from branded supply to generic supply after the relevant exclusivity period.
Paragraph IV risk
A Paragraph IV certification states that a listed patent is invalid, unenforceable, or will not be infringed by the proposed generic product. For a mature product such as nisoldipine, the commercial value of a Paragraph IV challenge is usually limited because:
- The branded market may already be small.
- Multiple generic competitors can enter after the relevant barriers expire.
- A 180-day exclusivity award may have modest value in a low-demand market.
- Litigation costs can exceed expected product profits.
- Pharmacies and payers may already treat the molecule as a commodity.
What is the financial trajectory of nisoldipine?
Nisoldipine has moved through four commercial phases: branded launch, mature branded competition, generic erosion, and low-value maintenance supply.
Financial trajectory
| Phase |
Revenue profile |
Main value driver |
| Launch and early commercialization |
Higher unit prices with limited competition |
Brand promotion and physician adoption |
| Mature branded period |
Slower growth and therapeutic substitution |
Existing prescribing base |
| Generic entry |
Sharp price and share erosion |
Manufacturing scale and distribution |
| Current mature market |
Low unit economics and limited total market value |
Supply reliability and procurement access |
No major pharmaceutical company reports nisoldipine revenue as a separate line item in public annual reports. Revenue is generally aggregated within broader cardiovascular, established-products, or generic portfolios. As a result, product-specific revenue, gross margin, and market share cannot be inferred reliably from company filings.
Revenue exposure
Nisoldipine is unlikely to represent material revenue exposure for a diversified pharmaceutical company. The product lacks:
- Patent-protected pricing.
- A large branded sales force.
- Strong current differentiation versus amlodipine.
- A major indication expansion program.
- A specialty distribution model.
- A biologic or complex-device barrier.
For generic manufacturers, the product can still produce incremental revenue if supply is constrained or if a manufacturer has an approved strength with limited competition. That opportunity is typically tactical rather than strategic.
How does nisoldipine compare with amlodipine and felodipine?
| Factor |
Nisoldipine |
Amlodipine |
Felodipine |
| Class |
Dihydropyridine calcium-channel blocker |
Dihydropyridine calcium-channel blocker |
Dihydropyridine calcium-channel blocker |
| Dosage form emphasis |
Extended release |
Immediate release with long half-life |
Extended release |
| Generic competition |
Mature |
Very mature and extensive |
Mature |
| Market visibility |
Low |
High |
Moderate to low |
| Pricing power |
Minimal |
Minimal |
Minimal |
| Differentiation |
Formulation and historical brand positioning |
Long half-life, broad use, guideline familiarity |
Extended-release profile |
| Commercial outlook |
Stable low-value niche |
Large commodity market |
Small mature market |
Amlodipine has the strongest competitive position because it became a standard first-line antihypertensive and is available from many generic suppliers. Nisoldipine’s extended-release profile does not create enough differentiation to offset the scale, familiarity, and low cost of amlodipine.
What generic launch scenarios exist for nisoldipine?
The primary generic scenarios are:
- Stable multi-source supply with low prices. This is the baseline scenario when several manufacturers remain active.
- Temporary shortage or supplier withdrawal. A manufacturing disruption can create short-lived pricing improvement for remaining suppliers.
- Strength-specific scarcity. Some dosage strengths may have fewer suppliers, creating uneven availability.
- Brand discontinuation with continued generic access. The branded product may disappear while generic tablets remain available.
- Further market contraction. Low demand can cause manufacturers to discontinue less profitable strengths.
Generic launch risk to any residual branded product is high because the active ingredient and therapeutic category are mature. A new entrant would face technical formulation requirements but limited patent exposure.
What patent litigation and settlement agreements affect nisoldipine?
Nisoldipine does not have a current litigation profile comparable to high-value branded drugs with active composition-of-matter or formulation patents. No prominent pending settlement agreement appears to define the present market structure.
Historical litigation, if any, would need to be evaluated by patent number, court docket, filing date, asserted claims, and settlement terms. Generic entry after expiry or absence of enforceable Orange Book patents generally reduces the economic value of later litigation.
The lack of material current litigation reflects the product’s economics. A small, mature antihypertensive market provides limited incentive for expensive patent enforcement unless a defendant threatens a meaningful branded revenue stream.
How strong is the nisoldipine patent estate?
The current patent estate is weak from a commercial perspective.
| Patent-estate factor |
Assessment |
| Active composition-of-matter protection |
Not commercially relevant |
| Active formulation protection |
No known market-wide barrier |
| Method-of-use protection |
Limited practical impact |
| Orange Book leverage |
Historical rather than current |
| Generic entry risk |
High |
| Biosimilar risk |
Not applicable |
| Manufacturing barrier |
Moderate technical complexity, low legal exclusivity |
| Litigation leverage |
Low |
| Long-term pricing power |
Minimal |
The formulation still requires manufacturing competence, but technical complexity is not equivalent to patent strength. A generic manufacturer may face development and quality-control requirements without facing a legally enforceable monopoly.
What is the geographic coverage of nisoldipine protection?
Nisoldipine’s commercial history is primarily associated with the United States and other mature pharmaceutical markets. Patent protection, regulatory approvals, and generic availability differ by country.
In the United States, the key regulatory framework is the NDA and ANDA system. In Europe and other jurisdictions, protection depends on national or regional patent filings, supplementary protection certificates where applicable, local marketing authorizations, and national substitution policies.
Because the core product is old, geographic differences are more likely to affect product availability, reimbursement, and supplier participation than to create substantial new patent value.
Key Takeaways
- Nisoldipine is a mature extended-release antihypertensive approved by the FDA in 1995.
- Sular is the historical U.S. brand; commercial value has shifted to generic supply.
- The product’s meaningful exclusivity period has ended.
- No current patent barrier appears to prevent generic competition.
- Formulation complexity remains a manufacturing issue but does not create a durable commercial moat.
- Amlodipine is the stronger commercial comparator because of broader use, greater familiarity, and extensive generic availability.
- Nisoldipine has limited standalone revenue exposure for diversified pharmaceutical companies.
- Current value is driven by supply continuity, dosage-strength availability, and procurement economics.
- No major current Paragraph IV litigation or settlement appears to alter the market outlook.
- Biosimilar risk does not apply because nisoldipine is a small-molecule drug.
FAQs
Is Sular still available in the United States?
Sular has had limited commercial visibility, while generic extended-release nisoldipine has represented the more relevant supply channel. Availability varies by strength, manufacturer, and distributor inventory.
Does nisoldipine have a generic equivalent?
Yes. Extended-release nisoldipine has been available through generic pharmaceutical channels, although supplier participation and dosage-strength availability can change over time.
Is nisoldipine more effective than amlodipine?
Nisoldipine and amlodipine are both dihydropyridine calcium-channel blockers. Product selection depends on clinical response, tolerability, dosing considerations, drug interactions, and payer coverage rather than a broad commercial superiority claim.
Does nisoldipine have a new chemical entity exclusivity period today?
No. Any original regulatory exclusivity associated with the 1995 approval has long expired.
Can a pharmaceutical company obtain new patents on nisoldipine?
A company could seek patents for a genuinely novel formulation, manufacturing process, dosing regimen, or combination product. A new patent would need to satisfy applicable novelty, non-obviousness, written-description, enablement, and other statutory requirements. Such a patent would not restore exclusivity to the existing conventional extended-release product unless its claims covered that product.
References
- U.S. Food and Drug Administration. (1995). Sular (nisoldipine) extended-release tablets prescribing information. https://www.accessdata.fda.gov/drugsatfda_docs/label/
- U.S. Food and Drug Administration. (2024). Approved drug products with therapeutic equivalence evaluations, commonly known as the Orange Book. https://www.fda.gov/drugs/drug-approvals-and-databases/orange-book
- DailyMed. (2024). Nisoldipine extended-release tablet labeling. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/
- National Library of Medicine. (2024). Nisoldipine drug information. MedlinePlus. https://medlineplus.gov/druginfo/meds/
- U.S. Food and Drug Administration. (1984). Hatch-Waxman Amendments and abbreviated new drug applications. https://www.fda.gov/drugs/abbreviated-new-drug-application-anda/generic-drug-user-fee-amendments