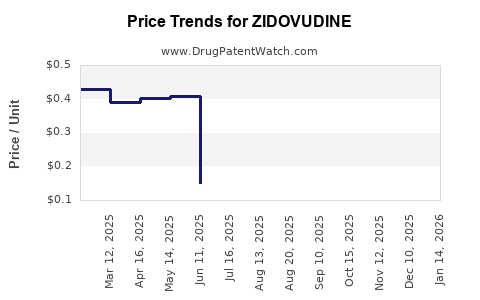
Last updated: September 8, 2026
Zidovudine, also known as azidothymidine or AZT, is a mature antiretroviral with no meaningful branded exclusivity remaining in the United States. The drug generated substantial revenue as Retrovir during the early HIV-treatment market, but its commercial position declined after combination therapy, resistance concerns, and newer nucleoside and integrase-inhibitor regimens displaced it. Current value is concentrated in low-cost generic supply, selected pediatric and perinatal applications, fixed-dose combinations, and public-health procurement.
What is the current market status of zidovudine?
Zidovudine is a generic, low-margin HIV medicine rather than a growth pharmaceutical asset.
The drug is a thymidine nucleoside reverse-transcriptase inhibitor, or NRTI. It was approved by the U.S. Food and Drug Administration in 1987 as Retrovir, becoming the first FDA-approved treatment for HIV infection.[1] It is available in several dosage forms, including capsules, oral solution, and injectable formulations. Zidovudine is also used in fixed-dose combinations such as Combivir, containing zidovudine and lamivudine, and Trizivir, containing zidovudine, lamivudine, and abacavir.
Its market position has changed materially:
| Period |
Market position |
Financial implication |
| 1987-1995 |
First approved HIV treatment and primary antiretroviral option |
High pricing and strong branded demand |
| 1996-2005 |
Combination therapy expands; resistance and toxicity concerns emerge |
Revenue declines as treatment protocols change |
| 2006-2015 |
Generic entry and newer NRTIs gain share |
Price compression and loss of branded value |
| 2016-present |
Mature generic and public-health product |
Low unit prices, limited commercial growth |
Zidovudine remains clinically relevant but is no longer a preferred backbone for most adult HIV regimens. Current treatment guidelines generally favor tenofovir-based combinations and integrase-inhibitor regimens because of better tolerability, dosing convenience, resistance profiles, and long-term treatment economics.[2]
When did zidovudine lose exclusivity?
Zidovudine lost practical U.S. market exclusivity in the mid-2000s after expiration of the core patents associated with the compound and its use in HIV treatment.
The principal U.S. patent commonly associated with zidovudine was U.S. Patent No. 4,724,232, covering 2',3'-dideoxynucleoside compounds and related antiviral applications. The patent issued in 1988 and was assigned to Burroughs Wellcome, the original commercial developer of Retrovir.[3] Its effective U.S. term expired in the mid-2000s, subject to patent-term adjustments and any applicable regulatory extensions.
The critical commercial consequence was the loss of a defensible branded monopoly. Once the core patent term ended, generic manufacturers could compete through abbreviated new drug applications, or ANDAs, without repeating the full clinical development program required for an original new drug application.
What patents protect zidovudine today?
No active U.S. patent estate appears to provide a material barrier to ordinary generic zidovudine supply. The original compound and core therapeutic-use patents are expired. Any remaining patents associated with specific combination products, manufacturing processes, formulations, or foreign jurisdictions must be evaluated separately from the basic zidovudine molecule.
The relevant patent categories are:
- Compound patents covering zidovudine itself.
- Method-of-use patents covering treatment of HIV or prevention of maternal-fetal transmission.
- Formulation patents covering oral solutions, injectable products, or fixed-dose tablets.
- Combination patents covering products such as Combivir and Trizivir.
- Manufacturing patents covering intermediates, synthesis, crystallization, or impurity control.
For a generic manufacturer, the main commercial issue is no longer molecule-level patent infringement. It is regulatory compliance, reliable active pharmaceutical ingredient supply, quality control, and the ability to compete at public-sector prices.
What is the Orange Book status of zidovudine?
The U.S. Orange Book does not provide a current branded exclusivity barrier for ordinary zidovudine products. Retrovir was approved under NDA 019910, while zidovudine combination products were approved under separate applications.[4]
Orange Book analysis must distinguish between:
- A product listed as discontinued for commercial reasons.
- A product withdrawn for safety or efficacy reasons.
- An active product with listed patents.
- Generic products approved through ANDAs.
The presence of a discontinued branded product does not itself block generic approval. For zidovudine, the branded product’s commercial discontinuation and the expiration of historic patents have left the market primarily dependent on generic approvals and public procurement.
Are there Paragraph IV challenges for zidovudine?
Current Paragraph IV litigation is not a major commercial issue for basic zidovudine products because the principal molecule-level patent protection has expired.
Paragraph IV certifications are most relevant when an ANDA applicant seeks approval before the expiration of a listed patent. For zidovudine, the important ANDA wave occurred after the core patent estate had ceased to provide meaningful protection. Historical litigation centered on the validity, scope, and enforceability of patents held by Burroughs Wellcome and related entities during the period when Retrovir was commercially dominant.
The practical assessment is:
| Issue |
Current risk |
| Core zidovudine compound patent |
Low; expired |
| Basic HIV-treatment method patents |
Low; generally expired |
| Generic capsule or oral-solution entry |
Low patent risk |
| Fixed-dose combination patents |
Product-specific and generally limited |
| Process or formulation patents |
Potentially relevant to a specific manufacturing route |
| Current Paragraph IV litigation |
Not a material market-wide constraint |
What formulations are protected by zidovudine patents?
The principal commercial formulations are capsules, oral solution, intravenous injection, and fixed-dose tablets. Formulation protection has been less durable than molecule-level protection because generic manufacturers can often design around a narrow formulation claim or use a conventional dosage form.
Oral capsules and oral solution
Generic capsules and oral solution compete primarily on manufacturing cost, supply continuity, and procurement eligibility. The oral solution has continuing value in pediatric use and for patients unable to swallow tablets. This segment is operationally more complex than standard solid-dose manufacturing because it requires control of microbial quality, preservative systems, taste, stability, and packaging.
Intravenous zidovudine
Intravenous use has historical importance in perinatal prevention and selected hospital settings. Its commercial value is limited because modern prevention protocols use more effective and convenient antiretroviral strategies in many settings. Hospital purchasing is price-sensitive and often based on tenders.
Fixed-dose combinations
Combivir combines zidovudine with lamivudine. Trizivir combines zidovudine, lamivudine, and abacavir. These products improved adherence relative to separate tablets but became less competitive as newer combinations offered better tolerability and simpler dosing.
Combination-product protection does not restore meaningful exclusivity to the underlying zidovudine market. Generic manufacturers can compete with the individual components, and once combination patents expire, authorized or generic fixed-dose alternatives can enter.
How does zidovudine compare with competing HIV drugs?
Zidovudine has lost share to tenofovir, abacavir, lamivudine, emtricitabine, and integrase-inhibitor-based regimens.
| Drug or class |
Relative position versus zidovudine |
| Tenofovir disoproxil fumarate |
Broader use in first-line combinations and HIV prevention; different renal and bone-risk profile |
| Tenofovir alafenamide |
Lower systemic tenofovir exposure and strong use in modern combination products |
| Lamivudine |
Often paired with integrase inhibitors or tenofovir; generally easier to administer |
| Abacavir |
Used selectively because of cardiovascular-risk and HLA-B*5701 screening considerations |
| Dolutegravir |
Integrase inhibitor with high potency and a major role in contemporary first-line therapy |
| Bictegravir |
Used in modern single-tablet regimens |
| Zidovudine |
Retained in selected pediatric, perinatal, salvage, and resource-limited settings |
Zidovudine’s major clinical disadvantages include anemia, neutropenia, lipoatrophy, mitochondrial toxicity, frequent dosing in some historical regimens, and a lower convenience profile than newer products.[5] Those limitations directly affect demand and pricing power.
What is the financial trajectory for zidovudine?
Zidovudine followed a classic pharmaceutical lifecycle: high early revenue, rapid decline after therapeutic substitution, and long-term survival as a low-cost generic.
Branded revenue phase
Retrovir benefited from limited competition when HIV had few treatment options. Burroughs Wellcome and later Glaxo Wellcome and GlaxoSmithKline captured substantial revenue from the product and its combination products. The early market supported premium pricing because treatment alternatives were limited and clinical demand was urgent.
The revenue model changed after the introduction of multidrug antiretroviral therapy in the mid-1990s. Zidovudine remained part of several combination regimens, but its unit demand no longer represented monotherapy demand. Revenue migrated from the single-agent product to fixed-dose combinations and broader HIV portfolios.
Generic erosion phase
After patent expiry, generic competition reduced prices. Public-sector tenders accelerated the decline because procurement agencies typically select products based on lowest sustainable cost, regulatory qualification, and supply reliability.
Generic erosion affected both volume and price:
- Adult first-line use declined.
- Branded Retrovir lost formulary priority.
- Combination products faced substitution from newer regimens.
- Public procurement shifted toward lower-cost alternatives.
- Manufacturing margins narrowed.
- Revenue became fragmented among multiple suppliers.
Current financial profile
No major pharmaceutical company separately reports zidovudine revenue as a material standalone product line. GSK’s HIV business is now centered on newer products and partnerships, including dolutegravir-based medicines and long-acting therapies, rather than Retrovir.[6]
Current zidovudine revenue is therefore best characterized as:
- Low per-unit pricing.
- Moderate or low global volume.
- Higher dependence on institutional and government buyers.
- Limited brand premium.
- High sensitivity to supply interruptions.
- Minimal potential for large-scale revenue growth without a new indication or procurement shift.
What companies manufacture or supply zidovudine?
The market includes the original branded developer, generic pharmaceutical companies, contract manufacturers, and suppliers serving national procurement programs. The supplier base varies by country and regulatory jurisdiction.
Manufacturers compete on:
- FDA, EMA, WHO, or national regulatory approval.
- Active pharmaceutical ingredient sourcing.
- Product stability and shelf life.
- Pediatric formulation capability.
- Tender pricing.
- Manufacturing capacity.
- Supply-chain reliability.
- Registration in low- and middle-income markets.
The primary manufacturing barrier is not patent exclusion. It is maintaining a compliant, economical production platform for a mature product with limited pricing headroom.
What licensing deals affect zidovudine?
The main historic commercial transfer involved Burroughs Wellcome’s development and commercialization of zidovudine, followed by the corporate consolidation of Burroughs Wellcome into Glaxo Wellcome and later GSK. The product was not built around a current royalty-bearing licensing model comparable to newer HIV products.
The commercial significance of historic ownership is now limited because the core patents have expired. GSK retains historical brand and regulatory knowledge, but that does not create meaningful generic-market control.
What patent litigation affects zidovudine?
Zidovudine’s important patent disputes occurred during the branded exclusivity period. Litigation addressed the scope and enforceability of patents covering nucleoside analogues and antiviral use. Those disputes shaped the timing of generic entry but do not create a current market-wide barrier.
Current litigation risk is more likely to arise from:
- ANDA disputes involving a specific combination product.
- Product liability or manufacturing-quality claims.
- Procurement exclusion or regulatory noncompliance.
- Trademark disputes involving branded presentation.
- Contract disputes over supply and distribution.
- Patent claims directed to a particular process or formulation.
No current litigation category appears capable of restoring broad exclusivity to single-agent zidovudine.
What is the FDA regulatory status of zidovudine?
Zidovudine is an FDA-approved antiretroviral active ingredient with established safety, efficacy, dosing, and manufacturing requirements.[1] Generic versions can rely on the reference product’s established clinical record through the ANDA pathway, subject to bioequivalence and quality requirements.
Regulatory considerations include:
- Bioequivalence for oral solid products.
- Stability and microbial controls for oral solution.
- Sterility and container closure for injection.
- Pediatric dosing and labeling.
- Drug-drug interaction management.
- Hematologic toxicity monitoring.
- Appropriate use in combination therapy.
Because zidovudine is an old molecule, regulatory risk is generally lower than for a new chemical entity. Manufacturing deviations, supply interruptions, or labeling deficiencies remain material commercial risks.
Does zidovudine have biosimilar risk?
Zidovudine has no biosimilar risk because it is a small-molecule drug, not a biologic. Its competitive threat comes from generic drugs, therapeutic substitution, and newer antiretrovirals.
The economic distinction is important:
- Generic competition addresses the same active ingredient.
- Biosimilar competition applies to biologic reference products.
- Therapeutic substitution shifts demand to a different medicine or regimen.
For zidovudine, therapeutic substitution is the larger long-term threat because newer antiretroviral combinations offer better convenience and tolerability.
What generic launch scenarios exist for zidovudine?
The main generic scenarios are:
Continued low-price supply
Generic suppliers maintain production for public-health programs, pediatric use, and hospital demand. This is the most likely base case.
Supplier consolidation
Low margins may lead smaller manufacturers to exit. Fewer suppliers can increase shortage risk even when the product has no patent barrier.
Regional demand preservation
Some markets may continue using zidovudine because of established guidelines, procurement economics, pediatric needs, or local registration practices.
Further therapeutic substitution
As national HIV programs update protocols, zidovudine demand may continue to decline in favor of tenofovir-based and integrase-inhibitor regimens.
How strong is the zidovudine patent estate?
The patent estate is weak from a current commercial-exclusivity perspective.
| Patent-estate factor |
Assessment |
| Core compound protection |
Expired |
| Basic HIV-treatment protection |
Expired or commercially nonblocking |
| Formulation protection |
Narrow and product-specific |
| Combination-product protection |
Historical and largely exhausted |
| Manufacturing protection |
Potentially relevant to a specific process |
| Geographic coverage |
Materially different by country, but generally mature |
| Generic-entry barrier |
Low |
| Litigation leverage |
Low for basic single-agent products |
| Revenue protection |
Minimal |
The economic value lies in supply execution, not proprietary exclusivity.
What is the outlook for zidovudine revenue?
Zidovudine revenue is likely to remain flat to declining over the long term, with occasional volume increases from procurement cycles, shortages of alternatives, pediatric demand, or changes in national treatment protocols.
The principal revenue risks are therapeutic displacement and continued price erosion. The principal upside is limited to niche demand, contract supply, and markets where zidovudine remains embedded in legacy treatment or prevention programs.
A new commercial growth phase would require a meaningful change in clinical guidance, a new delivery technology, or an indication that creates demand beyond established HIV treatment. No such driver is currently central to the product’s market position.
Key Takeaways
- Zidovudine is a mature generic antiretroviral with no meaningful U.S. molecule-level exclusivity.
- Retrovir generated substantial early HIV-treatment revenue, but branded economics deteriorated after combination therapy and patent expiry.
- The core U.S. patent estate, including U.S. Patent No. 4,724,232, is expired.
- Current competition is based on generic price, regulatory compliance, manufacturing reliability, and public procurement access.
- Tenofovir-based and integrase-inhibitor regimens have displaced zidovudine in most adult first-line treatment settings.
- Pediatric, perinatal, hospital, and resource-limited-market demand provide residual volume.
- Zidovudine has generic risk, not biosimilar risk.
- Current financial exposure is fragmented and generally immaterial to large branded pharmaceutical companies.
- The largest business risks are therapeutic substitution, supplier exit, and low-margin manufacturing.
- The most likely revenue trajectory is stable-to-declining with limited growth potential.
FAQs About Zidovudine Patent and Market Value
Is Retrovir still commercially important?
No. Retrovir has historical importance, but current zidovudine demand is primarily generic and institutional.
Can a company obtain a new patent on zidovudine?
A new patent cannot ordinarily restore protection for the known zidovudine molecule. A company could seek protection for a genuinely novel formulation, manufacturing process, delivery system, or new therapeutic use if the statutory patent requirements are met.
Is zidovudine still used to prevent mother-to-child HIV transmission?
It can be used in selected perinatal settings, but contemporary prevention strategies often rely on combination antiretroviral therapy and maternal viral-load suppression rather than zidovudine monotherapy.[2]
Does zidovudine have a large generic market in the United States?
No. The U.S. market is mature and relatively limited compared with the market for newer antiretroviral combinations. Demand is concentrated in specific clinical situations and existing treatment protocols.
Which drug most directly replaced zidovudine?
Tenofovir-based regimens replaced zidovudine in many treatment settings, while dolutegravir and other integrase inhibitors reshaped the broader HIV-treatment market. The replacement was therapeutic rather than the result of a single competing product.
References
-
U.S. Food and Drug Administration. (1987). Retrovir (zidovudine) prescribing information. FDA.
-
U.S. Department of Health and Human Services. (2024). Guidelines for the use of antiretroviral agents in adults and adolescents with HIV. ClinicalInfo.HIV.gov.
-
U.S. Patent and Trademark Office. (1988). U.S. Patent No. 4,724,232: 2',3'-Dideoxynucleosides. U.S. Department of Commerce.
-
U.S. Food and Drug Administration. (2024). Approved drug products with therapeutic equivalence evaluations: Orange Book. FDA.
-
National Institutes of Health. (2024). Zidovudine: Drug information. ClinicalInfo.HIV.gov.
-
GSK plc. (2024). Annual report 2023. GSK.