Share This Page
SODIUM POLYSTYRENE SULFONATE - Generic Drug Details
✉ Email this page to a colleague
What are the generic drug sources for sodium polystyrene sulfonate and what is the scope of patent protection?
Sodium polystyrene sulfonate
is the generic ingredient in five branded drugs marketed by Kvk Tech, Concordia, Ani Pharms, Ajenat Pharms, Chartwell Rx, Citrusphrma, Cmp Pharma Inc, Epic Pharma Llc, Nuvo Pharms Inc, Pai Holdings Pharm, Upsher Smith Labs, Hikma, Lyne, Morton Grove, and Roxane, and is included in eighteen NDAs. Additional information is available in the individual branded drug profile pages.Eleven suppliers are listed for this compound.
Summary for SODIUM POLYSTYRENE SULFONATE
| US Patents: | 0 |
| Tradenames: | 5 |
| Applicants: | 15 |
| NDAs: | 18 |
| Finished Product Suppliers / Packagers: | 11 |
| Raw Ingredient (Bulk) Api Vendors: | 56 |
| Clinical Trials: | 9 |
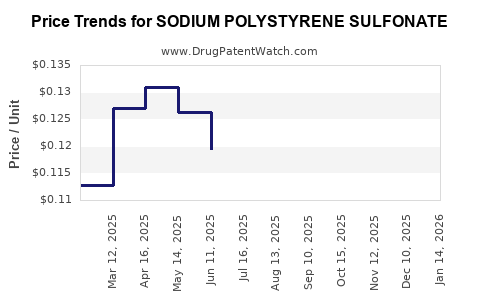
| Drug Prices: | Drug price trends for SODIUM POLYSTYRENE SULFONATE |
| What excipients (inactive ingredients) are in SODIUM POLYSTYRENE SULFONATE? | SODIUM POLYSTYRENE SULFONATE excipients list |
| DailyMed Link: | SODIUM POLYSTYRENE SULFONATE at DailyMed |
Recent Clinical Trials for SODIUM POLYSTYRENE SULFONATE
Identify potential brand extensions & 505(b)(2) entrants
| Sponsor | Phase |
|---|---|
| Mario Negri Institute for Pharmacological Research | PHASE3 |
| Alexandria University | NA |
| University of California, Irvine | Phase 4 |
Anatomical Therapeutic Chemical (ATC) Classes for SODIUM POLYSTYRENE SULFONATE
US Patents and Regulatory Information for SODIUM POLYSTYRENE SULFONATE
| Applicant | Tradename | Generic Name | Dosage | NDA | Approval Date | TE | Type | RLD | RS | Patent No. | Patent Expiration | Product | Substance | Delist Req. | Exclusivity Expiration |
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Nuvo Pharms Inc | SODIUM POLYSTYRENE SULFONATE | sodium polystyrene sulfonate | POWDER;ORAL, RECTAL | 204071-002 | Nov 28, 2014 | RX | No | No | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | ||||
| Cmp Pharma Inc | SODIUM POLYSTYRENE SULFONATE | sodium polystyrene sulfonate | POWDER;ORAL, RECTAL | 089910-001 | Jan 19, 1989 | AA | RX | No | No | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | |||
| Morton Grove | SODIUM POLYSTYRENE SULFONATE | sodium polystyrene sulfonate | SUSPENSION;ORAL, RECTAL | 088717-001 | Sep 11, 1984 | DISCN | No | No | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | ||||
| Ani Pharms | KIONEX | sodium polystyrene sulfonate | SUSPENSION;ORAL, RECTAL | 040028-001 | Sep 17, 2007 | AA | RX | No | No | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | |||
| >Applicant | >Tradename | >Generic Name | >Dosage | >NDA | >Approval Date | >TE | >Type | >RLD | >RS | >Patent No. | >Patent Expiration | >Product | >Substance | >Delist Req. | >Exclusivity Expiration |
Sodium Polystyrene Sulfonate Market Dynamics, Patent Status, and Financial Trajectory
Sodium polystyrene sulfonate (SPS), marketed historically as Kayexalate and sold mainly through generic suppliers, is a mature potassium-binding drug with limited pricing power and low patent protection. Its commercial position has weakened as patiromer and sodium zirconium cyclosilicate gained adoption for chronic hyperkalemia. SPS remains relevant in cost-sensitive markets because of low acquisition cost, broad availability, and long clinical experience, but its use is constrained by delayed onset, sodium burden, tolerability issues, and gastrointestinal safety concerns.
What is the current market position of sodium polystyrene sulfonate?
SPS is an ion-exchange resin that exchanges sodium for potassium in the gastrointestinal tract. It is used to reduce serum potassium in patients with hyperkalemia, particularly when lower-cost treatment is prioritized.
| Market factor | Current position |
|---|---|
| Drug class | Cation-exchange potassium binder |
| Primary active ingredient | Sodium polystyrene sulfonate |
| Major historical brand | Kayexalate |
| Regulatory status | FDA-approved prescription drug; multiple generic products |
| Primary use | Reduction of elevated serum potassium |
| Onset | Delayed and variable; not a preferred emergency monotherapy |
| Patent position | Foundational protection expired; generic competition established |
| Pricing power | Low |
| Main competitors | Patiromer, marketed as Veltassa; sodium zirconium cyclosilicate, marketed as Lokelma |
| Commercial trajectory | Mature, low-growth or declining in developed markets |
| Financial visibility | No separately reported global SPS revenue for most suppliers |
SPS has the strongest commercial position where drug budgets are constrained, newer potassium binders are unavailable, or prescribers prioritize acquisition cost over convenience and tolerability. Its relative position is weaker in chronic kidney disease and heart failure populations where long-term potassium control can support continued use of renin-angiotensin-aldosterone system inhibitors.
When did sodium polystyrene sulfonate lose exclusivity?
SPS has no meaningful remaining composition-of-matter exclusivity in the United States. The product was approved decades ago, and the active ingredient is supplied by multiple generic manufacturers.
The original Kayexalate product was associated with historical approval by the FDA under NDA 011287. Generic sodium polystyrene sulfonate products are approved through abbreviated new drug applications and do not depend on a current innovator patent for market access.[1]
The practical exclusivity timeline is therefore:
| Period | Commercial status |
|---|---|
| 1950s onward | Original SPS products introduced and used clinically |
| 1980s-2000s | Broad generic and international availability expanded |
| 2010s | New potassium binders introduced in the United States |
| 2020s | SPS remains generic and price-sensitive; newer agents take share in chronic treatment |
Patent expiration does not eliminate all commercial barriers. Suppliers still need compliant drug-substance sourcing, manufacturing controls, validated particle and exchange characteristics, packaging, and regulatory approval. Those requirements are operational barriers rather than durable exclusivity.
What patents protect sodium polystyrene sulfonate?
No current U.S. patent estate appears to provide material blocking protection for the basic SPS product. Historical patents relating to sulfonated polymer resins and ion-exchange materials are expired or commercially irrelevant to routine generic SPS sales.
Formulation patents
SPS formulations can differ by:
- Resin particle size
- Sodium content
- Suspension vehicle
- Powder or oral suspension presentation
- Flavoring and excipient systems
- Unit-dose packaging
- Combination with sorbitol or other excipients
These formulation differences can create product-specific patent or regulatory issues in some jurisdictions, but they do not generally restore broad exclusivity to SPS. The key historical safety issue has been the use of sorbitol-containing products. The FDA warned that concomitant administration of SPS with sorbitol was associated with cases of colonic necrosis and other serious gastrointestinal injury.[2]
Method-of-use patents
SPS does not have a commercially important method-of-use patent estate comparable with the patent programs supporting Veltassa or Lokelma. Generic suppliers generally compete on price, availability, contracting, and supply reliability rather than patented clinical positioning.
Manufacturing and intellectual-property barriers
The manufacturing process is technically manageable for established pharmaceutical suppliers. Commercial barriers include:
- Consistent sulfonation and cross-linking of the polymer.
- Control of particle-size distribution and potassium-exchange capacity.
- Batch-to-batch control of impurities and extractables.
- Stability of oral suspensions or powders.
- Compliance with current good manufacturing practice requirements.
- Reliable access to qualified resin and excipient suppliers.
These factors can produce temporary shortages or supplier concentration. They do not create an effective long-term monopoly because multiple manufacturers can produce or source comparable resin systems.
What is the FDA regulatory status of sodium polystyrene sulfonate?
SPS is an FDA-approved prescription potassium binder. Current labeling states that the drug is used for the treatment of hyperkalemia, but its potassium-lowering effect is delayed and variable. It is not an appropriate replacement for emergency interventions when rapid correction is required.[1]
The label contains clinically important restrictions:
- SPS may cause clinically significant sodium exposure.
- Patients with heart failure, severe hypertension, or sodium-sensitive conditions require caution.
- It should not be used in patients with obstructive bowel disease or abnormal bowel motility in relevant clinical settings.
- Separation from other orally administered medicines may be required because SPS can bind drugs in the gastrointestinal tract.
- Serious gastrointestinal events, including intestinal necrosis, have been reported.
- Concomitant use with sorbitol is discouraged because of gastrointestinal safety concerns.[1,2]
The FDA approved newer potassium binders partly in response to the need for more predictable, better-tolerated chronic therapies. Patiromer was approved in 2015, and sodium zirconium cyclosilicate was approved in 2018.[3,4]
What is the Orange Book status of sodium polystyrene sulfonate?
SPS products are primarily generic FDA-approved products rather than protected branded products with a commercially significant Orange Book patent strategy. Any product-specific listing must be reviewed by application number and manufacturer because generic listings and labeling can change.
The relevant commercial conclusion is that generic SPS suppliers do not face a dominant active patent listed by an innovator that would ordinarily support a broad Paragraph IV litigation campaign. Market entry is generally governed by ANDA approval, supply qualification, and commercial contracting.
By contrast, Veltassa and Lokelma have relied on branded product patents, formulation claims, manufacturing claims, and method-of-use positions to extend commercial protection beyond the underlying clinical concept of potassium binding.[5,6]
How does sodium polystyrene sulfonate compare with Veltassa and Lokelma?
SPS has a cost advantage but a weaker clinical and commercial profile for long-term use.
| Attribute | Sodium polystyrene sulfonate | Veltassa | Lokelma |
|---|---|---|---|
| Active ingredient | Sodium polystyrene sulfonate | Patiromer sorbitex calcium | Sodium zirconium cyclosilicate |
| Approval era | Mid-20th century | 2015 | 2018 |
| Generic availability | Yes | No broad U.S. generic equivalent during the branded period | No broad U.S. generic equivalent during the branded period |
| Sodium load | Material sodium exposure | Calcium-based exchange; no sodium load from active binder | Contains sodium |
| Onset | Delayed and variable | Hours; chronic use | Relatively rapid potassium reduction, but not emergency monotherapy |
| Chronic-use positioning | Limited by tolerability and safety concerns | Strong | Strong |
| Acquisition cost | Low | High relative to SPS | High relative to SPS |
| Main commercial advantage | Price and availability | Chronic potassium control without sodium exchange | Faster and predictable potassium reduction |
| Main commercial limitation | GI risk, sodium burden, variable effect | Drug-interaction spacing and cost | Edema and sodium-related concerns |
Clinical guidelines increasingly distinguish acute management from chronic potassium control. Emergency hyperkalemia requires cardiac monitoring, membrane stabilization when indicated, and therapies that shift or remove potassium rapidly. SPS is poorly suited to that role because its effect is delayed.[7]
In chronic kidney disease and heart failure, newer binders can preserve guideline-directed therapies by controlling recurrent hyperkalemia. That clinical role supports higher prices and stronger reimbursement positioning than SPS.
What is the financial trajectory of sodium polystyrene sulfonate?
SPS does not have a transparent standalone revenue stream comparable with Veltassa or Lokelma. Generic manufacturers usually report total portfolios rather than product-level SPS revenue. Financial analysis therefore depends on market structure rather than audited product sales.
Revenue trajectory
The expected financial trajectory is:
| Driver | Effect on SPS economics |
|---|---|
| Generic competition | Sustained price compression |
| Low manufacturing complexity | Limits supplier pricing power |
| Hospital and pharmacy formularies | Favor low-cost SPS where clinically acceptable |
| Chronic-care substitution | Shifts volume to Veltassa and Lokelma |
| Safety concerns | Reduces use in long-term and high-risk populations |
| Supply interruptions | Can create temporary price increases |
| International access | Supports residual volume in emerging markets |
| Limited marketing investment | Restricts branded demand generation |
| Reimbursement pressure | Favors SPS in budget-sensitive channels |
SPS revenue is likely to be stable to declining in high-income markets, with erosion concentrated in chronic hyperkalemia. Volume can remain meaningful because hyperkalemia prevalence is rising with chronic kidney disease, diabetes, heart failure, and use of renin-angiotensin-aldosterone system inhibitors. That disease growth does not necessarily translate into SPS revenue growth because newer binders are capturing the incremental value of chronic treatment.
Margin profile
Gross margins depend heavily on manufacturing scale and distribution contracts. A supplier with captive resin production or a low-cost international manufacturing base can retain acceptable margins. A distributor buying finished product from third parties faces greater exposure to shortages, freight costs, and contract price pressure.
SPS lacks the commercial characteristics that support high-margin specialty pharmaceuticals:
- No active composition-of-matter exclusivity
- Limited brand differentiation
- No meaningful patient-services ecosystem
- Low switching costs between generic suppliers
- Limited promotional value
- Substitution by newer branded agents
The product can still generate attractive contribution margins when manufacturing costs are low and competition is limited in a particular channel. Those margins are generally vulnerable to new supplier entry.
Which companies are challenging sodium polystyrene sulfonate?
The main competitive challenge comes from manufacturers of newer potassium binders rather than generic companies pursuing SPS litigation.
Vifor Pharma and Veltassa
Veltassa, developed by Vifor Pharma, targets chronic hyperkalemia. Its commercial rationale is based on improved chronic-use positioning, reduced sodium exposure relative to sodium-based binders, and support for continued use of renin-angiotensin-aldosterone system therapies.[5]
AstraZeneca and Lokelma
Lokelma was developed by AstraZeneca after the company acquired rights from ZS Pharma. It competes on potency, predictable potassium reduction, and chronic management. Its sodium content creates a different risk-benefit profile from patiromer but remains commercially preferable to SPS for many managed-care and specialty-care settings.[4,6]
Generic SPS suppliers
Generic suppliers compete primarily through:
- Wholesale acquisition cost
- Contracted hospital pricing
- Pharmacy benefit coverage
- Supply continuity
- Dosage-form availability
- Regulatory inspection history
- Private-label relationships
The market is fragmented, and supplier identity can vary by country and distribution channel.
Are there Paragraph IV challenges or patent lawsuits involving sodium polystyrene sulfonate?
There is no widely recognized active U.S. Paragraph IV campaign directed at the basic SPS product. The reason is commercial: SPS is already generic, and the underlying product lacks a valuable unexpired innovator patent that would justify extensive litigation.
Patent litigation has greater relevance to patiromer and sodium zirconium cyclosilicate. Generic entrants to those products may challenge branded formulation, composition, manufacturing, or method-of-use patents. Such disputes can affect the timing of substitution away from SPS, but they do not restore SPS exclusivity.
Settlement agreements involving newer potassium binders could delay generic entry and extend the period during which SPS remains the low-cost alternative. The direct financial impact on SPS would be indirect and dependent on formulary decisions, payer restrictions, and physician willingness to use the older resin.
What generic entry risks exist for sodium polystyrene sulfonate?
Generic-entry risk is already realized rather than prospective. SPS operates in a post-exclusivity market.
The principal risks are:
- Further price erosion from additional suppliers.
- Contract loss to vertically integrated generic manufacturers.
- Product recalls caused by manufacturing or contamination failures.
- Shortages if resin supply becomes concentrated.
- Formulary removal in favor of newer binders.
- Safety-driven restrictions on long-term use.
- Loss of hospital volume to standardized potassium-management protocols.
The principal upside risk is supply disruption. Because SPS is inexpensive and clinically familiar, a shortage can temporarily increase demand for another generic supplier. That effect is usually volume-driven and does not create durable pricing power.
What geographic markets remain attractive for sodium polystyrene sulfonate?
SPS has the strongest residual commercial opportunity in markets where:
- Patiromer and Lokelma are not registered or are unaffordable.
- Public reimbursement systems prioritize low acquisition cost.
- Generic hospital procurement dominates prescribing.
- Chronic kidney disease and hyperkalemia treatment capacity are expanding.
- Local manufacturing or import channels are established.
The United States and Western Europe are more exposed to substitution by newer binders. Emerging markets may retain SPS longer because of lower prices and restricted access to branded alternatives. Regulatory requirements differ by jurisdiction, particularly for resin specifications, sorbitol-containing products, labeling warnings, and pharmacovigilance.
How strong is the sodium polystyrene sulfonate patent estate?
The patent estate is weak from an exclusivity perspective but adequate from a manufacturing perspective.
| Estate category | Assessment |
|---|---|
| Composition patent | Expired or commercially exhausted |
| Basic therapeutic-use claims | Expired or not commercially blocking |
| Formulation patents | Limited and product-specific |
| Method-of-use patents | Limited commercial importance |
| Manufacturing know-how | Moderate operational value |
| Regulatory exclusivity | No meaningful current exclusivity |
| Litigation leverage | Low |
| Generic substitution protection | None of strategic significance |
SPS is therefore a supply-chain and formulary asset, not a patent asset. Its value lies in low cost, established procurement channels, and availability.
What are the likely generic launch scenarios?
The likely market scenarios are:
Base case
SPS remains available as a low-cost generic, with gradual volume erosion in chronic hyperkalemia. Generic pricing stays compressed, while hospitals and public systems continue using it selectively.
Downside case
Safety concerns, reimbursement restrictions, or broad adoption of newer binders accelerate substitution. SPS becomes concentrated in inpatient, emergency-adjacent, or resource-constrained settings.
Supply-constrained case
One or more manufacturers experience quality or sourcing problems. Remaining suppliers gain temporary volume and pricing leverage, but the product remains structurally generic.
Emerging-market growth case
Expansion of kidney-disease treatment and limited access to Veltassa and Lokelma increases SPS demand. Volume rises without materially improving global pricing because procurement remains price-sensitive.
What is the investment and licensing outlook?
SPS is generally unattractive as a standalone licensing target unless the transaction includes:
- A low-cost manufacturing platform
- Regional distribution rights
- A broader renal-care portfolio
- A hospital procurement network
- A differentiated ready-to-use formulation
- Proven supply continuity
- Access to markets where newer potassium binders are unavailable
An acquisition based only on SPS revenue would face low growth, limited IP protection, and substitution risk. The product can have strategic value inside a broader nephrology portfolio, particularly where it provides a low-cost option alongside premium chronic potassium binders.
Key Takeaways
- Sodium polystyrene sulfonate is a mature, generic potassium binder with no meaningful remaining U.S. exclusivity.
- Its commercial value is based on low cost and availability, not patent protection.
- SPS faces sustained substitution from Veltassa and Lokelma in chronic hyperkalemia.
- Financial reporting is rarely product-specific, but the market profile indicates compressed pricing and flat-to-declining developed-market revenue.
- FDA labeling and safety concerns limit chronic use, especially in patients vulnerable to sodium overload or gastrointestinal injury.
- No major active Paragraph IV campaign is central to the SPS market.
- Manufacturing know-how and supply reliability matter more than patent strength.
- Emerging markets and budget-sensitive hospital systems provide the strongest residual demand.
- SPS remains commercially relevant but has limited standalone investment or licensing appeal.
FAQs
Is sodium polystyrene sulfonate still commercially viable?
Yes. It remains viable as a low-cost generic, especially in hospitals, public-health systems, and countries where newer potassium binders are expensive or unavailable. Its long-term growth prospects are limited.
Is Kayexalate still protected by patents?
No commercially meaningful patent protection appears to block generic sodium polystyrene sulfonate in the United States. Kayexalate-related exclusivity has expired, and generic products are established.
Can sodium polystyrene sulfonate compete with Lokelma on price?
Yes. SPS is typically much less expensive at acquisition. Lokelma competes through more predictable potassium reduction, stronger chronic-care positioning, and branded reimbursement rather than low price.
Does sodium polystyrene sulfonate have biosimilar competition?
No. SPS is a small-molecule polymeric drug product, not a biologic. The relevant competition is generic substitution and branded potassium binders, not biosimilars.
What is the largest commercial risk for sodium polystyrene sulfonate manufacturers?
The largest structural risk is loss of chronic-use volume to patiromer and sodium zirconium cyclosilicate. The largest operational risk is a manufacturing or supply interruption in a low-margin product with limited ability to pass through higher costs.
References
-
U.S. Food and Drug Administration. (2023). Sodium polystyrene sulfonate prescribing information. FDA/DailyMed labeling.
-
U.S. Food and Drug Administration. (2009). FDA drug safety communication: Reports of colonic necrosis in patients receiving sodium polystyrene sulfonate in sorbitol. FDA.
-
U.S. Food and Drug Administration. (2015). Veltassa (patiromer) approval letter and prescribing information. FDA.
-
U.S. Food and Drug Administration. (2018). Lokelma (sodium zirconium cyclosilicate) approval letter and prescribing information. FDA.
-
Vifor Pharma. (2023). Veltassa prescribing information and product information. Vifor Pharma.
-
AstraZeneca. (2023). Lokelma prescribing information and product information. AstraZeneca.
-
Kidney Disease: Improving Global Outcomes. (2020). KDIGO 2020 clinical practice guideline for diabetes management in chronic kidney disease. Kidney International, 98(4S), S1-S115.
More… ↓
