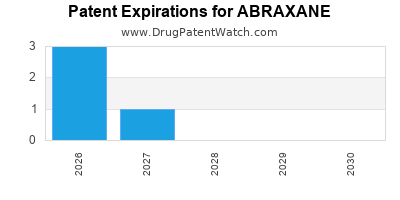
Last updated: August 19, 2026
Abraxane market dynamics are shifting from premium oncology growth to erosion management. The albumin-bound paclitaxel product generated approximately $1 billion in annual sales at its peak under Celgene and Bristol Myers Squibb, but revenue has faced pressure from generic nab-paclitaxel, lower chemotherapy volumes, pricing controls, and the maturity of its pancreatic, breast, and lung cancer indications. Abraxane remains commercially relevant because its albumin-bound formulation has differentiated administration and clinical positioning, but its patent and exclusivity profile no longer supports the growth rates seen after the pancreatic-cancer launch.
Abraxane Market Dynamics, Sales Trajectory, Patents, Generics, and Competitive Outlook
What is Abraxane and how does it compete in oncology?
Abraxane is paclitaxel protein-bound particles for injectable suspension, administered intravenously. The active ingredient is paclitaxel, a microtubule inhibitor. Unlike conventional paclitaxel products, Abraxane uses albumin-bound nanoparticles and does not require the polyoxyethylated castor oil solvent used in several conventional paclitaxel formulations.
The formulation supports several commercial and clinical differentiators:
- No routine corticosteroid and antihistamine premedication is required to prevent solvent-related hypersensitivity reactions.
- Administration time is shorter than with some conventional paclitaxel regimens.
- The product is used in metastatic breast cancer, locally advanced or metastatic non-small-cell lung cancer, and metastatic adenocarcinoma of the pancreas.
- The pancreatic-cancer regimen combines Abraxane with gemcitabine.
The product was originally developed by Abraxis BioScience. Celgene acquired Abraxis in 2010, and Bristol Myers Squibb acquired Celgene in 2019. Abraxane is now part of BMS’s mature oncology portfolio.
What are Abraxane’s FDA-approved indications?
The FDA approved Abraxane for three principal indications.
| Indication |
FDA milestone |
Commercial relevance |
| Metastatic breast cancer after failure of combination chemotherapy or relapse within six months of adjuvant chemotherapy |
2005 |
Original U.S. approval |
| Locally advanced or metastatic non-small-cell lung cancer, with carboplatin |
2012 |
Expanded thoracic oncology use |
| Metastatic adenocarcinoma of the pancreas, with gemcitabine |
2013 |
Largest growth driver and key revenue expansion |
The pancreatic indication materially expanded the addressable market because it placed Abraxane in first-line treatment for a high-mortality cancer with substantial chemotherapy demand. FDA labeling specifies a 125 mg/m² dose on Days 1, 8, and 15 of each 28-day cycle for pancreatic cancer, subject to dose modification for toxicity (U.S. Food and Drug Administration, 2023).
Abraxane is not a biologic. Biosimilar approval pathways therefore do not apply. Competitive risk comes from generic or alternative paclitaxel products, not from biosimilars.
How much revenue has Abraxane generated?
Abraxane reached approximately $1 billion in annual sales before entering a mature or declining phase. Reported figures vary by year and reporting convention because Celgene and BMS changed portfolio disclosures after the 2019 acquisition.
| Fiscal year |
Reported Abraxane sales, approximate |
Company context |
| 2017 |
$997 million |
Celgene |
| 2018 |
$1.03 billion |
Celgene |
| 2019 |
$1.13 billion |
Celgene; final full reporting period before BMS integration |
| 2020 |
Approximately $1.0 billion |
BMS portfolio reporting |
| 2021 |
Approximately $1.1 billion |
Continued pandemic-era oncology disruption |
| 2022 |
Approximately $1.0 billion |
Mature product with generic pressure |
| 2023 |
Approximately $0.9 billion to $1.0 billion |
Declining mature-brand profile |
Celgene reported Abraxane net sales of $1.13 billion in 2019, up from approximately $1.03 billion in 2018 (Celgene Corporation, 2019). BMS subsequently reported Abraxane within its established brands and oncology portfolio rather than presenting the product with the same level of standalone detail in every disclosure period (Bristol Myers Squibb, 2024).
The financial trajectory has three phases:
- Launch and indication expansion: Sales increased after the 2005 breast-cancer approval and accelerated after the 2013 pancreatic-cancer approval.
- Peak commercial period: Annual sales reached roughly $1 billion or more, supported by pancreatic-cancer demand and broad oncology distribution.
- Maturity and erosion: Revenue weakened as the product aged, generic competition emerged, and hospitals used lower-cost taxane alternatives.
Why did Abraxane sales grow after 2013?
The pancreatic-cancer approval was the principal growth catalyst. The MPACT trial showed improved overall survival for nab-paclitaxel plus gemcitabine compared with gemcitabine alone in metastatic pancreatic adenocarcinoma. The regimen became an established first-line option alongside FOLFIRINOX and other chemotherapy approaches (Von Hoff et al., 2013).
Growth also came from:
- Higher use in community oncology.
- Expansion of the U.S. pancreatic-cancer treatment market.
- Greater physician familiarity with albumin-bound delivery.
- Use in patients for whom solvent-based paclitaxel administration was less attractive.
- BMS’s scale in oncology sales and hospital contracting after the Celgene acquisition.
The product’s growth was not driven by a new molecular entity. It was driven by reformulation, expanded clinical evidence, and indication expansion around an established cytotoxic active ingredient.
When does Abraxane lose exclusivity?
Abraxane’s regulatory exclusivity has expired. Its commercial protection now depends mainly on patents, formulation differentiation, manufacturing complexity, and clinical adoption.
The 2005 approval did not provide the type of long-duration new chemical entity exclusivity available to a novel active ingredient because paclitaxel was already known. The pancreatic indication could support limited new-clinical-investigation exclusivity, but that period has also expired.
The key practical dates are:
| Protection category |
Abraxane status |
| New chemical entity exclusivity |
Not available for paclitaxel |
| Original FDA approval |
2005 |
| Pancreatic indication approval |
2013 |
| Regulatory exclusivity for later indications |
Expired |
| Core formulation and manufacturing patents |
Expiration dates extend into the mid-2020s, depending on patent and patent-term adjustment |
| Generic entry |
Began after FDA approval of generic nab-paclitaxel |
Public patent records associated with Abraxane include U.S. patents covering protein-bound paclitaxel particles and methods of producing or administering the formulation. U.S. Patent No. 7,820,788 is commonly identified as a core Abraxane-related patent, with a patent term extending into the 2020s. Later patents and patent-term adjustments can create different effective dates for specific claims. Patent expiry must therefore be assessed claim by claim rather than by using one single “Abraxane expiry date.”
What patents protect Abraxane?
The patent estate has historically focused on the formulation and manufacturing platform rather than paclitaxel itself.
Formulation patents
The relevant claims generally concern:
- Paclitaxel particles associated with albumin.
- Particle-size characteristics.
- Solvent-free injectable suspensions.
- Albumin-bound delivery systems.
- Concentration and dosing parameters.
- Stability and reconstitution characteristics.
These patents matter because a generic manufacturer cannot necessarily rely on conventional paclitaxel chemistry alone to copy the product. It must develop a product that meets the FDA’s requirements for a complex injectable formulation while avoiding enforceable patent claims.
Manufacturing and process patents
Manufacturing barriers include:
- Production of reproducible nanoparticle suspensions.
- Control of particle size and aggregation.
- Sterile processing and lyophilization.
- Reconstitution performance.
- Batch-to-batch consistency.
- Scale-up of albumin-paclitaxel binding and filtration steps.
These process factors can delay generic entry even when regulatory exclusivity has expired. They also affect product quality, supply reliability, and hospital purchasing decisions.
Method-of-use patents
Method-of-use protection has been less commercially decisive than formulation protection. The main competitive value of Abraxane comes from its approved regimens and administration characteristics, while its core oncology indications are based on established clinical uses of paclitaxel. Method patents can still affect a generic’s labeling and carve-out strategy, but they do not create the same barrier as a broad formulation patent.
What is the Orange Book status of Abraxane?
Abraxane is listed in the FDA’s Orange Book as a prescription drug product with patent information submitted by the sponsor. The listed patents relate to the product’s formulation and associated intellectual property rather than to a novel paclitaxel molecule.
The Orange Book matters because an ANDA applicant seeking approval for a generic version must address listed patents through one of four certifications:
- Paragraph I: no patent information is listed.
- Paragraph II: the patent has expired.
- Paragraph III: the applicant will wait until patent expiration.
- Paragraph IV: the patent is invalid, unenforceable, or will not be infringed.
For Abraxane, Paragraph IV activity is commercially important because a successful challenge can enable earlier generic entry. The relevant risk is not the existence of an Orange Book listing alone. The decisive factors are the number of listed patents, claim scope, patent-term adjustment, litigation outcomes, and any settlement restricting launch.
Which companies are challenging Abraxane?
Generic competition has emerged for paclitaxel protein-bound particles. Teva has received FDA approval for a generic version of paclitaxel protein-bound particles for injectable suspension in the United States. The product is designed to compete directly with Abraxane in the 100 mg vial presentation.
The competitive field includes:
- Teva and other ANDA applicants pursuing generic nab-paclitaxel.
- Conventional paclitaxel suppliers, including large injectable-generic manufacturers.
- Docetaxel, which competes in several taxane-treated cancers.
- FOLFIRINOX and gemcitabine-based regimens in pancreatic cancer.
- Immunotherapy and targeted therapy combinations in selected lung and breast cancer settings.
Publicly reported litigation and settlement information must be tied to a particular ANDA, patent number, and court docket. Abraxane’s generic-entry risk is clear even where a single definitive “launch date” is not available from BMS financial disclosures.
What generic entry risks exist for Abraxane?
Generic entry creates greater risk for Abraxane than for many conventional cytotoxic products because the brand premium is linked to a complex formulation, not a unique active ingredient.
The principal risks are:
- Price erosion. Hospital systems and group purchasing organizations can shift volume toward lower-cost versions.
- Formulary substitution. Injectable oncology products are purchased through institutional channels where pharmacy committees and contracts influence share.
- Tender pressure outside the United States. National health systems often prioritize cost per dose.
- Reference-pricing pressure. Generic availability can affect reimbursement benchmarks even when physicians continue prescribing the branded product.
- Reduced negotiating leverage. BMS may need discounts to retain accounts.
- Manufacturing disruption. Shortages or quality events can accelerate switching among suppliers.
Generic penetration may be slower than for a simple oral tablet. Abraxane is a complex sterile injectable, and hospitals may require supplier qualification, clinical confidence, and reliable supply before broad adoption. That delay can moderate the first years of erosion, but it does not eliminate the long-term risk.
How does Abraxane compare with conventional paclitaxel?
| Attribute |
Abraxane |
Conventional paclitaxel |
| Active ingredient |
Paclitaxel |
Paclitaxel |
| Delivery system |
Albumin-bound nanoparticles |
Solvent-based formulation |
| Premedication |
Usually no routine solvent-related premedication |
Commonly required |
| Infusion profile |
Generally shorter |
Often longer |
| Formulation complexity |
High |
Lower |
| Generic competition |
Emerging complex generic competition |
Broad and established |
| Cost position |
Premium |
Lower-cost |
| Main commercial advantage |
Administration and formulation differentiation |
Price and availability |
Abraxane’s premium depends on whether the health system values reduced premedication, administration convenience, and formulation tolerability enough to offset its higher acquisition cost. In cost-sensitive markets, conventional paclitaxel remains a strong substitute.
How does Abraxane compare with competing pancreatic-cancer regimens?
In metastatic pancreatic cancer, Abraxane plus gemcitabine competes primarily with FOLFIRINOX and modified FOLFIRINOX. The choice depends on performance status, toxicity tolerance, neuropathy risk, age, comorbidities, local practice, and reimbursement.
| Regimen |
Competitive position |
| Abraxane plus gemcitabine |
Established first-line option, often considered when a gemcitabine-based regimen is preferred |
| FOLFIRINOX |
Strong efficacy profile but can involve substantial gastrointestinal, hematologic, and neurologic toxicity |
| Gemcitabine alone |
Lower-intensity option, generally used for less fit patients |
| Clinical trials |
Important for biomarker-defined or treatment-resistant disease |
Abraxane’s commercial defense is strongest where clinicians value a familiar regimen and where the product’s administration profile offsets the price premium. Its defense is weaker where hospitals use protocol-driven, low-cost chemotherapy purchasing.
What regulatory and manufacturing barriers protect Abraxane?
Abraxane is a complex injectable product. FDA approval requires more than demonstrating pharmaceutical equivalence for a simple small-molecule tablet. Applicants must address product quality, particle characteristics, sterility, stability, and clinical or pharmacologic comparability under the applicable regulatory pathway.
The principal barriers are:
- Complex formulation characterization.
- Sterile manufacturing at commercial scale.
- Analytical demonstration of comparable particle attributes.
- Reconstitution and infusion performance.
- Supply of high-quality human albumin.
- Control of aggregation and stability.
- Consistent clinical dosing and labeling.
These barriers give BMS some protection against rapid commoditization. They do not provide permanent insulation because the market has already demonstrated that competitors can develop approved alternatives.
What licensing deals shaped Abraxane’s commercial history?
The product’s commercial ownership changed through corporate transactions rather than a major current licensing arrangement:
- Abraxis BioScience developed and commercialized Abraxane.
- Celgene acquired Abraxis in 2010 for approximately $2.9 billion.
- Bristol Myers Squibb acquired Celgene in 2019 in a transaction valued at approximately $74 billion.
The Celgene acquisition transferred Abraxane to BMS together with Celgene’s oncology portfolio. That transaction gave Abraxane access to BMS’s global commercial infrastructure, but it also placed the product within a portfolio increasingly focused on higher-growth immuno-oncology and specialty medicines.
What litigation and settlement issues affect Abraxane?
Abraxane litigation risk centers on ANDA challenges and the enforceability of formulation or manufacturing patents. The commercial consequences depend on whether a court:
- Upholds the asserted claims.
- Finds the claims invalid.
- Finds non-infringement.
- Allows an at-risk launch.
- Approves a settlement with a delayed generic-entry date.
Patent settlements can preserve branded revenue for a defined period while giving the generic applicant a negotiated launch date. The financial value of such a settlement depends on U.S. sales, expected erosion, the number of generic entrants, and the remaining patent term.
BMS’s public financial reports do not provide a complete standalone litigation valuation for Abraxane. The market should therefore treat patent settlements as potential timing events rather than as evidence that the product has regained long-term exclusivity.
What is Abraxane’s geographic coverage?
Abraxane has been marketed in the United States and international markets under BMS and predecessor-company commercialization arrangements. Geographic value varies substantially:
- The United States has historically generated the greatest revenue and the highest branded pricing.
- Europe applies national reimbursement and health-technology assessment controls.
- Japan and other Asian markets have distinct approval, pricing, and distribution structures.
- Emerging markets place greater emphasis on procurement cost and may favor conventional paclitaxel.
The U.S. market remains the principal driver of patent value because Orange Book listings and Paragraph IV litigation are U.S.-specific mechanisms. International erosion can occur through local patent expiry, compulsory pricing, tender procurement, and local generic approvals even when U.S. protection remains active.
How strong is the Abraxane patent estate?
Abraxane has a moderate, declining patent position.
Its strengths are:
- A complex albumin-bound formulation.
- Manufacturing know-how that is difficult to replicate at scale.
- Established clinical use in three major oncology indications.
- Hospital familiarity and a large installed prescriber base.
- Regulatory and quality barriers for complex injectables.
Its weaknesses are:
- Paclitaxel is an old, widely available active ingredient.
- Regulatory exclusivity has expired.
- Core patent protection is moving through the 2020s.
- Generic nab-paclitaxel has reached the U.S. market.
- Conventional paclitaxel and other taxanes provide low-cost substitutes.
- BMS has not positioned Abraxane as a central growth engine comparable with newer immuno-oncology products.
The estate is more defensible than a conventional paclitaxel brand with no formulation differentiation, but less durable than a product protected by composition-of-matter patents extending well beyond the current decade.
What generic launch scenarios are most likely?
Scenario 1: Controlled erosion
One or two generic manufacturers enter, but adoption is gradual because hospitals qualify suppliers cautiously. Abraxane retains meaningful share through clinical familiarity and reliable supply. Net sales decline steadily rather than collapse.
Scenario 2: Accelerated U.S. substitution
Multiple suppliers enter, payers and group purchasing organizations prioritize price, and BMS discounts the brand to preserve volume. Revenue falls rapidly, with the largest impact in high-volume pancreatic-cancer centers.
Scenario 3: Supply-constrained generic penetration
Generic approval occurs, but manufacturing capacity, albumin supply, or quality issues limit availability. BMS retains temporary share, although long-term pricing pressure remains.
The most likely outcome for a complex oncology injectable is usually staged erosion rather than an immediate 90% decline. The pace depends on the number of approved suppliers and the extent of institutional substitution.
What is the outlook for Abraxane revenue?
Abraxane should be treated as a mature cash-generating oncology product rather than a growth asset. The main revenue drivers are:
- U.S. generic penetration.
- Net price after rebates and contracting.
- Pancreatic-cancer treatment volume.
- Hospital chemotherapy utilization.
- Supply reliability.
- BMS’s willingness to defend share through discounts.
- Competition from FOLFIRINOX, conventional paclitaxel, and other taxanes.
The product can remain financially material because annual revenue near $1 billion creates a large base even after moderate erosion. The strategic question is whether BMS can preserve margin, not whether Abraxane can return to its prior growth trajectory.
Key Takeaways
- Abraxane is an albumin-bound paclitaxel formulation used in breast, lung, and pancreatic cancers.
- Sales expanded sharply after the 2013 pancreatic-cancer approval and reached approximately $1 billion or more annually.
- Regulatory exclusivity has expired, and patent protection is moving through the 2020s.
- The core defense is formulation complexity, manufacturing know-how, and clinical familiarity.
- Teva and other generic manufacturers create direct nab-paclitaxel competition.
- Conventional paclitaxel remains a strong lower-cost substitute.
- Abraxane is not exposed to biosimilar competition because it is a non-biologic drug.
- The most likely financial path is gradual-to-accelerating erosion, depending on generic uptake and hospital contracting.
- BMS’s Abraxane exposure is material but strategically secondary to its newer oncology growth products.
FAQs About Abraxane Patent Expiry, Generics, and Market Competition
Is Abraxane the same as paclitaxel?
Abraxane contains paclitaxel but uses an albumin-bound nanoparticle formulation. Conventional paclitaxel uses a solvent-based formulation. The products have different administration requirements, formulation characteristics, and pricing.
Does Abraxane require steroid premedication?
Abraxane generally does not require the routine solvent-related premedication associated with conventional paclitaxel. The final decision depends on the clinical regimen and patient-specific factors.
Is there a generic version of Abraxane?
Yes. FDA-approved generic paclitaxel protein-bound particles have entered the U.S. market, creating direct competition with Abraxane.
Can a biosimilar replace Abraxane?
No. Abraxane is not a biologic. Competition proceeds through generic-drug and complex-injectable pathways rather than the biosimilar pathway.
What is the biggest commercial risk to Abraxane?
The largest risk is institutional substitution after generic nab-paclitaxel entry. Lower-priced generic products can reduce both Abraxane volume and net price, particularly in hospital and group-purchasing channels.
References
-
Bristol Myers Squibb. (2024). 2023 annual report. Bristol Myers Squibb Company.
-
Celgene Corporation. (2019). 2018 annual report. Celgene Corporation.
-
U.S. Food and Drug Administration. (2023). Abraxane prescribing information. U.S. Department of Health and Human Services.
-
U.S. Food and Drug Administration. (2024). Approved drug products with therapeutic equivalence evaluations: Orange Book. U.S. Department of Health and Human Services.
-
Von Hoff, D. D., Ervin, T., Arena, F. P., Chiorean, E. G., Infante, J., Moore, M., Seay, T., Tjulandin, S., Ma, W. W., Saleh, M. N., Harris, M., Reni, M., Dowden, S., Laheru, D., Bahary, N., Ramanathan, R. K., Tabernero, J., Hidalgo, M., Goldstein, D., ... Chen, L. T. (2013). Increased survival in pancreatic cancer with nab-paclitaxel plus gemcitabine. New England Journal of Medicine, 369(18), 1691-1703. https://doi.org/10.1056/NEJMoa1304369