SINUVA Drug Patent Profile
✉ Email this page to a colleague
When do Sinuva patents expire, and what generic alternatives are available?
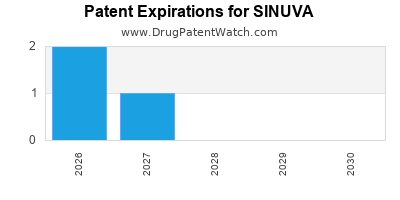
Sinuva is a drug marketed by Intersect Ent Inc and is included in one NDA. There are seven patents protecting this drug.
The generic ingredient in SINUVA is mometasone furoate. There is one drug master file entry for this compound. Twenty-seven suppliers are listed for this compound. Additional details are available on the mometasone furoate profile page.
DrugPatentWatch® Litigation and Generic Entry Outlook for Sinuva
A generic version of SINUVA was approved as mometasone furoate by PADAGIS US on March 18th, 2002.
AI Deep Research
Questions you can ask:
- What is the 5 year forecast for SINUVA?
- What are the global sales for SINUVA?
- What is Average Wholesale Price for SINUVA?
Summary for SINUVA
| US Patents: | 7 |
| Applicants: | 1 |
| NDAs: | 1 |
| Finished Product Suppliers / Packagers: | 1 |
| Raw Ingredient (Bulk) Api Vendors: | 78 |
| Patent Applications: | 6,076 |
| Drug Prices: | Drug price information for SINUVA |
| What excipients (inactive ingredients) are in SINUVA? | SINUVA excipients list |
| DailyMed Link: | SINUVA at DailyMed |

Pharmacology for SINUVA
| Drug Class | Corticosteroid |
| Mechanism of Action | Corticosteroid Hormone Receptor Agonists |
US Patents and Regulatory Information for SINUVA
SINUVA is protected by seven US patents.
| Applicant | Tradename | Generic Name | Dosage | NDA | Approval Date | TE | Type | RLD | RS | Patent No. | Patent Expiration | Product | Substance | Delist Req. | Exclusivity Expiration |
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | RX | Yes | Yes | 8,025,635 | ⤷ Start Trial | Y | ⤷ Start Trial | |||
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | RX | Yes | Yes | 8,763,222 | ⤷ Start Trial | Y | ⤷ Start Trial | |||
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | RX | Yes | Yes | 9,585,681 | ⤷ Start Trial | ⤷ Start Trial | ||||
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | RX | Yes | Yes | 10,232,152 | ⤷ Start Trial | Y | ⤷ Start Trial | |||
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | RX | Yes | Yes | 10,357,640 | ⤷ Start Trial | ⤷ Start Trial | ||||
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | RX | Yes | Yes | 10,406,332 | ⤷ Start Trial | Y | ⤷ Start Trial | |||
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | RX | Yes | Yes | 7,544,192 | ⤷ Start Trial | ⤷ Start Trial | ||||
| >Applicant | >Tradename | >Generic Name | >Dosage | >NDA | >Approval Date | >TE | >Type | >RLD | >RS | >Patent No. | >Patent Expiration | >Product | >Substance | >Delist Req. | >Exclusivity Expiration |
Expired US Patents for SINUVA
| Applicant | Tradename | Generic Name | Dosage | NDA | Approval Date | Patent No. | Patent Expiration |
|---|---|---|---|---|---|---|---|
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | 7,662,141 | ⤷ Start Trial |
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | 9,585,681 | ⤷ Start Trial |
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | 7,951,131 | ⤷ Start Trial |
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | 7,951,130 | ⤷ Start Trial |
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | 7,951,133 | ⤷ Start Trial |
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | 7,713,255 | ⤷ Start Trial |
| Intersect Ent Inc | SINUVA | mometasone furoate | IMPLANT;IMPLANTATION | 209310-001 | Dec 8, 2017 | 8,109,918 | ⤷ Start Trial |
| >Applicant | >Tradename | >Generic Name | >Dosage | >NDA | >Approval Date | >Patent No. | >Patent Expiration |
International Patents for SINUVA
See the table below for patents covering SINUVA around the world.
| Country | Patent Number | Title | Estimated Expiration |
|---|---|---|---|
| Australia | 2014236729 | ⤷ Start Trial | |
| Australia | 2019201045 | ⤷ Start Trial | |
| Canada | 2903848 | ⤷ Start Trial | |
| China | 105188831 | ⤷ Start Trial | |
| China | 112089505 | ⤷ Start Trial | |
| European Patent Office | 2968877 | ⤷ Start Trial | |
| European Patent Office | 3636227 | ⤷ Start Trial | |
| >Country | >Patent Number | >Title | >Estimated Expiration |
Supplementary Protection Certificates for SINUVA
| Patent Number | Supplementary Protection Certificate | SPC Country | SPC Expiration | SPC Description |
|---|---|---|---|---|
| 0112669 | 96C0002 | Belgium | ⤷ Start Trial | PRODUCT NAME: MOMETASONE FUROATE; NAT. REGISTRATION NO/DATE: NL 19601 19950919; FIRST REGISTRATION: GR - 10681/89 19900622 |
| 0548114 | SPC/GB97/064 | United Kingdom | ⤷ Start Trial | PRODUCT NAME: MOMETASONE FUROATE MONOHYDRATE; REGISTERED: FR AMM 343012.6 19970219; UK 00201/0216 19970410 |
| 3043773 | 132021000000191 | Italy | ⤷ Start Trial | PRODUCT NAME: MOMETASONE O UN SUO SALE E OLOPATADINA O UN SUO SALE(RYALTRIS); AUTHORISATION NUMBER(S) AND DATE(S): 048499014, 048499026, 048499038, 20210726;140638, 20210426 |
| 3043773 | 2022C/520 | Belgium | ⤷ Start Trial | PRODUCT NAME: MOMETASONE OF EEN ZOUT HIERVAN EN OLOPATADINE OF EEN ZOUT HIERVAN; AUTHORISATION NUMBER AND DATE: BE595626 20220203 |
| 3043773 | 21C1057 | France | ⤷ Start Trial | PRODUCT NAME: MOMETASONE OU L'UN DE SES SELS AVEC OLOPATADINE OU L'UN DE SES SELS; NAT. REGISTRATION NO/DATE: NL52121 20211026; FIRST REGISTRATION: AT - 140638 20210426 |
| 3043773 | 2190041-0 | Sweden | ⤷ Start Trial | PRODUCT NAME: MOMETASONE OR A SALT THEREOF AND OLOPATADINE OR A SALT THEREOF; NAT. REG. NO/DATE: MT NR 60226 20210519; FIRST REG.: AT APPROVAL NR 140638 20210426 |
| 3043773 | SPC/GB21/077 | United Kingdom | ⤷ Start Trial | PRODUCT NAME: MOMETASONE OR A SALT THEREOF AND OLOPATADINE OR A SALT THEREOF; REGISTERED: AT 140638 20210426; UK PL 25258/0331 - 0001 20210511 |
| >Patent Number | >Supplementary Protection Certificate | >SPC Country | >SPC Expiration | >SPC Description |
SINUVA (mifepristone intravaginal gel) market dynamics and financial trajectory: sales runway, payer uptake, exclusivity and generic entry pressure
More… ↓
Make Better Decisions: Try a trial or see plans & pricing
Drugs may be covered by multiple patents or regulatory protections. All trademarks and applicant names are the property of their respective owners or licensors. Although great care is taken in the proper and correct provision of this service, thinkBiotech LLC does not accept any responsibility for possible consequences of errors or omissions in the provided data. The data presented herein is for information purposes only. There is no warranty that the data contained herein is error free. We do not provide individual investment advice. This service is not registered with any financial regulatory agency. The information we publish is educational only and based on our opinions plus our models. By using DrugPatentWatch you acknowledge that we do not provide personalized recommendations or advice. thinkBiotech performs no independent verification of facts as provided by public sources nor are attempts made to provide legal or investing advice. Any reliance on data provided herein is done solely at the discretion of the user. Users of this service are advised to seek professional advice and independent confirmation before considering acting on any of the provided information. thinkBiotech LLC reserves the right to amend, extend or withdraw any part or all of the offered service without notice.
ISSN: 2162-2639

Privacy and Cookies
Terms & Conditions
Site Map
DrugPatentWatch Alternatives
LOE / Major Patent Expirations 2026 - 2027
NCE-1 Patent Challenge Dates 2026 - 2027
Friedman, Yali. "DrugPatentWatch" DrugPatentWatch, thinkBiotech, 2026, www.DrugPatentWatch.com.
See Primary Research Papers Citing DrugPatentWatch