Last updated: November 7, 2026
Rivastigmine is a mature acetylcholinesterase inhibitor used for mild-to-moderate Alzheimer’s dementia and Parkinson’s disease dementia. Its commercial trajectory is defined by broad generic availability for capsules and oral solution, declining branded sales for Exelon, and a later transition to generic transdermal patches. The patch remains the most commercially differentiated formulation because it improves adherence and reduces gastrointestinal exposure, but its market protection has also eroded.
No reliable public source reports current global rivastigmine sales as a standalone product. Financial analysis therefore depends on historical Exelon disclosures, prescription volume, generic pricing, formulation mix, and market-share data from commercial databases.
What is rivastigmine and how large is its addressable market?
Rivastigmine is a reversible inhibitor of acetylcholinesterase and butyrylcholinesterase. It is marketed in oral capsules, oral solution, and transdermal patches. The drug is approved for:
- Mild-to-moderate Alzheimer’s dementia.
- Mild-to-moderate dementia associated with Parkinson’s disease.
- Transdermal treatment of mild-to-moderate Alzheimer’s dementia and Parkinson’s disease dementia in the United States.
The FDA approved Exelon capsules and oral solution in 2000. The Exelon Patch was approved in 2007. The patch uses a once-daily delivery system, while oral products are generally administered twice daily after dose titration.[1][2]
Rivastigmine product forms
| Formulation |
Typical strengths |
Commercial role |
Competitive position |
| Capsules |
1.5 mg, 3 mg, 4.5 mg, 6 mg |
Low-cost oral treatment |
Highly commoditized |
| Oral solution |
2 mg/mL |
Patients with swallowing or titration needs |
Narrower niche |
| Transdermal patch |
4.6, 9.5, and 13.3 mg/24 hours |
Adherence and tolerability segment |
Higher value than oral generics |
| Brand Exelon |
Same active ingredient |
Original innovator product |
Limited pricing power after generic entry |
The addressable patient population is large because dementia prevalence is increasing, but rivastigmine competes with donepezil, galantamine, memantine, combination products, and newer disease-modifying Alzheimer’s medicines. The drug is symptomatic therapy and does not modify the underlying progression of Alzheimer’s disease.
How does rivastigmine compare with competing Alzheimer’s drugs?
Rivastigmine competes primarily on formulation and tolerability rather than superior efficacy.
| Drug |
Mechanism |
Main formulation advantage |
Generic status |
Commercial implication |
| Rivastigmine |
Acetylcholinesterase and butyrylcholinesterase inhibition |
Patch avoids some oral gastrointestinal exposure |
Generic oral and patch products available |
Price erosion with residual patch niche |
| Donepezil |
Acetylcholinesterase inhibition |
Once-daily tablets and orally disintegrating tablets |
Generic |
Major low-cost competitor |
| Galantamine |
Acetylcholinesterase inhibition and nicotinic modulation |
Extended-release capsule |
Generic |
Competes in oral maintenance therapy |
| Memantine |
NMDA receptor antagonism |
Tablets, solution, extended release |
Generic |
Often used in moderate-to-severe disease |
| Lecanemab |
Anti-amyloid monoclonal antibody |
Disease-modifying treatment for selected patients |
Biologic, no biosimilar competition currently |
Expands treatment segmentation but does not directly replace rivastigmine for all patients |
Rivastigmine’s patch can be selected when caregivers have difficulty administering twice-daily oral therapy or when oral tolerability is poor. Donepezil remains the major generic benchmark because of its low price, simple dosing, and broad clinical familiarity.
What patents protect Exelon and generic rivastigmine products?
The core compound and early oral formulation protections have expired in the United States. The principal remaining commercial issue was protection around the transdermal delivery system, not the active pharmaceutical ingredient.
Core patent and regulatory timeline
| Event |
Approximate date |
Commercial effect |
| Rivastigmine development and original patent filings |
1980s-1990s |
Established compound and formulation rights |
| FDA approval of Exelon capsules and oral solution |
2000 |
Launched branded oral market |
| FDA approval of Exelon Patch |
2007 |
Created differentiated transdermal segment |
| U.S. oral generic entry |
2010s |
Rapid erosion of oral brand value |
| U.S. patch patent disputes and regulatory challenges |
Late 2010s-early 2020s |
Delayed or shaped generic patch entry |
| U.S. generic transdermal approvals |
2020s |
Reduced remaining patch exclusivity |
| Current market |
2020s |
Primarily generic, with residual branded and formulation-based demand |
The Orange Book should be used for the current list of patents and regulatory exclusivities because listed patents, expiration dates, pediatric extensions, and delisting status can change over time.[3] Historical Exelon labeling identifies the patch as a transdermal system containing rivastigmine and describes the dose-delivery profile that generic manufacturers had to replicate.[2]
What formulations are protected by rivastigmine patents?
The commercially important formulation claims relate to:
- Transdermal delivery of rivastigmine.
- Patch composition and drug-in-adhesive architecture.
- Controlled delivery over approximately 24 hours.
- Adhesive performance and drug stability.
- Dose strengths corresponding to the Exelon Patch product line.
The practical barrier is not only patent protection. A patch applicant also must demonstrate pharmaceutical equivalence and bioequivalence under the FDA’s abbreviated new drug application pathway. Adhesion, residual drug, release characteristics, and skin exposure can complicate development relative to capsules.
When did rivastigmine lose exclusivity?
Rivastigmine lost meaningful oral exclusivity before the end of the 2010s. The Exelon Patch retained a later commercial window because the transdermal product relied on formulation and delivery-system protection.
The exclusivity profile is best divided into three periods:
- Original oral franchise: Protected by compound, formulation, and regulatory exclusivities that expired before the current decade.
- Patch-led brand period: Maintained by transdermal differentiation, formulation patents, and the higher technical burden of patch development.
- Generic patch period: Began after FDA approval of competing transdermal products, leaving brand Exelon with limited pricing and volume support.
Rivastigmine has no current biologic exclusivity period and no biosimilar framework. It is a small-molecule product regulated through abbreviated new drug applications.
What is the Orange Book status of Exelon and rivastigmine?
Exelon is an FDA-approved reference-listed drug. The relevant Orange Book analysis separates active ingredient, dosage form, strength, and route.
For commercial diligence, the key questions are:
- Whether any patent remains listed for the specific Exelon dosage form.
- Whether a listed patent covers capsules, oral solution, or transdermal systems.
- Whether a generic applicant filed a Paragraph IV certification.
- Whether the reference sponsor sued within the 45-day statutory period.
- Whether any 30-month stay, preliminary injunction, settlement, or launch restriction applied.
- Whether pediatric exclusivity or other regulatory exclusivity remains active.
The original oral products are generally treated as off-patent generic products. The patch required more detailed Orange Book and litigation review because listed patents could affect the timing of abbreviated new drug application approvals.
Which companies challenged Exelon patents and entered the rivastigmine market?
Rivastigmine has attracted multiple generic manufacturers because the oral products are straightforward to manufacture and the patch has a large established reference market.
Potential and actual generic participants have included companies such as:
- Amneal Pharmaceuticals.
- Teva Pharmaceutical Industries.
- Dr. Reddy’s Laboratories.
- Zydus Pharmaceuticals.
- Alembic Pharmaceuticals.
- Mylan and related Viatris entities.
- Other regional and contract manufacturers.
The relevant challenge mechanism is the Paragraph IV certification under the Hatch-Waxman Act. A generic applicant can assert that an Orange Book patent is invalid, unenforceable, or not infringed. The innovator may then file an infringement action, triggering a statutory approval stay in certain circumstances.
Publicly available information indicates that the commercial contest centered more heavily on generic patch approvals and patent positions than on the oral capsules, where generic competition was already established. Exact current litigation posture must be read from FDA approval records, Orange Book entries, and federal court dockets rather than inferred from historical patent listings.
What is the FDA regulatory status of rivastigmine?
Rivastigmine is an established FDA-approved small molecule. It does not depend on biologic licensing or a biosimilar pathway.
Regulatory characteristics
| Regulatory issue |
Rivastigmine status |
| New drug application |
Exelon approved through an NDA |
| Generic pathway |
ANDA under Hatch-Waxman |
| Reference product |
Exelon capsules, oral solution, and patch |
| Biosimilar pathway |
Not applicable |
| Pediatric exclusivity |
Not a major current commercial driver |
| Controlled substance status |
Not controlled |
| Primary safety limitations |
Nausea, vomiting, weight loss, bradycardia, skin reactions with patch |
| Key administration issue |
Dose titration and adherence |
The patch label includes important administration requirements, including rotation of application sites and removal of the prior patch before applying a new one.[2] These instructions create product-use risks that can affect adherence, caregiver burden, and patient persistence.
How strong is the rivastigmine patent estate?
The current estate is commercially weak for the active ingredient and oral products but stronger for specialized delivery technology.
Patent-strength assessment
| Patent category |
Current strength |
Commercial relevance |
| Composition of matter |
Expired |
No meaningful barrier |
| Oral tablet or capsule claims |
Expired or largely exhausted |
Generic competition is entrenched |
| Oral solution claims |
Limited |
Small niche, low barrier |
| Transdermal formulation |
Historically meaningful, now eroded |
Supported delayed generic entry |
| Manufacturing process claims |
Variable |
May affect individual suppliers but rarely supports broad market exclusivity |
| Device or adhesive claims |
Potentially relevant |
Can create formulation-specific litigation |
| Method-of-use claims |
Limited value after core disease indications became generic |
May support narrow labeling positions |
Method-of-use patents are less important for rivastigmine than formulation patents because Alzheimer’s and Parkinson’s dementia uses are well established and generic labels can often rely on the same approved indications after patent resolution.
What generic launch risks exist for rivastigmine?
The principal launch risk is not whether generic competition will occur. It is how quickly price erosion will spread across formulations and whether patch supply will be stable.
Oral product risks
Generic capsules and oral solution face:
- Low clinical differentiation.
- Multiple approved suppliers.
- Pharmacy substitution.
- Contracting pressure from wholesalers and health plans.
- Low barriers to switching.
- Potential manufacturing concentration.
Oral rivastigmine is therefore a low-margin market unless a supplier has a cost advantage, reliable API access, or a differentiated presentation.
Patch product risks
Generic patches face a more complex risk profile:
- Adhesion failures.
- Skin tolerability problems.
- Manufacturing yield losses.
- Regulatory scrutiny of drug release and exposure.
- Limited reimbursement separation from cheaper oral therapy.
- Brand loyalty among caregivers and prescribers.
- Potential supply interruptions if only a few patch manufacturers remain.
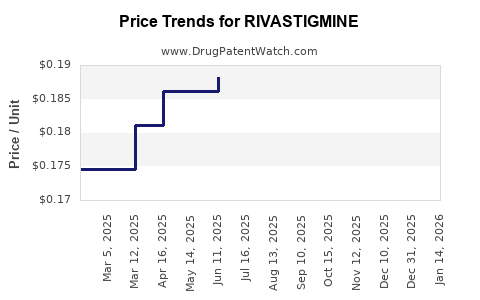
The patch can preserve higher net pricing than oral capsules, but the difference narrows as payers place generic patches on preferred formularies.
How has rivastigmine affected Novartis financial performance?
Exelon was a meaningful Novartis product before generic erosion, but it is no longer a material standalone growth driver for the company. Novartis historically reported Exelon within its pharmaceutical product portfolio rather than as a continuously disclosed independent business segment. Later annual reports emphasize major growth products such as Entresto, Cosentyx, Kisqali, Kesimpta, and Pluvicto, while mature products such as Exelon contribute little to group-level growth.[4]
Financial trajectory
| Period |
Financial direction |
Main driver |
| 2000-2007 |
Growth |
Oral launch and disease prevalence |
| 2007-2011 |
Expansion |
Patch launch and premium formulation |
| 2012-2016 |
Decline |
Oral generic entry and price erosion |
| 2017-2020 |
Further decline |
Mature patch franchise and payer pressure |
| 2021-present |
Low, largely residual brand contribution |
Generic patch competition and limited innovation |
The loss of exclusivity changed Exelon from a branded growth asset into a mature product with residual sales. Novartis’s financial exposure is now limited relative to the company’s overall revenue base. The larger economic opportunity sits with generic manufacturers that can supply the patch at scale, not with the originator.
What licensing deals affect rivastigmine?
No major current licensing transaction is widely associated with rivastigmine as a strategic growth asset. The product’s licensing history is primarily connected with historical development, regional commercialization, and generic manufacturing arrangements rather than current high-value business development.
Potential commercial arrangements include:
- Regional rights to market generic capsules or solution.
- Contract manufacturing for transdermal systems.
- API supply agreements.
- Technology transfer for patch manufacturing.
- Authorized-generic or co-marketing structures.
These arrangements are generally private or reported at product-portfolio level. They do not create a valuation framework comparable with licensing deals for oncology drugs, gene therapies, or biologics.
What is the competitive landscape for rivastigmine?
The market is split between low-cost oral generics and a smaller patch segment.
Competitive factors
Price: Oral products have the lowest acquisition cost and face the strongest substitution pressure.
Adherence: The patch has a practical advantage for patients who struggle with twice-daily dosing.
Tolerability: Transdermal administration can reduce peak-related gastrointestinal effects, although the patch introduces local skin reactions.
Distribution: Retail pharmacy and mail-order channels favor products with multiple interchangeable suppliers.
Manufacturing: Patch production is more technically demanding than capsule production, which can limit the number of reliable suppliers.
Clinical substitution: Donepezil is a strong substitute because it is inexpensive, familiar, and available in multiple dosage forms.
What is the geographic coverage of rivastigmine patents and competition?
Rivastigmine’s original patent estate has expired in major markets, including the United States and Europe. Generic availability is broad across North America, Europe, and many emerging markets.
Geographic differences remain in:
- Patch launch timing.
- National reimbursement.
- Reference-pricing systems.
- Patent-term extensions.
- Regulatory requirements for transdermal equivalence.
- Local manufacturing and procurement rules.
The United States remains important because of its large branded pharmaceutical market and formal Orange Book and Paragraph IV system. Europe is more heavily shaped by national reimbursement and tendering. Emerging markets tend to emphasize price and local supply, reducing the value of brand positioning.
What manufacturing and intellectual-property barriers remain?
The active ingredient is not the principal barrier. The main barriers are operational.
Manufacturing barriers
- Consistent drug loading in adhesive matrices.
- Stable adhesion across temperature and humidity conditions.
- Control of crystallization and drug release.
- Packaging that preserves patch performance.
- Sufficient production capacity for multiple strengths.
- Quality control for residual drug and release rate.
- Reliable sourcing of pharmaceutical-grade rivastigmine API.
Intellectual-property barriers
- Patch composition claims.
- Drug-in-adhesive architecture.
- Delivery-rate limitations.
- Adhesive and backing-layer designs.
- Manufacturing methods that avoid existing claims.
- Device-specific claims in certain jurisdictions.
These barriers can support temporary supply advantages but are unlikely to restore broad, long-term exclusivity for the molecule.
What is the outlook for rivastigmine revenue?
Rivastigmine revenue is likely to remain stable to declining in nominal terms, with growth in patient volume offset by lower prices. The patch provides the strongest remaining commercial segment, but it is unlikely to recreate the original Exelon revenue profile.
The base-case market outlook is:
- Continued decline in branded Exelon sales.
- Persistent generic dominance for capsules and oral solution.
- Increasing generic share of transdermal prescriptions.
- Stable demand from the aging population.
- Downward net pricing.
- Limited originator investment.
- Selective opportunity for efficient patch manufacturers.
- No meaningful biosimilar-driven disruption because rivastigmine is a small molecule.
For investors, the product is a mature generic-market opportunity rather than a branded innovation asset. For generic companies, patch manufacturing capability is more valuable than compound ownership. For licensors, the most relevant assets are transdermal technology, manufacturing know-how, and regional distribution rather than core rivastigmine patents.
Key Takeaways
- Rivastigmine is an off-patent small-molecule Alzheimer’s and Parkinson’s dementia therapy.
- Oral capsules and oral solution are highly commoditized.
- The transdermal patch is the principal differentiated formulation.
- Exelon’s historical revenue declined after oral generic entry and later patch competition.
- No biosimilar risk applies; all competition proceeds through conventional generic pathways.
- Paragraph IV litigation was more relevant to the patch than to oral products.
- Current commercial value lies in reliable patch manufacturing, supply continuity, and low-cost distribution.
- Novartis has limited remaining financial exposure to rivastigmine relative to its major growth products.
- Market revenue should remain supported by dementia prevalence but constrained by generic price erosion.
FAQs
Is rivastigmine still under patent?
The core compound and oral products are no longer protected by meaningful U.S. exclusivity. Historical patent protection for the transdermal patch delayed generic competition but has substantially eroded.
Is the rivastigmine patch generic?
Yes. Generic transdermal rivastigmine products have entered the market in the 2020s, although availability can vary by country, strength, supplier, and pharmacy channel.
Does rivastigmine have biosimilar competition?
No. Rivastigmine is a small-molecule drug. Competitors file abbreviated new drug applications, not biosimilar applications.
Which rivastigmine formulation has the highest commercial value?
The transdermal patch has the highest differentiation and manufacturing complexity. Capsules have the largest generic substitution risk and the lowest pricing power.
Can generic rivastigmine be launched before all Exelon patents expire?
A Paragraph IV certification can permit an applicant to challenge listed patents before their expiration. Launch timing depends on litigation, statutory stays, court decisions, settlements, and the final FDA approval status.
References
-
U.S. Food and Drug Administration. (2000). Exelon approval history and prescribing information. FDA.
-
U.S. Food and Drug Administration. (2023). Exelon (rivastigmine transdermal system) prescribing information. FDA.
-
U.S. Food and Drug Administration. (2024). Approved drug products with therapeutic equivalence evaluations: Orange Book. FDA.
-
Novartis AG. (2024). Annual report 2023. Novartis.
-
National Institute on Aging. (2024). How is Alzheimer’s disease treated? U.S. Department of Health and Human Services.
-
U.S. Food and Drug Administration. (1984). Drug Price Competition and Patent Term Restoration Act. FDA.