Share This Page
NIMODIPINE Drug Patent Profile
✉ Email this page to a colleague
When do Nimodipine patents expire, and when can generic versions of Nimodipine launch?
Nimodipine is a drug marketed by Bionpharma, Heritage, Sofgen Pharms, Sun Pharm Inds Inc, Thepharmanetwork Llc, Alkem Labs Ltd, and Annora Pharma. and is included in seven NDAs.
The generic ingredient in NIMODIPINE is nimodipine. There is one drug master file entry for this compound. Four suppliers are listed for this compound. Additional details are available on the nimodipine profile page.
DrugPatentWatch® Litigation and Generic Entry Outlook for Nimodipine
A generic version of NIMODIPINE was approved as nimodipine by HERITAGE on May 2nd, 2007.
AI Deep Research
Questions you can ask:
- What is the 5 year forecast for NIMODIPINE?
- What are the global sales for NIMODIPINE?
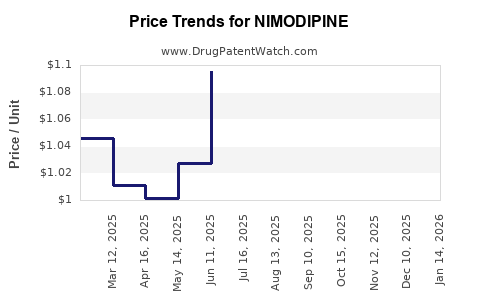
- What is Average Wholesale Price for NIMODIPINE?
Summary for NIMODIPINE
Recent Clinical Trials for NIMODIPINE
Identify potential brand extensions & 505(b)(2) entrants
| Sponsor | Phase |
|---|---|
| Nebraska Methodist Health System | PHASE3 |
| Centre Hospitalier St Anne | PHASE3 |
| Yale University | PHASE2 |
Pharmacology for NIMODIPINE
| Drug Class | Dihydropyridine Calcium Channel Blocker |
| Mechanism of Action | Calcium Channel Antagonists |
Medical Subject Heading (MeSH) Categories for NIMODIPINE
Anatomical Therapeutic Chemical (ATC) Classes for NIMODIPINE
Paragraph IV (Patent) Challenges for NIMODIPINE
| Tradename | Dosage | Ingredient | Strength | NDA | ANDAs Submitted | Submissiondate |
|---|---|---|---|---|---|---|
| NYMALIZE | Oral Solution | nimodipine | 6 mg/mL | 203340 | 1 | 2021-11-29 |
US Patents and Regulatory Information for NIMODIPINE
| Applicant | Tradename | Generic Name | Dosage | NDA | Approval Date | TE | Type | RLD | RS | Patent No. | Patent Expiration | Product | Substance | Delist Req. | Exclusivity Expiration |
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Bionpharma | NIMODIPINE | nimodipine | CAPSULE;ORAL | 076740-001 | Jan 17, 2008 | AB | RX | No | Yes | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | |||
| Annora Pharma | NIMODIPINE | nimodipine | SOLUTION;ORAL | 216937-001 | Jul 9, 2024 | RX | No | Yes | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | ||||
| Sun Pharm Inds Inc | NIMODIPINE | nimodipine | CAPSULE;ORAL | 077067-001 | Apr 17, 2007 | DISCN | No | No | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | ||||
| Heritage | NIMODIPINE | nimodipine | CAPSULE;ORAL | 077811-001 | May 2, 2007 | AB | RX | No | No | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | |||
| >Applicant | >Tradename | >Generic Name | >Dosage | >NDA | >Approval Date | >TE | >Type | >RLD | >RS | >Patent No. | >Patent Expiration | >Product | >Substance | >Delist Req. | >Exclusivity Expiration |
Nimodipine Market Dynamics and Financial Trajectory
Nimodipine is a mature, low-growth calcium-channel blocker used primarily to reduce the incidence and severity of neurological deficits after subarachnoid hemorrhage caused by ruptured intracranial aneurysms. Its commercial profile is defined by generic competition, limited treatment volume, hospital-focused demand and minimal remaining patent protection. Revenue growth is unlikely to come from price expansion or patent exclusivity. The main commercial variables are diagnosis rates, neurocritical-care utilization, supplier continuity, formulation access and regional reimbursement.
What is nimodipine used for and how large is the addressable market?
Nimodipine is approved in the United States for improving neurological outcomes in patients with subarachnoid hemorrhage from ruptured intracranial berry aneurysms. The standard dose is 60 mg orally every four hours for 21 consecutive days, initiated within 96 hours of the hemorrhage.[1]
The drug does not treat the aneurysm itself. Its value is concentrated in the prevention or reduction of delayed cerebral ischemia and associated neurological deficits after hemorrhage. Treatment is generally initiated in hospitals and continued after discharge only when the 21-day course extends beyond the inpatient stay.
The addressable market is therefore narrower than the broader calcium-channel blocker market.
| Market characteristic | Nimodipine impact |
|---|---|
| Primary disease | Aneurysmal subarachnoid hemorrhage |
| Treatment setting | Hospital and neurocritical-care unit |
| Typical course | 21 days |
| Chronic use | Not standard |
| Main dosage form | 30 mg oral capsules |
| Alternative formulation | 3 mg/mL oral solution |
| Prescribing base | Neurosurgeons, neurologists, intensivists |
| Demand pattern | Acute, episodic and diagnosis-driven |
| Generic substitution | High |
| Pricing power | Low for capsules; higher for specialized liquid products |
Aneurysmal subarachnoid hemorrhage is uncommon relative to ischemic stroke and other cardiovascular diseases. Incidence varies by geography, age structure, hypertension prevalence, smoking prevalence, aneurysm detection and access to emergency neurosurgical care. The small patient population limits total market size even when clinical use is guideline-supported.
How has the nimodipine market evolved?
Nimodipine was developed by Bayer and commercialized under the brand name Nimotop. The U.S. Food and Drug Administration approved Nimotop capsules in 1988 for use after subarachnoid hemorrhage.[2]
The market moved through three commercial phases:
Brand-led phase
The original market was supported by branded pricing, physician familiarity and hospital protocols. Bayer’s Nimotop established nimodipine as a standard post-hemorrhage therapy in many markets.
Generic capsule phase
After the relevant compound and product exclusivity periods expired, multiple manufacturers entered the oral capsule market. Generic competition reduced the price of the conventional 30 mg dosage form and shifted purchasing toward wholesalers, hospital pharmacies and group purchasing organizations.
Specialty formulation phase
The commercial opportunity later shifted toward ready-to-administer oral liquid products. Nymalize, a 3 mg/mL oral solution, was approved by the FDA in 2013.[3] The product addressed medication-administration risks associated with transferring liquid nimodipine from capsules and was supplied in a formulation designed for enteral administration.
The liquid formulation created a temporary differentiation opportunity because it addressed a hospital safety and workflow issue rather than a new pharmacologic indication. That opportunity was narrower than a conventional specialty pharmaceutical market because the active ingredient was already generic and the treatment course was short.
What is the financial trajectory for nimodipine?
Nimodipine is a mature, low-revenue pharmaceutical market at the individual-product level. Public company filings generally do not report nimodipine revenue separately, which prevents a reliable standalone global sales figure from being calculated from audited disclosures.
The financial trajectory can be summarized as follows:
| Period | Commercial condition | Financial effect |
|---|---|---|
| 1988 to early generic period | Branded Nimotop and limited competition | Higher unit pricing and stronger brand economics |
| Generic expansion | Multiple capsule suppliers | Lower prices and reduced gross margins |
| 2013 onward | Introduction of Nymalize oral solution | Premium pricing potential in hospital safety segment |
| Mature generic period | Commodity capsule market and limited patient volume | Flat or declining nominal revenue |
| Current market structure | Supplier, shortage and channel-driven competition | Revenue volatility without durable growth |
The largest revenue pools are likely concentrated in branded or differentiated liquid formulations rather than standard capsules. Capsule sales are constrained by:
- Short treatment duration
- Limited annual patient volume
- Generic substitution
- Hospital purchasing pressure
- Absence of chronic maintenance use
- Low switching costs among equivalent suppliers
A manufacturer can generate acceptable returns from nimodipine if it has low-cost manufacturing, dependable supply, institutional contracts or a differentiated formulation. The molecule does not support the revenue profile associated with high-volume cardiovascular drugs such as amlodipine or chronic antihypertensive therapies.
What patents protect nimodipine products?
The original compound patent and early product patents are expired or otherwise no longer commercially relevant in the United States and major European markets. Nimodipine was first approved in the United States in 1988, placing the core patent estate well beyond the normal 20-year patent term from filing for the original invention.[2,4]
| Patent category | Current commercial position |
|---|---|
| Original compound patent | Expired |
| Original capsule formulation | Expired or commercially irrelevant |
| Brand product protection | Expired |
| Generic capsule patents | No meaningful blocking estate expected |
| Oral-solution formulation patents | Historical protection may have applied, but does not restore compound exclusivity |
| Method-of-use patents | No known active U.S. blocking estate central to current capsule sales |
| Manufacturing patents | Potentially relevant at the supplier level, not a broad market barrier |
Patent risk is therefore low for conventional 30 mg nimodipine capsules. The principal intellectual-property issues concern specific formulations, delivery systems, manufacturing processes or device components. Those rights, where active, would generally protect a product configuration rather than the active ingredient across all dosage forms.
What is the Orange Book status of nimodipine?
Nimodipine has no meaningful current Orange Book protection comparable to a newly launched small-molecule product.
The original branded capsule approval was associated with Nimotop. Generic manufacturers entered through abbreviated new drug applications after the loss of relevant exclusivity. FDA labeling states that nimodipine is administered orally and warns against intravenous or parenteral administration because of the risk of serious or fatal cardiovascular events.[1]
The practical Orange Book implications are:
- Core capsule protection does not prevent generic entry.
- Any historical listed patents have expired or ceased to be commercially blocking.
- Current competition is governed primarily by ANDA approval, manufacturing capacity and procurement economics.
- Formulation-specific products may have separate regulatory and patent histories.
The absence of meaningful active Orange Book barriers makes Paragraph IV litigation an unlikely driver of the current market.
When did nimodipine lose exclusivity?
Nimodipine lost its original U.S. market exclusivity after the expiration of the compound and product-protection period associated with the 1988 approval. The exact commercial transition depended on patent term, regulatory exclusivity and generic approval timing, but the market has been generic for many years.
Nimodipine is not protected by current new chemical entity exclusivity. It is also not a biologic and does not have a biosimilar pathway.
Does nimodipine face biosimilar risk?
No. Biosimilars apply to biologic products. Nimodipine is a synthetic small molecule. Competitive risk comes from generic capsules and competing oral solutions, not biosimilars.
Which companies are competing in the nimodipine market?
Competition varies by country and product availability. Historically important commercial entities include Bayer, the original developer and marketer of Nimotop, and Arbor Pharmaceuticals, associated with Nymalize in the United States.[2,3]
Generic suppliers have included regional and multinational pharmaceutical companies distributing nimodipine capsules through hospital and retail channels. The exact supplier roster changes because generic approvals, product discontinuations, shortages and wholesaler contracts change over time.
The competitive landscape has two distinct segments:
Generic capsule segment
This is a price-sensitive market. Products are typically interchangeable from a therapeutic standpoint when they meet FDA or local regulatory standards. Competitive advantage depends on:
- Cost of active pharmaceutical ingredient
- Manufacturing scale
- Regulatory compliance
- Supply reliability
- Hospital contracts
- Wholesaler access
- Ability to avoid recalls or shortages
Specialty oral-solution segment
The oral solution can command a higher price because it may reduce administration errors and simplify enteral delivery in neurologically impaired patients. Its commercial value depends on hospital protocols, pharmacy purchasing policies and evidence that the formulation lowers operational or medication-safety risk.
What formulations are protected by nimodipine patents?
The principal commercially relevant formulations are 30 mg capsules and 3 mg/mL oral solution.
30 mg capsules
Capsules are the established generic dosage form. They have broad supplier availability in many markets and limited differentiation. The primary risk is supply interruption rather than patent infringement.
3 mg/mL oral solution
The oral solution was developed to address administration concerns in critically ill patients. Nimodipine capsules should not be administered intravenously, and improper preparation or administration can cause severe hypotension and cardiovascular harm.[1]
The solution formulation can support:
- Enteral tube administration
- More predictable dosing workflow
- Reduced need to manipulate capsules
- Hospital medication-safety protocols
- Product differentiation after capsule commoditization
Any patent value attached to the solution is formulation-specific. It does not restore exclusivity over nimodipine as a molecule.
What FDA regulatory issues affect the market?
FDA regulatory risk is concentrated in administration safety, labeling and manufacturing quality.
The FDA label warns that nimodipine must be administered orally or through a feeding tube and must not be injected. Intravenous administration has been associated with serious adverse events, including cardiovascular collapse and death.[1]
Key regulatory factors include:
- Route-of-administration control. Packaging and labeling must reduce the risk of accidental intravenous use.
- Dosage-form clarity. Hospitals must distinguish capsules from ready-to-use oral solution.
- Supply continuity. A small supplier base can create operational exposure if a manufacturer experiences a quality problem.
- ANDA compliance. Generic products must meet bioequivalence and manufacturing requirements.
- Medication-error prevention. The product’s narrow safety margin for improper administration gives formulation and packaging design commercial relevance.
Nimodipine is not subject to the regulatory development costs associated with a new chemical entity. The remaining regulatory burden is largely maintenance-oriented.
Are there Paragraph IV challenges or nimodipine patent lawsuits?
Nimodipine is not a significant current Paragraph IV litigation market. Paragraph IV disputes are most commercially important before generic launch, when an active patent can delay or structure entry. Nimodipine’s core patent estate is too old to create that type of present-day barrier.
No major active U.S. patent litigation is central to the current commercial outlook for standard nimodipine capsules. Historical disputes, if any, would have limited relevance unless they involved an active formulation, manufacturing process or market-specific patent.
Settlement agreements are not known to be a material factor in present nimodipine competition. The market is primarily shaped by generic entry and procurement rather than branded-generic litigation.
What generic entry risks exist for nimodipine manufacturers?
Generic entry risk is asymmetric. Incumbent manufacturers face price erosion and supply substitution, while new entrants face a small market with limited room for several profitable suppliers.
Risks to incumbent capsule manufacturers
- Loss of hospital contracts to lower-priced suppliers
- Wholesale price compression
- Product discontinuation by competitors
- FDA inspection or manufacturing disruption
- Shortages that create temporary volume opportunities but damage long-term reliability
- Low patient volume relative to fixed regulatory and manufacturing costs
Risks to new entrants
- Small addressable patient population
- Low repeat utilization
- Contract concentration among hospital systems
- Limited ability to differentiate a conventional capsule
- Need to maintain inventory despite episodic demand
- Potentially weak return on regulatory investment
The strongest entry case is usually a dependable low-cost capsule supplier or a differentiated oral-solution manufacturer with hospital access. A me-too capsule launch has limited strategic value unless it fills a supply gap.
How strong is the nimodipine patent estate?
The patent estate is weak for the active ingredient and conventional capsule. It is potentially moderate for specific delivery or formulation technologies, but that protection is narrower and more vulnerable to design-around strategies.
| Protection dimension | Strength |
|---|---|
| Active ingredient | Very weak; expired core rights |
| Standard capsule | Very weak |
| Oral solution | Product-specific and potentially moderate |
| Method of use | Limited current blocking value |
| Manufacturing process | Potentially relevant but supplier-specific |
| Regulatory exclusivity | None of strategic importance |
| Biosimilar protection | Not applicable |
| Litigation leverage | Low |
The commercial moat is therefore operational rather than patent-based. Manufacturing quality, inventory management, hospital contracting and regulatory compliance matter more than exclusionary rights.
How does nimodipine compare with competing calcium-channel blockers?
Nimodipine is not commercially interchangeable with chronic calcium-channel blockers such as amlodipine, diltiazem, verapamil or nifedipine in terms of market structure or treatment purpose.
| Drug | Primary use | Typical treatment duration | Market profile |
|---|---|---|---|
| Nimodipine | Neurological protection after aneurysmal subarachnoid hemorrhage | 21 days | Small, hospital-focused, episodic |
| Amlodipine | Hypertension and angina | Chronic | High-volume generic |
| Diltiazem | Hypertension, angina and arrhythmias | Chronic or recurring | Broad generic market |
| Verapamil | Hypertension and arrhythmias | Chronic or recurring | Mature generic |
| Nifedipine | Hypertension and angina | Chronic | High-volume generic |
Nimodipine’s clinical niche supports physician familiarity and protocol-driven use, but its limited indication prevents the scale achieved by chronic cardiovascular therapies.
What geographic markets matter most for nimodipine?
The most commercially relevant markets are jurisdictions with:
- Established aneurysm-treatment centers
- Neurocritical-care infrastructure
- Routine use of nimodipine after aneurysmal subarachnoid hemorrhage
- Reimbursement for inpatient medicines
- Local generic manufacturing or import capacity
The United States has high product standardization and strong hospital purchasing pressure. Europe has a fragmented national and regional reimbursement environment, with Bayer’s historical brand presence and generic competition varying by country. Japan, South Korea and other advanced Asian markets have substantial neurovascular treatment capacity but distinct regulatory and reimbursement systems.
Lower-income markets may have clinical demand but weaker commercial economics. Availability can depend on importers, public tenders and intermittent procurement rather than stable retail demand.
What manufacturing and supply barriers affect nimodipine?
The active ingredient is a mature small molecule, so basic chemical synthesis is not a major strategic barrier. The more important constraints are:
- Qualified API sourcing
- Stability and dissolution performance
- Oral-solution manufacturing controls
- Packaging that prevents route-of-administration errors
- Hospital inventory planning
- Compliance with current good manufacturing practices
- Maintenance of multiple approved suppliers
A shortage can produce temporary pricing power, but it does not create durable market expansion. The patient population remains limited, and hospitals may switch suppliers quickly once availability normalizes.
What is the outlook for nimodipine revenue?
The base case is a stable-to-declining mature market in standard capsules, with episodic growth in specialty oral solutions and regions expanding neurocritical-care capacity.
| Scenario | Market outcome | Revenue implication |
|---|---|---|
| Base case | Stable clinical use, continued generic competition | Flat to modest decline |
| Upside case | More aneurysmal subarachnoid hemorrhage treatment, stronger liquid adoption, supply shortages | Temporary volume or price increase |
| Downside case | Supplier exits, hospital budget pressure, reduced liquid reimbursement | Lower market revenue and potential access problems |
| Strategic case | New delivery system or hospital-safety product | Limited premium segment growth |
A durable revenue reacceleration would require one of four changes: a materially differentiated delivery system, expansion into a new approved indication, broad geographic penetration or a supply-constrained market that supports higher pricing. None is inherent in the current standard capsule business.
Key Takeaways
- Nimodipine is a mature small-molecule drug with no meaningful remaining core patent protection.
- Its principal indication is a 21-day treatment course after aneurysmal subarachnoid hemorrhage.
- The U.S. market is generic for standard 30 mg capsules.
- Nymalize and other oral-solution products offer the main potential for formulation-based differentiation.
- Nimodipine has no biosimilar exposure because it is not a biologic.
- Current Paragraph IV litigation and settlement activity are not material market drivers.
- Revenue is constrained by a small, episodic patient population and intense hospital purchasing pressure.
- The commercial moat is based on supply reliability, formulation safety, manufacturing quality and institutional contracts.
- Standard capsule revenue is likely flat to declining, while specialty liquid products may retain targeted premium economics.
- Manufacturing disruption and supplier exits create greater near-term risk than patent expiration.
FAQs About Nimodipine Market and Financial Outlook
Is nimodipine still a profitable pharmaceutical product?
It can be profitable as a low-cost generic or differentiated hospital formulation, but its limited patient population and short treatment duration restrict total revenue potential.
Does nimodipine have patent exclusivity in the United States?
No meaningful core patent exclusivity remains for standard nimodipine capsules. Any relevant formulation protection would be narrower and product-specific.
Can a generic manufacturer launch nimodipine without major patent risk?
For standard capsules, patent risk is low. The main barriers are FDA approval, manufacturing economics, hospital contracts and reliable supply.
Why can nimodipine oral solution cost more than capsules?
The oral solution may reduce administration complexity and medication-error risk in critically ill patients. Those operational benefits can support premium pricing despite the absence of active-ingredient exclusivity.
What is the biggest commercial risk for nimodipine?
The primary risk is market commoditization combined with a small, episodic patient base. For hospitals, the most immediate operational risk is supplier interruption or accidental improper administration.
References
- U.S. Food and Drug Administration. (2023). Nimodipine prescribing information. FDA-approved labeling.
- U.S. Food and Drug Administration. (1988). Nimotop (nimodipine) approval history and prescribing information.
- U.S. Food and Drug Administration. (2013). Nymalize (nimodipine) oral solution prescribing information.
- United States Patent and Trademark Office. (n.d.). Patent term and expiration framework for pharmaceutical patents. USPTO.
More… ↓
