ONUREG Drug Patent Profile
When do Onureg patents expire, and when can generic versions of Onureg launch?
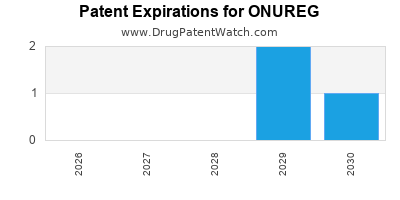
Onureg is a drug marketed by Bristol and is included in one NDA. There are three patents protecting this drug and one Paragraph IV challenge.
The generic ingredient in ONUREG is azacitidine. There is one drug master file entry for this compound. Twenty-one suppliers are listed for this compound. Additional details are available on the azacitidine profile page.
DrugPatentWatch® Litigation and Generic Entry Outlook for Onureg
A generic version of ONUREG was approved as azacitidine by DR REDDYS on September 16th, 2013.
AI Deep Research
Questions you can ask:
- What is the 5 year forecast for ONUREG?
- What are the global sales for ONUREG?
- What is Average Wholesale Price for ONUREG?
Summary for ONUREG
| US Patents: | 3 |
| Applicants: | 1 |
| NDAs: | 1 |
| Finished Product Suppliers / Packagers: | 1 |
| Raw Ingredient (Bulk) Api Vendors: | 124 |
| Clinical Trials: | 40 |
| Drug Prices: | Drug price information for ONUREG |
| Patent Litigation and PTAB cases: | See patent lawsuits and PTAB cases for ONUREG |
| What excipients (inactive ingredients) are in ONUREG? | ONUREG excipients list |
| DailyMed Link: | ONUREG at DailyMed |

Recent Clinical Trials for ONUREG
Identify potential brand extensions & 505(b)(2) entrants
| Sponsor | Phase |
|---|---|
| Hikma Pharmaceuticals LLC | PHASE1 |
| French Innovative Leukemia Organisation | Phase 2 |
| Acute Leukemia French Association | Phase 2 |
Pharmacology for ONUREG
| Drug Class | Nucleoside Metabolic Inhibitor |
| Mechanism of Action | Nucleic Acid Synthesis Inhibitors |
Paragraph IV (Patent) Challenges for ONUREG
| Tradename | Dosage | Ingredient | Strength | NDA | ANDAs Submitted | Submissiondate |
|---|---|---|---|---|---|---|
| ONUREG | Tablets | azacitidine | 200 mg and 300 mg | 214120 | 1 | 2021-09-30 |
US Patents and Regulatory Information for ONUREG
ONUREG is protected by three US patents and one FDA Regulatory Exclusivity.
| Applicant | Tradename | Generic Name | Dosage | NDA | Approval Date | TE | Type | RLD | RS | Patent No. | Patent Expiration | Product | Substance | Delist Req. | Exclusivity Expiration |
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Bristol | ONUREG | azacitidine | TABLET;ORAL | 214120-001 | Sep 1, 2020 | RX | Yes | No | ⤷ Start Trial | ⤷ Start Trial | Y | ⤷ Start Trial | |||
| Bristol | ONUREG | azacitidine | TABLET;ORAL | 214120-002 | Sep 1, 2020 | RX | Yes | Yes | ⤷ Start Trial | ⤷ Start Trial | Y | ⤷ Start Trial | |||
| Bristol | ONUREG | azacitidine | TABLET;ORAL | 214120-001 | Sep 1, 2020 | RX | Yes | No | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | ||||
| >Applicant | >Tradename | >Generic Name | >Dosage | >NDA | >Approval Date | >TE | >Type | >RLD | >RS | >Patent No. | >Patent Expiration | >Product | >Substance | >Delist Req. | >Exclusivity Expiration |
EU/EMA Drug Approvals for ONUREG
| Company | Drugname | Inn | Product Number / Indication | Status | Generic | Biosimilar | Orphan | Marketing Authorisation | Marketing Refusal |
|---|---|---|---|---|---|---|---|---|---|
| Bristol-Myers Squibb Pharma EEIG | Vidaza | azacitidine | EMEA/H/C/000978Vidaza is indicated for the treatment of adult patients who are not eligible for haematopoietic stem cell transplantation (HSCT) with: intermediate 2 and high-risk myelodysplastic syndromes (MDS) according to the International Prognostic Scoring System (IPSS),chronic myelomonocytic leukaemia (CMML) with 10 29 % marrow blasts without myeloproliferative disorder,acute myeloid leukaemia (AML) with 20 30 % blasts and multi-lineage dysplasia, according to World Health Organisation (WHO) classification.Vidaza is indicated for the treatment of adult patients aged 65 years or older who are not eligible for HSCT with AML with >30% marrow blasts according to the WHO classification. | Authorised | no | no | no | 2008-12-17 | |
| Accord Healthcare S.L.U. | Azacitidine Accord | azacitidine | EMEA/H/C/005147Azacitidine Accord is indicated for the treatment of adult patients who are not eligible for haematopoietic stem cell transplantation (HSCT) with:- intermediate-2 and high-risk myelodysplastic syndromes (MDS) according to the International Prognostic Scoring System (IPSS),- chronic myelomonocytic leukaemia (CMML) with 10-29 % marrow blasts without myeloproliferative disorder,- acute myeloid leukaemia (AML) with 20-30 % blasts and multi-lineage dysplasia, according to World Health Organisation (WHO) classification,- AML with >30% marrow blasts according to the WHO classification. | Authorised | yes | no | no | 2020-02-13 | |
| Mylan Ireland Limited | Azacitidine Mylan | azacitidine | EMEA/H/C/004984Azacitidine Mylan is indicated for the treatment of adult patients who are not eligible for haematopoietic stem cell transplantation (HSCT) with:intermediate 2 and high risk myelodysplastic syndromes (MDS) according to the International Prognostic Scoring System (IPSS),chronic myelomonocytic leukaemia (CMML) with 10 29% marrow blasts without myeloproliferative disorder,acute myeloid leukaemia (AML) with 20 30% blasts and multi lineage dysplasia, according to World Health Organisation (WHO) classification,AML with > 30% marrow blasts according to the WHO classification. | Authorised | yes | no | no | 2020-03-27 | |
| >Company | >Drugname | >Inn | >Product Number / Indication | >Status | >Generic | >Biosimilar | >Orphan | >Marketing Authorisation | >Marketing Refusal |
International Patents for ONUREG
See the table below for patents covering ONUREG around the world.
| Country | Patent Number | Title | Estimated Expiration |
|---|---|---|---|
| Argentina | 071808 | ⤷ Start Trial | |
| Australia | 2009246926 | ⤷ Start Trial | |
| Australia | 2013202665 | ⤷ Start Trial | |
| >Country | >Patent Number | >Title | >Estimated Expiration |
More… ↓
DrugChatter Q&A for ONUREG
Make Better Decisions: Try a trial or see plans & pricing
Drugs may be covered by multiple patents or regulatory protections. All trademarks and applicant names are the property of their respective owners or licensors. Although great care is taken in the proper and correct provision of this service, thinkBiotech LLC does not accept any responsibility for possible consequences of errors or omissions in the provided data. The data presented herein is for information purposes only. There is no warranty that the data contained herein is error free. We do not provide individual investment advice. This service is not registered with any financial regulatory agency. The information we publish is educational only and based on our opinions plus our models. By using DrugPatentWatch you acknowledge that we do not provide personalized recommendations or advice. thinkBiotech performs no independent verification of facts as provided by public sources nor are attempts made to provide legal or investing advice. Any reliance on data provided herein is done solely at the discretion of the user. Users of this service are advised to seek professional advice and independent confirmation before considering acting on any of the provided information. thinkBiotech LLC reserves the right to amend, extend or withdraw any part or all of the offered service without notice.
ISSN: 2162-2639

Privacy and Cookies
Terms & Conditions
Site Map
DrugPatentWatch Alternatives
LOE / Major Patent Expirations 2026 - 2027
NCE-1 Patent Challenge Dates 2026 - 2027
Friedman, Yali. "DrugPatentWatch" DrugPatentWatch, thinkBiotech, 2026, www.DrugPatentWatch.com.
See Primary Research Papers Citing DrugPatentWatch