KOSELUGO Drug Patent Profile
✉ Email this page to a colleague
Which patents cover Koselugo, and what generic alternatives are available?
Koselugo is a drug marketed by Astrazeneca and is included in two NDAs. There are eight patents protecting this drug and one Paragraph IV challenge.
The generic ingredient in KOSELUGO is selumetinib sulfate. There is one drug master file entry for this compound. One supplier is listed for this compound. Additional details are available on the selumetinib sulfate profile page.
DrugPatentWatch® Generic Entry Outlook for Koselugo
Koselugo was eligible for patent challenges on April 10, 2024.
By analyzing the patents and regulatory protections it appears that the earliest date
for generic entry will be November 19, 2032. This may change due to patent challenges or generic licensing.
There have been two patent litigation cases involving the patents protecting this drug, indicating strong interest in generic launch. Recent data indicate that 63% of patent challenges are decided in favor of the generic patent challenger and that 54% of successful patent challengers promptly launch generic drugs.
Indicators of Generic Entry
AI Deep Research
Questions you can ask:
- What is the 5 year forecast for KOSELUGO?
- What are the global sales for KOSELUGO?
- What is Average Wholesale Price for KOSELUGO?
Summary for KOSELUGO
| US Patents: | 8 |
| Applicants: | 1 |
| NDAs: | 2 |
| Finished Product Suppliers / Packagers: | 1 |
| Raw Ingredient (Bulk) Api Vendors: | 129 |
| Clinical Trials: | 12 |
| Patent Applications: | 5,974 |
| Drug Prices: | Drug price information for KOSELUGO |
| Patent Litigation and PTAB cases: | See patent lawsuits and PTAB cases for KOSELUGO |
| What excipients (inactive ingredients) are in KOSELUGO? | KOSELUGO excipients list |
| DailyMed Link: | KOSELUGO at DailyMed |
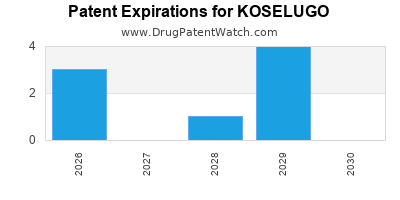

DrugPatentWatch® Estimated Loss of Exclusivity (LOE) Date for KOSELUGO
Generic Entry Dates for KOSELUGO*:
Constraining patent/regulatory exclusivity:
TREATMENT OF ADULT PATIENTS WITH NEUROFIBROMATOSIS TYPE 1 (NF1) WHO HAVE SYMPTOMATIC, INOPERABLE PLEXIFORM NEUROFIBROMAS (PN) NDA:
Dosage:
CAPSULE;ORAL |
Generic Entry Dates for KOSELUGO*:
Constraining patent/regulatory exclusivity:
FDA HAS NOT RECOGNIZED ORPHAN-DRUG EXCLUSIVITY (ODE) FOR THIS DRUG, BUT IT CONTAINS THE SAME ACTIVE MOIETY OR MOIETIES AS ANOTHER DRUG(S) THAT WAS ELIGIBLE FOR ODE, AND ALSO SHARES ODE-PROTECTED USE(S) OR INDICATION(S) WITH THAT DRUG(S).AN APPLICATION SEEKING APPROVAL FOR THE SAME ACTIVE MOIETY OR MOIETIES, INCLUDING AN ANDA THAT CITES THIS NDA AS ITS BASIS OF SUBMISSION, MAY NOT BE APPROVED FOR SUCH ODE-PROTECTED USE(S) AND INDICATION(S) NDA:
Dosage:
GRANULE;ORAL |
*The generic entry opportunity date is the latter of the last compound-claiming patent and the last regulatory exclusivity protection. Many factors can influence early or later generic entry. This date is provided as a rough estimate of generic entry potential and should not be used as an independent source.
Recent Clinical Trials for KOSELUGO
Identify potential brand extensions & 505(b)(2) entrants
| Sponsor | Phase |
|---|---|
| Congressionally Directed Medical Research Programs | Phase 2 |
| Children's Hospital of Philadelphia | Phase 2 |
| University of Alabama at Birmingham | Phase 2 |
Pharmacology for KOSELUGO
| Drug Class | Kinase Inhibitor |
| Mechanism of Action | Mitogen-Activated Protein Kinase Kinase 1 Inhibitors Mitogen-Activated Protein Kinase Kinase 2 Inhibitors |
Paragraph IV (Patent) Challenges for KOSELUGO
| Tradename | Dosage | Ingredient | Strength | NDA | ANDAs Submitted | Submissiondate |
|---|---|---|---|---|---|---|
| KOSELUGO | Capsules | selumetinib sulfate | 10 mg and 25 mg | 213756 | 1 | 2026-08-04 |
US Patents and Regulatory Information for KOSELUGO
KOSELUGO is protected by eight US patents and seven FDA Regulatory Exclusivities.
Based on analysis by DrugPatentWatch, the earliest date for a generic version of KOSELUGO is ⤷ Start Trial.
This potential generic entry date is based on TREATMENT OF ADULT PATIENTS WITH NEUROFIBROMATOSIS TYPE 1 (NF1) WHO HAVE SYMPTOMATIC, INOPERABLE PLEXIFORM NEUROFIBROMAS (PN).
Generics may enter earlier, or later, based on new patent filings, patent extensions, patent invalidation, early generic licensing, generic entry preferences, and other factors.
| Applicant | Tradename | Generic Name | Dosage | NDA | Approval Date | TE | Type | RLD | RS | Patent No. | Patent Expiration | Product | Substance | Delist Req. | Exclusivity Expiration |
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Astrazeneca | KOSELUGO | selumetinib sulfate | GRANULE;ORAL | 219943-001 | Sep 10, 2025 | RX | Yes | Yes | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | ||||
| Astrazeneca | KOSELUGO | selumetinib sulfate | GRANULE;ORAL | 219943-001 | Sep 10, 2025 | RX | Yes | Yes | 8,178,693 | ⤷ Start Trial | Y | Y | ⤷ Start Trial | ||
| Astrazeneca | KOSELUGO | selumetinib sulfate | GRANULE;ORAL | 219943-002 | Sep 10, 2025 | RX | Yes | No | 9,562,017 | ⤷ Start Trial | Y | ⤷ Start Trial | |||
| >Applicant | >Tradename | >Generic Name | >Dosage | >NDA | >Approval Date | >TE | >Type | >RLD | >RS | >Patent No. | >Patent Expiration | >Product | >Substance | >Delist Req. | >Exclusivity Expiration |
Expired US Patents for KOSELUGO
| Applicant | Tradename | Generic Name | Dosage | NDA | Approval Date | Patent No. | Patent Expiration |
|---|---|---|---|---|---|---|---|
| Astrazeneca | KOSELUGO | selumetinib sulfate | CAPSULE;ORAL | 213756-001 | Apr 10, 2020 | 8,178,693 | ⤷ Start Trial |
| Astrazeneca | KOSELUGO | selumetinib sulfate | GRANULE;ORAL | 219943-002 | Sep 10, 2025 | 8,178,693 | ⤷ Start Trial |
| Astrazeneca | KOSELUGO | selumetinib sulfate | GRANULE;ORAL | 219943-001 | Sep 10, 2025 | 8,178,693 | ⤷ Start Trial |
| >Applicant | >Tradename | >Generic Name | >Dosage | >NDA | >Approval Date | >Patent No. | >Patent Expiration |
International Patents for KOSELUGO
When does loss-of-exclusivity occur for KOSELUGO?
Based on analysis by DrugPatentWatch, the following patents block generic entry in the countries listed below:
Argentina
Patent: 1100
Estimated Expiration: ⤷ Start Trial
Patent: 6001
Estimated Expiration: ⤷ Start Trial
Australia
Patent: 09229204
Estimated Expiration: ⤷ Start Trial
Brazil
Patent: 0909267
Estimated Expiration: ⤷ Start Trial
Canada
Patent: 18653
Estimated Expiration: ⤷ Start Trial
Chile
Patent: 09000765
Estimated Expiration: ⤷ Start Trial
Patent: 12002380
Patent: Compuestos derivados de bezoimidazol, inhibidores de mek; utiles en el tratamiento del cancer.(divisional solicitud cl 521-03)
Estimated Expiration: ⤷ Start Trial
China
Patent: 2046156
Estimated Expiration: ⤷ Start Trial
Colombia
Patent: 11068
Estimated Expiration: ⤷ Start Trial
Croatia
Patent: 0120657
Estimated Expiration: ⤷ Start Trial
Cyprus
Patent: 13279
Estimated Expiration: ⤷ Start Trial
Denmark
Patent: 71321
Estimated Expiration: ⤷ Start Trial
Ecuador
Patent: 10010578
Estimated Expiration: ⤷ Start Trial
European Patent Office
Patent: 71321
Estimated Expiration: ⤷ Start Trial
Hong Kong
Patent: 49476
Estimated Expiration: ⤷ Start Trial
Patent: 56844
Estimated Expiration: ⤷ Start Trial
Japan
Patent: 47710
Estimated Expiration: ⤷ Start Trial
Patent: 11515455
Estimated Expiration: ⤷ Start Trial
Patent: 14114320
Estimated Expiration: ⤷ Start Trial
Malaysia
Patent: 7492
Estimated Expiration: ⤷ Start Trial
Mexico
Patent: 10010671
Estimated Expiration: ⤷ Start Trial
New Zealand
Patent: 8849
Estimated Expiration: ⤷ Start Trial
Peru
Patent: 091755
Estimated Expiration: ⤷ Start Trial
Poland
Patent: 71321
Estimated Expiration: ⤷ Start Trial
Portugal
Patent: 71321
Estimated Expiration: ⤷ Start Trial
Russian Federation
Patent: 91920
Estimated Expiration: ⤷ Start Trial
Patent: 10143906
Estimated Expiration: ⤷ Start Trial
Saudi Arabia
Patent: 9300195
Estimated Expiration: ⤷ Start Trial
Serbia
Patent: 409
Estimated Expiration: ⤷ Start Trial
Slovenia
Patent: 71321
Estimated Expiration: ⤷ Start Trial
South Africa
Patent: 1006766
Estimated Expiration: ⤷ Start Trial
South Korea
Patent: 1650958
Estimated Expiration: ⤷ Start Trial
Patent: 110005246
Estimated Expiration: ⤷ Start Trial
Spain
Patent: 87942
Estimated Expiration: ⤷ Start Trial
Taiwan
Patent: 0946511
Estimated Expiration: ⤷ Start Trial
Patent: 33840
Estimated Expiration: ⤷ Start Trial
Ukraine
Patent: 1654
Estimated Expiration: ⤷ Start Trial
Uruguay
Patent: 737
Estimated Expiration: ⤷ Start Trial
Generics may enter earlier, or later, based on new patent filings, patent extensions, patent invalidation, early generic licensing, generic entry preferences, and other factors.
See the table below for additional patents covering KOSELUGO around the world.
| Country | Patent Number | Title | Estimated Expiration |
|---|---|---|---|
| Argentina | 071100 | ⤷ Start Trial | |
| Argentina | 116001 | ⤷ Start Trial | |
| Australia | 2009229204 | ⤷ Start Trial | |
| >Country | >Patent Number | >Title | >Estimated Expiration |
Supplementary Protection Certificates for KOSELUGO
| Patent Number | Supplementary Protection Certificate | SPC Country | SPC Expiration | SPC Description |
|---|---|---|---|---|
| 1482932 | PA2019007 | Lithuania | ⤷ Start Trial | PRODUCT NAME: BINIMETINIBAS BET KOKIOMIS FORMOMIS, KURIOMS TAIKOMA PAGRINDINIO PATENTO APSAUGA; REGISTRATION NO/DATE: EU/1/18/1315 20180920 |
| 1482932 | LUC00100 | Luxembourg | ⤷ Start Trial | PRODUCT NAME: BINIMETINIB SOUS TOUTES SES FORMES TELLES QUE PROTEGEES PAR LE BREVET DE BASE; AUTHORISATION NUMBER AND DATE: EU/1/18/1315 20180924 |
| 1482932 | 300974 | Netherlands | ⤷ Start Trial | DETAILS ASSIGNMENT: CHANGE OF OWNER(S), CHANGE OF OWNER(S) NAME |
| >Patent Number | >Supplementary Protection Certificate | >SPC Country | >SPC Expiration | >SPC Description |
KOSELUGO Market Dynamics and Financial Trajectory: Selumetinib Revenue, Competition, Exclusivity, and Commercial Outlook
More… ↓
DrugChatter Q&A for KOSELUGO
Make Better Decisions: Try a trial or see plans & pricing
Drugs may be covered by multiple patents or regulatory protections. All trademarks and applicant names are the property of their respective owners or licensors. Although great care is taken in the proper and correct provision of this service, thinkBiotech LLC does not accept any responsibility for possible consequences of errors or omissions in the provided data. The data presented herein is for information purposes only. There is no warranty that the data contained herein is error free. We do not provide individual investment advice. This service is not registered with any financial regulatory agency. The information we publish is educational only and based on our opinions plus our models. By using DrugPatentWatch you acknowledge that we do not provide personalized recommendations or advice. thinkBiotech performs no independent verification of facts as provided by public sources nor are attempts made to provide legal or investing advice. Any reliance on data provided herein is done solely at the discretion of the user. Users of this service are advised to seek professional advice and independent confirmation before considering acting on any of the provided information. thinkBiotech LLC reserves the right to amend, extend or withdraw any part or all of the offered service without notice.
ISSN: 2162-2639

Privacy and Cookies
Terms & Conditions
Site Map
DrugPatentWatch Alternatives
LOE / Major Patent Expirations 2026 - 2027
NCE-1 Patent Challenge Dates 2026 - 2027
Friedman, Yali. "DrugPatentWatch" DrugPatentWatch, thinkBiotech, 2026, www.DrugPatentWatch.com.
See Primary Research Papers Citing DrugPatentWatch