Share This Page
EMGALITY Drug Profile
✉ Email this page to a colleague
Summary for Tradename: EMGALITY
| High Confidence Patents: | 0 |
| Applicants: | 1 |
| BLAs: | 1 |
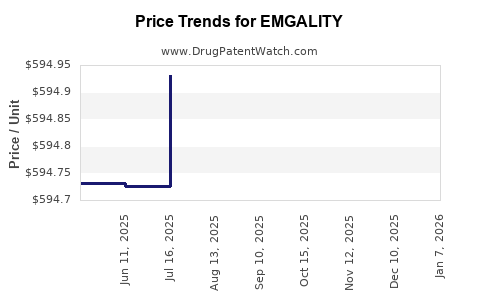
| Drug Prices: | Drug price information for EMGALITY |
| Recent Clinical Trials: | See clinical trials for EMGALITY |
Recent Clinical Trials for EMGALITY
Identify potential brand extensions & biosimilar entrants
| Sponsor | Phase |
|---|---|
| Chicago Headache Center & Research Institute | Phase 4 |
| AbbVie | Phase 4 |
| University of California, San Francisco | Phase 2 |
Note on Biologic Patents
Matching patents to biologic drugs is far more complicated than for small-molecule drugs.
DrugPatentWatch employs three methods to identify biologic patents:
- Brand-side disclosures in response to biosimilar applications
- DrugPatentWatch analysis and company disclosures
- Patents from broad patent text search
These patents were identified from disclosures by the brand-side company, in response to a potential biosimilar seeking to launch. They have a high certainty of blocking biosimilar entry. The expiration dates listed are not estimates — they're expiration dates as indicated by the brand-side company.
These patents were identified from searching various sources, including drug labels and other general disclosures from the brand-side company. This list may exclude some of the patents which block biosimilar launch, and some of these patents listed may not actually block biosimilar launch. The expiration dates listed for these patents are estimates, based on the grant date of the patent.
For completeness, these patents were identified by searching the patent literature for mentions of the branded or ingredient name of the drug. Some of these patents protect the original drug, whereas others may protect follow-on inventions or even inventions casually mentioning the drug. The expiration dates listed for these patents are estimates, based on the grant date of the patent.
1) High Certainty: US Patents for EMGALITY Derived from Brand-Side Litigation
No patents found based on brand-side litigation
2) High Certainty: US Patents for EMGALITY Derived from DrugPatentWatch Analysis and Company Disclosures
No patents found based on company disclosures
3) Low Certainty: US Patents for EMGALITY Derived from Patent Text Search
No patents found based on company disclosures
EMGALITY Market Dynamics, Financial Trajectory, Patent Exclusivity, and Competitive Risk
Emgality, Eli Lilly’s galcanezumab, is a commercially established CGRP monoclonal antibody for migraine prevention and episodic cluster headache. Its revenue trajectory has been positive but slower than the growth of newer oral CGRP therapies. Lilly reported approximately $817 million in Emgality revenue for 2024, up from about $715 million in 2023. The product remains protected by biologic regulatory exclusivity through 2030, while patent protection is expected to extend into the mid-2030s or later depending on the patent, jurisdiction, and any applicable adjustments.
The principal commercial risks are payer pressure, competition from AbbVie’s Qulipta and Ubrelvy, Biohaven’s Nurtec ODT, Teva’s Ajovy, and Amgen/Novartis’s Aimovig, as well as future biosimilar development. No conventional generic pathway applies because Emgality is a biologic licensed under a biologics license application, or BLA.
What is Emgality and how is it used?
Emgality is a humanized monoclonal antibody targeting calcitonin gene-related peptide, or CGRP. Lilly markets it under the active ingredient galcanezumab-gnlm.
| Attribute | Emgality |
|---|---|
| Active ingredient | Galcanezumab-gnlm |
| Manufacturer | Eli Lilly and Company |
| FDA application | BLA 761063 |
| Initial FDA approval | September 27, 2018 |
| Initial indication | Preventive treatment of migraine in adults |
| Additional indication | Preventive treatment of episodic cluster headache in adults |
| Dosage form | Prefilled pen, prefilled syringe, and single-dose syringe |
| Administration | Subcutaneous injection |
| Loading dose for migraine | 240 mg |
| Monthly maintenance dose | 120 mg |
| Cluster-headache dose | 300 mg monthly during the cluster period |
| Reference product type | Biologic |
| Interchangeable biosimilar | None approved as of the latest public FDA records reviewed |
The FDA approved Emgality for migraine prevention in 2018 and for episodic cluster headache in 2019. The product competes in a market that includes injectable antibodies, oral gepants, and legacy preventive therapies such as topiramate, beta blockers, and onabotulinumtoxinA.[1]
How has Emgality revenue changed?
Emgality revenue has grown from a launch-stage product into a mid-sized specialty pharmaceutical franchise. Lilly’s reported sales indicate continued expansion despite increasing competition in the CGRP class.
| Fiscal year | Reported Emgality revenue | Approximate year-over-year change |
|---|---|---|
| 2021 | About $550 million | Growth |
| 2022 | About $642 million | Approximately 17% |
| 2023 | About $715 million | Approximately 11% |
| 2024 | About $817 million | Approximately 14% |
Sources: Eli Lilly annual reports and Form 10-K filings.[2-5]
The financial trajectory has several features:
- Emgality continues to add revenue despite class crowding.
- Growth is being supported by broader awareness of CGRP-directed prevention and the episodic cluster-headache indication.
- Net sales growth is exposed to rebates, discounts, specialty-pharmacy economics, and payer utilization controls.
- The product is materially smaller than Lilly’s diabetes, obesity, oncology, and immunology franchises, limiting its effect on consolidated corporate revenue.
- Emgality remains strategically relevant because it produces recurring specialty-pharmacy revenue without the manufacturing complexity of a cell or gene therapy.
Lilly does not generally disclose Emgality operating margin, gross-to-net deductions, or patient-level profitability. Product-level revenue is therefore a better public indicator of commercial performance than contribution margin.
Why is Emgality revenue still growing?
The market has expanded through increased diagnosis of migraine, greater acceptance of preventive treatment, and migration from older oral therapies toward CGRP-specific drugs. Emgality benefits from monthly dosing and a delivery system that supports home administration.
The product’s commercial position also reflects prescriber familiarity. Lilly launched Emgality during the first major wave of preventive CGRP antibodies, giving it an established clinical and reimbursement footprint.
Growth is constrained by:
- Prior authorization requirements.
- Step-therapy rules requiring failure of older preventive medicines.
- Competition from oral gepants.
- Switching among CGRP antibodies.
- Patient copay exposure after manufacturer assistance expires.
- Payer preference for lower-net-cost products.
- The absence of a broad acute-treatment label comparable with oral gepants.
The episodic cluster-headache indication differentiates Emgality from several competing preventive products. Its commercial value is limited by the smaller size of the cluster-headache population and the episodic nature of treatment.
How does Emgality compare with competing migraine drugs?
Emgality competes against both biologics and oral CGRP antagonists. The key commercial distinction is convenience versus route of administration.
| Product | Company | Class | Main use | Route | Competitive position |
|---|---|---|---|---|---|
| Emgality | Eli Lilly | Anti-CGRP antibody | Migraine prevention; episodic cluster headache | Monthly injection | Established preventive biologic |
| Aimovig | Amgen/Novartis | CGRP receptor antibody | Migraine prevention | Monthly or quarterly injection depending on dose | First-to-market preventive antibody |
| Ajovy | Teva | Anti-CGRP antibody | Migraine prevention | Monthly or quarterly injection | Flexible dosing |
| Qulipta | AbbVie | Oral CGRP antagonist | Migraine prevention | Daily oral | Strong convenience and oral-positioning advantage |
| Ubrelvy | AbbVie | Oral CGRP antagonist | Acute migraine treatment | Oral | Acute-treatment competitor |
| Nurtec ODT | Pfizer, formerly Biohaven | Oral CGRP antagonist | Acute treatment and prevention | Orally disintegrating tablet | Dual-use product |
| Botox | AbbVie | Botulinum toxin | Chronic migraine prevention | In-office injection | Established chronic-migraine option |
Oral gepants create the greatest strategic pressure because they remove the injection barrier. They also allow manufacturers to position one molecule across acute and preventive treatment, although labeling varies by product.
Emgality retains advantages in monthly administration, long clinical experience, and an FDA-approved cluster-headache indication. It is less competitive where patients or prescribers favor oral treatment or where payers create class-level restrictions.
When does Emgality lose exclusivity?
Emgality has two separate protection dates: biologic regulatory exclusivity and patent protection.
Under the Biologics Price Competition and Innovation Act, a reference biologic generally receives 12 years of reference-product exclusivity. For Emgality, the relevant period runs from the 2018 licensure date and is expected to expire in September 2030, subject to the statutory treatment of any applicable pediatric exclusivity.[6]
Patent expiration is separate. The underlying galcanezumab patent estate includes antibody composition, sequence, formulation, manufacturing, and therapeutic-use claims. Public patent records indicate that relevant U.S. patent protection can extend beyond the 12-year biologic exclusivity period, with some claims reaching into the mid-2030s or later. The precise end date depends on:
- The individual patent.
- Patent-term adjustment.
- Patent-term extension.
- Terminal disclaimers.
- Claim validity and enforceability.
- Whether a biosimilar applicant challenges the patent.
- The scope of the claims that survive litigation.
A single “Emgality patent expiration date” is therefore inaccurate. The commercial loss-of-exclusivity date will depend on which patents are listed or asserted against a biosimilar applicant and whether the applicant prevails.
What patents protect Emgality?
Unlike small-molecule drugs, Emgality is not protected through the FDA Orange Book. Biologic patent information is handled through the Purple Book framework and through patent disclosures made by the reference-product sponsor and biosimilar applicant.
The Emgality estate is expected to include several patent categories:
| Patent category | Protected subject matter | Commercial relevance |
|---|---|---|
| Antibody composition | Galcanezumab antibody sequences and binding characteristics | Core product protection |
| Epitope and binding claims | Interaction with CGRP or related target structures | Can limit design-around options |
| Pharmaceutical composition | Stabilized antibody formulations and excipient combinations | Protects commercial drug product |
| Delivery system | Prefilled syringe, pen, or administration configuration | May delay device substitution |
| Therapeutic use | Migraine prevention and cluster-headache treatment | Supports indication-specific enforcement |
| Manufacturing | Cell culture, purification, and production processes | Creates process and know-how barriers |
The strongest claims are generally composition-of-matter claims covering the antibody or its defining sequence and binding properties. Formulation, device, and method-of-use claims can remain commercially important, but their enforceability often depends more heavily on claim construction and product-specific facts.
A competitor may avoid one patent family by using a different antibody sequence or formulation while still pursuing a biosimilar to the reference product. That makes the estate’s cumulative coverage more important than any single patent.
What is the Orange Book status of Emgality?
Emgality does not have an Orange Book listing because it is a biologic approved under a BLA rather than a small-molecule drug approved under an NDA.
The relevant regulatory framework is the FDA’s Purple Book. The Purple Book identifies licensed biological products and biosimilar or interchangeable biosimilar relationships. It does not replicate the Orange Book’s small-molecule patent-listing and Paragraph IV certification system.[7]
As a result:
- There is no conventional Orange Book patent list for Emgality.
- A biosimilar applicant does not file an ordinary Paragraph IV certification against Emgality.
- Patent disputes proceed under the BPCIA patent-exchange process, commonly called the patent dance, or through other litigation strategies.
- The biosimilar applicant may provide notice of commercial marketing before launch.
- A reference-product sponsor can seek preliminary or permanent injunctive relief.
Which companies are challenging Emgality exclusivity?
No approved Emgality biosimilar has been identified in the FDA’s public biologic-product records reviewed for this analysis. Publicly visible commercial pressure currently comes primarily from branded competitors rather than a disclosed biosimilar launch program.
The principal competitive companies are:
- AbbVie, through Qulipta and Ubrelvy.
- Pfizer, through Nurtec ODT.
- Amgen and Novartis, through Aimovig.
- Teva, through Ajovy.
- AbbVie, through Botox for chronic migraine.
- Manufacturers of established generic oral preventive medicines.
A future biosimilar challenge would likely come from a large biologics manufacturer or a specialty-generic company with antibody manufacturing capacity. The technical barrier is meaningful but not prohibitive. Galcanezumab is a conventional monoclonal antibody rather than a highly complex antibody-drug conjugate or multispecific biologic.
What Paragraph IV risks exist for Emgality?
Traditional Paragraph IV risk is not applicable because Emgality is not an NDA product. The comparable risk is a BPCIA biosimilar patent challenge.
A biosimilar applicant could challenge Emgality through:
- Patent invalidity claims.
- Non-infringement positions.
- Attempts to design around formulation or device patents.
- Declaratory-judgment litigation.
- Commercial launch after statutory notice.
- Settlement arrangements establishing a delayed launch date.
The timing of a biosimilar launch would depend on patent litigation, regulatory approval, manufacturing readiness, payer contracts, and the commercial attractiveness of the market at launch. Even after regulatory approval, a biosimilar may not immediately obtain preferred formulary status.
What formulation and manufacturing barriers protect Emgality?
Emgality’s manufacturing process requires mammalian-cell expression, purification, viral-clearance controls, analytical characterization, and sterile fill-finish operations. These requirements create a higher entry barrier than the production of conventional tablets.
The most important technical barriers are:
- Matching the reference antibody’s primary and higher-order structure.
- Demonstrating comparable glycosylation and charge-variant profiles.
- Establishing consistent potency and binding activity.
- Validating a scalable cell-culture process.
- Demonstrating stability across the commercial shelf life.
- Obtaining an adequate supply of prefilled delivery devices.
- Meeting FDA requirements for analytical similarity and immunogenicity assessment.
These barriers do not create permanent exclusivity. They increase development cost, extend timelines, and favor companies with established monoclonal-antibody infrastructure.
What litigation and settlement risks affect Emgality?
Patent litigation risk is structurally lower before a biosimilar filing becomes public. Once a biosimilar applicant initiates the BPCIA process, Lilly could assert composition, formulation, manufacturing, device, and method-of-use patents.
No broad public settlement framework has established an Emgality biosimilar launch date. The likely settlement variables would include:
- Earliest agreed launch date.
- Patent-license scope.
- Royalty or other consideration.
- Manufacturing restrictions.
- Product-label limitations.
- Treatment of cluster-headache use.
- Confidentiality provisions.
- Resolution of device patents.
A settlement could preserve Lilly’s market position beyond 2030 while allowing a biosimilar entrant before the last asserted patent expires.
How strong is the Emgality patent estate?
The estate is commercially strong but not immune to erosion.
| Factor | Assessment |
|---|---|
| Core antibody protection | Strongest element |
| Regulatory exclusivity | Clear through approximately September 2030 |
| Formulation protection | Potentially useful, but more vulnerable to design-around arguments |
| Method-of-use claims | Relevant to migraine and cluster headache, with indication-specific value |
| Device protection | Can complicate substitution but rarely prevents all biologic competition |
| Manufacturing claims | May increase litigation and process-development risk |
| Biosimilar barrier | Moderate to high |
| Long-term durability | Dependent on patent validity, claim scope, and settlement terms |
The estate should be valued as a layered system rather than by counting patent families. An invalidated core composition claim would weaken the product substantially. A surviving composition patent combined with formulation and use patents could support delayed biosimilar entry.
What generic launch scenarios exist for Emgality?
There are three credible post-exclusivity scenarios.
Scenario 1: No biosimilar before the mid-2030s
Lilly retains meaningful protection through patent enforcement or settlement. Revenue declines gradually as branded competition and payer pressure increase, but no immediate substitution occurs.
Scenario 2: One biosimilar launches after 2030
The first biosimilar receives a contracting advantage. Lilly responds through rebates, patient support, device differentiation, or contracting with specialty pharmacies. Revenue declines faster in government and managed-care channels.
Scenario 3: Multiple biosimilars launch after patent resolution
Competition produces sharper price pressure. The first entrant may receive preferred status, while later entrants compete primarily through discounts and supply reliability. Lilly’s net price and unit share both become vulnerable.
A rapid small-molecule-style collapse is less likely because biologic substitution depends on interchangeability, payer policy, physician behavior, and supply-chain contracting.
What is Emgality’s geographic coverage?
Emgality is marketed in the United States and other major pharmaceutical markets, including Europe and Japan, subject to local approvals, reimbursement rules, and naming conventions. Patent term and biosimilar entry risk vary by country.
The United States remains the most important market because of its high specialty-drug prices and large commercial migraine population. European markets typically create earlier price pressure through health-technology assessment, tendering, and reference-pricing systems. Japan and other regulated markets can impose additional reimbursement and post-approval requirements.
Lilly’s international revenue disclosures do not generally provide a complete country-by-country Emgality breakdown. Geographic exposure is therefore best assessed through regional product availability and reimbursement rather than public product-level sales.
What is Emgality’s FDA regulatory status?
Emgality is FDA-approved for:
- Preventive treatment of migraine in adults.
- Preventive treatment of episodic cluster headache in adults.
It is not approved as an acute rescue treatment for migraine. That limitation matters because Qulipta, Ubrelvy, and Nurtec ODT give competitors broader oral-CGRP positioning across preventive and acute-use segments.
The FDA label also contains safety information regarding hypersensitivity, injection-site reactions, and other adverse reactions. Continued commercial growth depends on maintaining supply, safety compliance, and reimbursement access.[1]
Key Takeaways
- Emgality generated approximately $817 million in 2024 revenue, according to Lilly’s reported product sales.
- Revenue growth remains positive but faces pressure from oral gepants and competing CGRP antibodies.
- FDA biologic exclusivity is expected to run through approximately September 2030.
- Patent protection may extend into the mid-2030s or later, but the exact loss-of-exclusivity date depends on individual patent claims and litigation.
- Emgality has no conventional Orange Book listing and is not subject to a standard Paragraph IV pathway.
- No approved Emgality biosimilar was identified in the public FDA records reviewed.
- The core antibody composition estate is more important than formulation or device patents.
- The most likely initial erosion mechanism is payer-driven branded competition, followed later by biosimilar entry.
- Lilly’s revenue exposure is material at the product level but modest relative to its diabetes, obesity, oncology, and immunology franchises.
- A biosimilar launch would likely produce gradual rather than immediate substitution because of biologic contracting and interchangeability rules.
FAQs
Is Emgality a biologic or a generic drug?
Emgality is a biologic monoclonal antibody. A conventional generic cannot be substituted for it. Any follow-on product would proceed through the FDA biosimilar pathway.
Can a biosimilar launch before Emgality’s 2030 exclusivity date?
FDA approval and commercial launch timing are constrained by reference-product exclusivity and patent rights. A biosimilar may be approved before commercial launch rights mature, depending on the applicable statutory and patent framework.
Does Emgality have an interchangeability advantage?
No interchangeable biosimilar for Emgality was identified in the public FDA records reviewed. An interchangeable designation would require additional FDA findings beyond biosimilarity.
Which competitor poses the greatest commercial risk to Emgality?
Oral gepants, particularly Qulipta and Nurtec ODT, pose the greatest commercial risk because they reduce the inconvenience associated with injectable prevention and can occupy broader treatment positions.
Is Emgality’s cluster-headache indication commercially important?
It is strategically differentiating but smaller than the migraine-prevention market. The indication strengthens product positioning without eliminating the larger competitive pressure from migraine-prevention drugs.
References
-
U.S. Food and Drug Administration. (2024). Emgality (galcanezumab-gnlm) prescribing information. FDA.
-
Eli Lilly and Company. (2022). 2021 annual report. Eli Lilly and Company.
-
Eli Lilly and Company. (2023). 2022 annual report. Eli Lilly and Company.
-
Eli Lilly and Company. (2024). 2023 annual report. Eli Lilly and Company.
-
Eli Lilly and Company. (2025). 2024 annual report. Eli Lilly and Company.
-
U.S. Food and Drug Administration. (2024). Biologics price competition and innovation act of 2009. FDA.
-
U.S. Food and Drug Administration. (2024). Purple Book: Database of licensed biological products. FDA.
More… ↓
