Last updated: September 23, 2026
ONIVYDE, Ipsen’s liposomal irinotecan product, has moved from a second-line pancreatic-cancer therapy to a broader pancreatic-cancer franchise following the 2024 U.S. approval of the NALIRIFOX regimen. The approval expanded the addressable market, while competition from FOLFIRINOX, gemcitabine plus nab-paclitaxel, and future irinotecan generics remains substantial. Ipsen’s commercial trajectory depends on first-line adoption, treatment-center familiarity, reimbursement, and the durability of its formulation and method-of-use patent protection.
What is ONIVYDE and how does it work?
ONIVYDE is a pegylated liposomal formulation of irinotecan hydrochloride trihydrate. It delivers irinotecan in a long-circulating liposomal system designed to increase exposure to the tumor microenvironment and release the active drug over time.
| Attribute |
ONIVYDE |
| Active ingredient |
Irinotecan hydrochloride trihydrate |
| Delivery system |
Pegylated liposomal injection |
| Developer and marketer |
Ipsen |
| Initial U.S. approval |
October 22, 2015 |
| Original indication |
Metastatic pancreatic adenocarcinoma after gemcitabine-based therapy |
| Expanded U.S. indication |
First-line metastatic pancreatic adenocarcinoma with oxaliplatin, fluorouracil and leucovorin |
| Key regimen |
NALIRIFOX |
| Administration |
Intravenous infusion |
| Therapeutic class |
Topoisomerase I inhibitor, liposomal formulation |
The original approval was based on the NAPOLI-1 study, which showed improved overall survival for ONIVYDE combined with fluorouracil and leucovorin compared with fluorouracil and leucovorin alone in previously treated metastatic pancreatic cancer.[1]
What FDA approvals support ONIVYDE sales?
ONIVYDE has two commercially important U.S. indications.
Second-line metastatic pancreatic cancer
The 2015 approval covered ONIVYDE in combination with fluorouracil and leucovorin for patients with metastatic pancreatic adenocarcinoma whose disease had progressed after gemcitabine-based therapy.[2]
This indication positioned ONIVYDE as a later-line treatment. The commercial opportunity was constrained by:
- Rapid progression of metastatic pancreatic cancer.
- Limited treatment eligibility after first-line therapy.
- Competition from conventional irinotecan-based regimens.
- Treatment-center preference for established chemotherapy combinations.
- The need for intravenous administration.
First-line metastatic pancreatic cancer
On February 13, 2024, the FDA approved ONIVYDE in combination with oxaliplatin, fluorouracil and leucovorin for first-line treatment of adults with metastatic pancreatic adenocarcinoma.[3]
The approval was based on NAPOLI-3, a randomized Phase 3 study comparing NALIRIFOX with nab-paclitaxel plus gemcitabine. NALIRIFOX improved median overall survival and progression-free survival:
| NAPOLI-3 outcome |
NALIRIFOX |
Gemcitabine plus nab-paclitaxel |
| Median overall survival |
11.1 months |
9.2 months |
| Median progression-free survival |
7.4 months |
5.6 months |
| Primary comparison |
Statistically significant |
Reference arm |
The first-line approval materially changed ONIVYDE’s market position. Instead of competing only for patients who had already received gemcitabine, ONIVYDE could be used at the initial treatment decision, where the patient pool is larger and treatment duration is potentially longer.[4]
How large is the ONIVYDE market opportunity?
The market is concentrated in metastatic pancreatic adenocarcinoma, a high-mortality cancer with substantial unmet need. In the United States, pancreatic cancer accounts for more than 60,000 new cases annually, although only a portion of patients present with metastatic disease or remain eligible for systemic treatment.[5]
The first-line approval expands the eligible population in three ways:
- It moves ONIVYDE earlier in the treatment sequence.
- It allows use before exposure to gemcitabine-based therapy.
- It gives oncologists a labeled alternative to gemcitabine plus nab-paclitaxel.
The market opportunity is still limited by the size of the metastatic population and by the fact that FOLFIRINOX remains a major standard-of-care option. ONIVYDE is not a broad solid-tumor product. Its commercial value depends heavily on pancreatic-cancer treatment guidelines and the adoption of NALIRIFOX.
U.S. versus international opportunity
The United States is the principal value market because:
- ONIVYDE received the earliest regulatory approvals there.
- Oncology reimbursement is relatively favorable for branded products.
- Ipsen has direct commercial infrastructure.
- NALIRIFOX adoption is likely to occur first in U.S. academic and high-volume cancer centers.
International growth is more dependent on country-specific reimbursement decisions, health technology assessments, chemotherapy budgets and local treatment guidelines. European uptake may be slower where FOLFIRINOX is deeply established and price controls are stronger.
What is ONIVYDE’s financial trajectory?
Ipsen has identified ONIVYDE as an oncology growth product, but its public reporting does not provide a uniform, standalone global revenue history for every reporting period. The company reports ONIVYDE within its specialty-care and oncology disclosures, with growth linked to U.S. demand, second-line use and the launch of the NALIRIFOX indication.[6]
The financial trajectory has four phases:
| Period |
Commercial phase |
Financial effect |
| 2015-2017 |
Initial U.S. launch and second-line use |
Establishment of branded liposomal irinotecan sales |
| 2018-2022 |
Expansion of commercial infrastructure and international access |
Gradual oncology-franchise growth |
| 2023 |
Pre-launch preparation for NAPOLI-3 approval |
Increased clinical and commercial investment |
| 2024 onward |
First-line U.S. launch |
Potential step-up in treatment volume and revenue per patient |
The first-line label is the main revenue catalyst. First-line patients generally represent a larger pool than later-line patients, and a successful regimen can produce longer treatment exposure. The sales uplift will depend on whether physicians use NALIRIFOX broadly or reserve it for selected patients.
Revenue quality is also important. ONIVYDE’s value is supported by a differentiated delivery system and clinical data, but the drug is administered with generic chemotherapy agents. Ipsen captures the branded value of the liposomal irinotecan component, while oxaliplatin, fluorouracil and leucovorin are largely commoditized.
How does ONIVYDE compare with competing pancreatic-cancer regimens?
ONIVYDE versus FOLFIRINOX
FOLFIRINOX uses conventional irinotecan, oxaliplatin, fluorouracil and leucovorin. NALIRIFOX substitutes liposomal irinotecan for conventional irinotecan.
| Factor |
NALIRIFOX |
FOLFIRINOX |
| Irinotecan component |
Liposomal irinotecan |
Conventional irinotecan |
| Regulatory status |
FDA-approved first-line regimen for metastatic pancreatic adenocarcinoma |
Widely used regimen; specific label positioning varies |
| Evidence base |
NAPOLI-3 |
Established clinical practice and prior trials |
| Differentiation |
Formulation, pharmacokinetics and Phase 3 data |
Lower drug cost and long clinical experience |
| Commercial risk |
Premium branded price |
Generic components and entrenched use |
NALIRIFOX must show enough clinical and operational value to justify its premium over conventional FOLFIRINOX. Physicians may favor it in centers that value the NAPOLI-3 data, while cost-sensitive systems may continue using conventional irinotecan.
ONIVYDE versus gemcitabine plus nab-paclitaxel
Gemcitabine plus nab-paclitaxel remains a major first-line competitor. It has extensive real-world use, broad physician familiarity and a defined role in treatment guidelines.
NALIRIFOX has the advantage of positive head-to-head NAPOLI-3 data. Gemcitabine plus nab-paclitaxel retains commercial strength through established prescribing patterns and the availability of a mature treatment pathway.
ONIVYDE versus generic irinotecan
Generic irinotecan is the most important price-based substitute. It is not therapeutically identical to ONIVYDE because ONIVYDE uses a pegylated liposomal delivery platform, but oncologists may view both as irinotecan-containing options within multi-agent chemotherapy.
The key commercial question is whether the liposomal formulation produces enough clinical or tolerability benefit to sustain a branded premium.
What patents and exclusivity protect ONIVYDE?
ONIVYDE’s protection is based on a combination of regulatory exclusivity, formulation patents and method-of-use claims.
Regulatory exclusivity
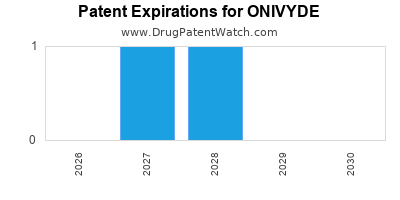
The original U.S. approval received orphan-drug exclusivity for metastatic pancreatic cancer. The seven-year orphan period associated with the 2015 approval expired in 2022.[2]
The 2024 first-line approval may create additional protection for qualifying clinical investigations under the Federal Food, Drug, and Cosmetic Act. The practical impact depends on the scope of the FDA’s exclusivity determination and the Orange Book listing applicable to the approved supplement.[3]
Formulation patents
The core intellectual-property value is the pegylated liposomal irinotecan formulation. Formulation claims can be more commercially important than claims covering conventional irinotecan because they target the delivery platform used in the branded product.
Potential generic applicants must address:
- Liposome composition.
- Drug-to-lipid ratio.
- Particle-size distribution.
- Encapsulation and release characteristics.
- Pharmacokinetic comparability.
- Manufacturing controls.
- Stability and sterility.
These technical requirements create a higher development barrier than a conventional small-molecule irinotecan injection.
Method-of-use patents
Method-of-use protection can cover the administration of liposomal irinotecan in pancreatic cancer, including combination regimens with fluorouracil, leucovorin and oxaliplatin. Such claims can support litigation against an ANDA applicant that seeks approval for an indication covered by the patent.
Method-of-use protection is vulnerable to:
- Carve-out strategies.
- Induced-infringement disputes.
- Invalidity challenges.
- Noninfringing labeling arguments.
- Differences between the proposed generic label and the protected indication.
When could generic ONIVYDE enter the U.S. market?
No standard small-molecule generic should be assumed to enter immediately after the expiration of the original orphan exclusivity. A generic version of ONIVYDE would likely require an ANDA or another abbreviated regulatory pathway supported by product-specific equivalence data.
Potential entry scenarios include:
| Scenario |
Commercial result |
| No approved ANDA before key patents expire |
Ipsen retains branded sales |
| One generic entrant |
Moderate price erosion, limited initial share loss |
| Multiple liposomal irinotecan entrants |
Rapid price compression and formulary substitution |
| Carve-out of protected indication |
Partial generic competition |
| Patent settlement with delayed entry |
Limited near-term erosion, defined future launch date |
The likely barrier is not only patent expiry. It is also the complexity of developing a reproducible liposomal product and satisfying FDA requirements for pharmaceutical equivalence and bioequivalence.
Which companies challenge ONIVYDE?
Publicly disclosed competitive pressure comes primarily from:
- Manufacturers of conventional irinotecan.
- Developers of liposomal irinotecan or other nanomedicine formulations.
- Suppliers of gemcitabine and nab-paclitaxel.
- Developers of next-generation pancreatic-cancer therapies.
- Oncology companies promoting first-line FOLFIRINOX or modified FOLFIRINOX.
No major biosimilar pathway applies to ONIVYDE because it is a complex small-molecule liposomal product rather than a biologic. The relevant threat is generic or follow-on liposomal competition, not biosimilar substitution.
What litigation and settlement risks affect ONIVYDE?
The main litigation risks are likely to involve:
- ANDA Paragraph IV challenges.
- Validity of liposomal formulation patents.
- Obviousness and written-description attacks.
- Noninfringement of method-of-use claims.
- Patent-term calculations.
- Regulatory exclusivity disputes.
- Labeling strategies for unprotected indications.
The commercial impact of a Paragraph IV filing would depend on the patents listed in the FDA Orange Book at the time of filing, the asserted claims, and whether Ipsen obtains a 30-month stay of FDA approval under the Hatch-Waxman framework.[7]
No widely reported settlement has established an earlier generic ONIVYDE launch date in the public record through the latest major company and FDA disclosures cited here.
How strong is the ONIVYDE competitive and patent estate?
ONIVYDE has a moderately strong commercial position rather than an unassailable monopoly.
Strengths
- FDA-approved first-line and second-line pancreatic-cancer uses.
- Positive Phase 3 head-to-head evidence from NAPOLI-3.
- Complex liposomal formulation.
- Ipsen’s oncology commercial infrastructure.
- Potential for treatment-sequence expansion.
- Limited direct substitutes with the same formulation.
Weaknesses
- Narrow disease concentration.
- High competition from FOLFIRINOX.
- Generic availability of conventional irinotecan.
- Intravenous administration.
- Price sensitivity among payers.
- Dependence on treatment guidelines and center-level adoption.
- Eventual exposure to formulation and method-of-use patent challenges.
What generic launch risks exist for ONIVYDE?
The most credible near-term risk is gradual erosion rather than an immediate collapse in sales. A generic entrant would first target price-sensitive accounts and payers. Uptake would be slower if oncologists view the liposomal delivery system and NAPOLI-3 evidence as clinically meaningful.
A more severe erosion scenario would require several conditions:
- FDA approval of a therapeutically substitutable liposomal irinotecan product.
- Successful challenge to key formulation patents.
- Broad payer preference for the generic.
- Continued use of ONIVYDE’s label by generic competitors through permissible labeling.
- Limited differentiation in real-world outcomes.
Key Takeaways
- ONIVYDE is a liposomal irinotecan product marketed by Ipsen for metastatic pancreatic adenocarcinoma.
- Its most important growth driver is the February 2024 FDA approval of first-line NALIRIFOX.
- The product competes with FOLFIRINOX and gemcitabine plus nab-paclitaxel, not only with conventional irinotecan.
- The orphan exclusivity associated with the original 2015 approval expired in 2022.
- The strongest continuing barriers are the liposomal formulation, manufacturing complexity and use-specific patent claims.
- Revenue growth depends on first-line adoption, reimbursement and guideline penetration.
- Generic risk is likely to emerge through specialized liposomal products rather than a simple conventional irinotecan substitute.
- ONIVYDE has meaningful commercial expansion potential but remains concentrated in one difficult-to-treat cancer indication.
FAQs
Is ONIVYDE a chemotherapy drug?
Yes. ONIVYDE is a liposomal formulation of irinotecan, a topoisomerase I inhibitor used as part of combination chemotherapy.
What regimen contains ONIVYDE?
The first-line regimen is NALIRIFOX, which combines ONIVYDE with oxaliplatin, fluorouracil and leucovorin. ONIVYDE is also used with fluorouracil and leucovorin after prior gemcitabine-based treatment.
Does ONIVYDE have biosimilar competition?
No. ONIVYDE is a complex liposomal small-molecule product, so the relevant competitive pathway is generic or follow-on liposomal irinotecan development rather than biosimilar approval.
Why is ONIVYDE more expensive than conventional irinotecan?
ONIVYDE uses a pegylated liposomal delivery system that requires specialized formulation, manufacturing, quality testing and clinical development. Conventional irinotecan is available as a mature generic injection.
What is the main investment risk for ONIVYDE?
The main risk is slower-than-expected first-line adoption because oncologists may continue using FOLFIRINOX or gemcitabine plus nab-paclitaxel, particularly where payers resist the premium cost of liposomal irinotecan.
References
-
Wang-Gillam, A., Li, C.-P., Bodoky, G., Dean, A., Shan, Y.-S., Jameson, G., Macarulla, T., Lee, K.-H., Cunningham, D., Blanc, J.-F., Hubner, R. A., Choi, M., Siveke, J. T., Mirakhur, B., & Chen, L.-T. (2016). Nanoliposomal irinotecan with fluorouracil and folinic acid in metastatic pancreatic cancer after previous gemcitabine-based therapy: A global, randomised, open-label, phase 3 trial. The Lancet, 387(10018), 545-557.
-
U.S. Food and Drug Administration. (2015). FDA approves Onivyde for metastatic pancreatic cancer. FDA.
-
U.S. Food and Drug Administration. (2024). FDA approves liposomal irinotecan combination for first-line treatment of metastatic pancreatic adenocarcinoma. FDA.
-
Wainberg, Z. A., Bekaii-Saab, T., Janssen, F., et al. (2023). NALIRIFOX versus nab-paclitaxel plus gemcitabine in treatment-naive patients with metastatic pancreatic ductal adenocarcinoma: The phase 3 NAPOLI 3 trial. The Lancet, 402(10397), 1272-1281.
-
National Cancer Institute. (2024). Pancreatic cancer statistics. U.S. Department of Health and Human Services.
-
Ipsen. (2024). Annual report 2023. Ipsen S.A.
-
U.S. Food and Drug Administration. (2024). Approved drug products with therapeutic equivalence evaluations: Orange Book. FDA.