Share This Page
Drug Sales Trends for WARFARIN
✉ Email this page to a colleague
Payment Methods and Pharmacy Types for WARFARIN (2022)
Revenues by Pharmacy Type
Units Sold by Pharmacy Type
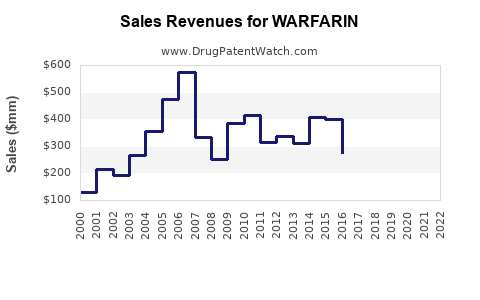
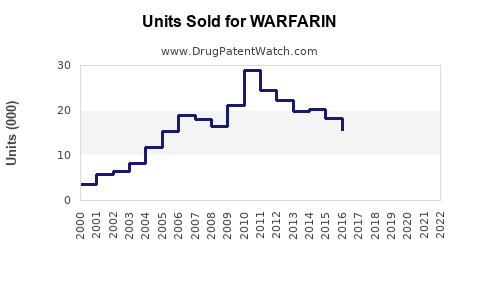
Annual Sales Revenues and Units Sold for WARFARIN
| Drug Name | Revenues (USD) | Units | Year |
|---|---|---|---|
| WARFARIN | ⤷ Start Trial | ⤷ Start Trial | 2022 |
| WARFARIN | ⤷ Start Trial | ⤷ Start Trial | 2021 |
| WARFARIN | ⤷ Start Trial | ⤷ Start Trial | 2020 |
| WARFARIN | ⤷ Start Trial | ⤷ Start Trial | 2019 |
| WARFARIN | ⤷ Start Trial | ⤷ Start Trial | 2018 |
| >Drug Name | >Revenues (USD) | >Units | >Year |
Warfarin Market Analysis and Sales Projections Through 2030
Warfarin is a mature, low-cost anticoagulant with declining clinical use in high-income markets but durable demand in patients with mechanical heart valves, severe renal impairment, antiphospholipid syndrome, and limited access to direct oral anticoagulants. The commercial market is driven by prescription volume rather than pricing. Warfarin has no meaningful remaining originator exclusivity, no biosimilar pathway, and limited patent protection. Base-case global sales are projected to remain broadly stable in nominal volume through 2030, while revenue growth is likely to come from emerging markets and monitoring services rather than higher drug prices.
What is the current warfarin market size?
Public sources do not provide a single audited global figure for warfarin sales. Commercial market-research estimates vary because some reports include anticoagulation-monitoring services, while others count only tablets or include all vitamin K antagonists.
A reasonable 2025 estimate for the global warfarin drug market is approximately $0.7 billion to $1.1 billion at manufacturer and pharmacy-channel value. The range reflects differences in geographic coverage, generic pricing, hospital purchasing, and whether combination products and active pharmaceutical ingredient sales are included.
| Metric | 2025 estimate |
|---|---|
| Global warfarin drug-market value | $0.7 billion-$1.1 billion |
| Estimated annual treatment courses | 20 million-35 million |
| Core dosage forms | 1 mg, 2 mg, 2.5 mg, 3 mg, 4 mg, 5 mg, 6 mg, 7.5 mg, 10 mg tablets |
| Main active ingredient | Warfarin sodium |
| Dominant commercial model | Generic prescription sales |
| Principal markets | United States, Europe, Japan, China, India, Latin America |
| Expected volume trend through 2030 | Flat to moderately declining |
| Expected nominal revenue trend through 2030 | Flat to low-single-digit growth |
The number of patients receiving warfarin is difficult to calculate because therapy duration varies substantially. Some patients receive lifelong treatment for mechanical valves, while others receive several months of treatment for venous thromboembolism or atrial fibrillation.
Warfarin remains clinically important despite competition from apixaban, rivaroxaban, dabigatran, and edoxaban. The American College of Cardiology and other clinical bodies generally favor direct oral anticoagulants for eligible patients with nonvalvular atrial fibrillation, but warfarin remains preferred or necessary in several settings, including mechanical prosthetic heart valves and moderate-to-severe mitral stenosis [1, 2].
How is the warfarin market segmented?
By indication
Atrial fibrillation historically represented the largest outpatient indication for warfarin. Its share has declined as direct oral anticoagulants have displaced warfarin in eligible patients.
| Indication | Current commercial outlook |
|---|---|
| Mechanical heart valves | Durable, high-retention segment |
| Nonvalvular atrial fibrillation | Continued decline in developed markets |
| Venous thromboembolism | Declining share, but persistent in price-sensitive markets |
| Antiphospholipid syndrome | Niche segment with continued warfarin use |
| Left ventricular thrombus | Specialist-driven, variable duration |
| Severe chronic kidney disease | Relative support for warfarin where DOAC use is constrained |
| Pediatric anticoagulation | Small but specialized demand |
| Long-term thrombosis prevention | Stable in selected high-risk patients |
The mechanical-valve segment is the strongest structural support for warfarin. Current direct oral anticoagulants are not interchangeable with warfarin for mechanical valve patients. The RE-ALIGN trial of dabigatran in mechanical heart valves was terminated early because of excess thromboembolic and bleeding events [3].
By geography
The United States remains a large market by prescription value but has experienced substantial substitution by DOACs. Europe has followed a similar pattern. China, India, Southeast Asia, Latin America, and parts of the Middle East have stronger price-driven demand and lower DOAC penetration.
| Region | 2025 market position | 2030 outlook |
|---|---|---|
| United States | High prescription volume, declining share | Low-single-digit annual volume decline |
| Western Europe | Mature generic market | Declining volume |
| Eastern Europe | More price-sensitive | Stable to modest growth |
| China | Large patient pool, mixed access | Stable to moderate growth |
| India | Low-cost generic supply | Moderate unit growth, low pricing |
| Latin America | Variable reimbursement | Stable demand |
| Middle East and Africa | Uneven access and monitoring | Selective growth in urban markets |
The largest geographic risk is substitution by DOACs. The largest geographic opportunity is expansion in countries where warfarin's low acquisition cost outweighs the burden of international normalized ratio monitoring.
What are the main growth drivers for warfarin sales?
Warfarin's market is supported by clinical, economic, and infrastructure factors.
First, its price is substantially lower than branded or recently introduced anticoagulants. Generic warfarin is available from multiple manufacturers, and tablet manufacturing is technically established.
Second, warfarin has a long clinical history and extensive physician familiarity. Hospitals and anticoagulation clinics have established dosing protocols, laboratory workflows, and reversal procedures.
Third, warfarin is usable in patient populations where DOACs are less suitable. These include mechanical-valve patients, some patients with severe renal dysfunction, and patients with antiphospholipid syndrome. The European Alliance of Associations for Rheumatology recommends vitamin K antagonist therapy for many high-risk antiphospholipid syndrome patients [4].
Fourth, warfarin's anticoagulant effect can be measured and adjusted through INR testing. Monitoring increases treatment burden but can be commercially relevant for anticoagulation-management providers, home-testing suppliers, and telehealth platforms.
What factors are reducing warfarin sales?
The primary constraint is DOAC substitution. In the United States, DOACs have become the dominant oral anticoagulant class for many patients with nonvalvular atrial fibrillation and venous thromboembolism. Their fixed dosing, fewer food interactions, and reduced monitoring burden make them commercially attractive despite higher drug costs.
Warfarin also has a narrow therapeutic index. Its effectiveness and safety are affected by dietary vitamin K, drug interactions, illness, adherence, alcohol use, and genetic variability. The FDA label identifies numerous drug and dietary interactions and requires individualized dosing based on INR response [5].
Other constraints include:
- Frequent laboratory testing.
- Higher clinical-management costs.
- Bleeding risk when INR is outside the therapeutic range.
- Patient preference for fixed-dose therapy.
- Generic supplier consolidation and occasional product shortages.
- Reduced use in primary care as anticoagulation management shifts toward DOAC protocols.
Warfarin will therefore remain a clinically necessary product but a weaker growth product.
What are the projected warfarin sales through 2030?
The following projection is a market model rather than reported company guidance. It assumes a 2025 global drug-market base of $0.9 billion, annual volume decline in developed markets, moderate unit growth in emerging markets, and low inflationary price increases.
| Year | Base-case global sales | Year-over-year growth | Main assumption |
|---|---|---|---|
| 2025 | $0.90 billion | - | Baseline |
| 2026 | $0.89 billion | -1.1% | DOAC substitution offsets emerging-market growth |
| 2027 | $0.89 billion | 0.0% | Stable generic demand |
| 2028 | $0.90 billion | 1.1% | Emerging-market volume and price normalization |
| 2029 | $0.91 billion | 1.1% | Persistent mechanical-valve demand |
| 2030 | $0.92 billion | 1.1% | Low nominal growth, declining developed-market volume |
Scenario analysis
| Scenario | 2030 sales | Market condition |
|---|---|---|
| Downside | $0.65 billion-$0.75 billion | Faster DOAC conversion, lower generic prices, fewer monitoring-dependent patients |
| Base case | $0.85 billion-$1.0 billion | Stable mechanical-valve demand and emerging-market growth |
| Upside | $1.05 billion-$1.25 billion | DOAC affordability constraints, supply disruptions, increased use in renal and antiphospholipid populations |
The downside case is more likely in the United States and Western Europe than globally. The upside case depends less on new clinical adoption than on slower DOAC penetration in lower-income healthcare systems.
How does warfarin compare with Eliquis, Xarelto, Pradaxa, and Savaysa?
Warfarin has the lowest acquisition cost but the highest monitoring burden among the principal oral anticoagulants.
| Product | Active ingredient | Generic status | Monitoring | Main competitive position |
|---|---|---|---|---|
| Coumadin/Jantoven and generics | Warfarin sodium | Generic | Required INR monitoring | Low-cost, mechanical-valve and specialist use |
| Eliquis | Apixaban | Patent and regulatory exclusivity materially stronger than warfarin | No routine INR monitoring | Leading DOAC in atrial fibrillation and VTE |
| Xarelto | Rivaroxaban | Patent protection historically extensive; generic entry timing varies by jurisdiction | No routine INR monitoring | Broad indication base |
| Pradaxa | Dabigatran | Mature product with generic competition in some markets | No routine INR monitoring | Earlier DOAC entrant |
| Savaysa/Lixiana | Edoxaban | Market-dependent exclusivity | No routine INR monitoring | Smaller DOAC position |
Warfarin's economic advantage is strongest when drug acquisition cost is the primary reimbursement concern. DOACs gain advantage when healthcare systems value reduced laboratory monitoring, fewer clinic visits, and simpler administration.
What patents protect warfarin?
The core composition-of-matter and product patents for warfarin expired decades ago. Warfarin was discovered and commercialized in the mid-20th century, placing its original patent estate well outside the modern 20-year patent term framework.
| Patent category | Current status |
|---|---|
| Warfarin active-ingredient patent | Expired |
| Warfarin sodium composition patents | Expired or commercially irrelevant |
| Original Coumadin product patents | Expired |
| Basic tablet formulation patents | Expired |
| Routine dosing and INR-monitoring concepts | Generally unprotectable or expired |
| Modern digital dosing tools | Potentially patentable, but separate from warfarin itself |
| Manufacturing process patents | Potentially jurisdiction-specific, but unlikely to block ordinary generic supply |
No active patent estate appears capable of excluding ordinary generic warfarin tablets from the global market. Any current patent risk would more likely involve a specialized formulation, delivery system, diagnostic-monitoring platform, packaging technology, or software-enabled dosing method rather than warfarin sodium itself.
What is the FDA regulatory and Orange Book status of warfarin?
Warfarin is an FDA-approved prescription anticoagulant. FDA-approved products include warfarin sodium tablets marketed under generic names and under products such as Jantoven. Coumadin was the historic branded product associated with Bristol-Myers Squibb.
The FDA label identifies warfarin as a vitamin K antagonist and includes boxed warnings for major or fatal bleeding, the need for individualized dosing, and the requirement for regular INR monitoring [5].
Because the core patents have expired, warfarin is a mature abbreviated new drug application market. Orange Book listings, where applicable to individual products, do not create a meaningful product-level exclusivity barrier comparable to those for newer small-molecule products. Label differences, dosage strengths, manufacturing approvals, and supply reliability are more commercially relevant than patent status.
Are there Paragraph IV challenges to warfarin?
Paragraph IV litigation is not a material current market issue for conventional warfarin tablets. Generic versions have been marketed for many years, and the relevant originator exclusivity periods have expired.
A Paragraph IV dispute could arise only around a newly approved, differentiated warfarin product, such as:
- A novel extended-release formulation.
- A fixed-dose combination.
- A proprietary delivery system.
- A digital dosing and monitoring product linked to a drug claim.
- A new method-of-use claim with commercial relevance.
Those products would face separate patent and regulatory analysis. They would not restore exclusivity to conventional warfarin tablets.
What formulation patents protect warfarin?
Traditional immediate-release warfarin tablets have little defensible patent protection. Generic manufacturers can produce multiple strengths using established excipient systems and conventional tablet compression.
Potentially protectable areas include:
- Pediatric liquid formulations.
- Taste-masked oral liquids.
- Unit-dose adherence packaging.
- Modified-release formulations.
- Fixed-dose combinations.
- Co-packaged INR testing and dosing systems.
- Stability improvements for moisture-sensitive products.
- Hospital-ready injectable or emergency-use presentations, subject to regulatory approval.
These opportunities have limited market size. The commercial barrier is more likely to be clinical adoption and reimbursement than patent enforceability.
What manufacturing and intellectual-property barriers affect warfarin?
Manufacturing barriers are low compared with biologics, sterile injectables, or complex drug-device combinations. Warfarin is a small-molecule tablet product with established synthesis and formulation processes.
The main operational risks are:
- Active pharmaceutical ingredient sourcing.
- Narrow therapeutic index controls.
- Content uniformity across multiple low-dose strengths.
- Stability and packaging controls.
- Regulatory compliance across several tablet strengths.
- Supply continuity during manufacturer exits.
- Pharmacovigilance for bleeding events and medication errors.
Manufacturing know-how can affect cost and reliability, but it is unlikely to support durable pricing power. A generic producer's competitive advantage is more likely to come from dependable supply, broad strength coverage, hospital contracts, and distribution than from blocking intellectual property.
Which companies compete in the warfarin market?
The market is fragmented and jurisdiction-specific. Competition includes generic manufacturers, branded-generic suppliers, hospital distributors, and regional pharmaceutical companies.
Potential suppliers vary by country and can include:
- Viatris and legacy Mylan operations.
- Teva Pharmaceutical Industries.
- Hikma Pharmaceuticals.
- Zydus Lifesciences.
- Sun Pharmaceutical Industries.
- Dr. Reddy's Laboratories.
- Lupin.
- Regional generic manufacturers.
- Contract manufacturers supplying private-label products.
Jantoven remains associated with warfarin sodium tablet supply in the United States. Brand and generic availability can change by dosage strength and distributor.
The absence of a single dominant global supplier creates a low-price market but also raises supply-continuity risk if manufacturers discontinue low-margin strengths.
What litigation and settlement risks affect warfarin?
There is no major active patent-litigation theme around conventional warfarin comparable to litigation involving high-revenue branded anticoagulants. Commercial disputes are more likely to involve:
- Product liability claims concerning bleeding.
- Failure-to-warn allegations.
- Medication-error litigation.
- Manufacturing-quality investigations.
- Antitrust or supply-contract disputes.
- Patent disputes involving new monitoring or delivery technologies.
Settlement agreements are not expected to affect generic warfarin entry because ordinary generic entry has already occurred. Any settlement relating to a future proprietary formulation would be product-specific.
What revenue exposure do pharmaceutical companies have to warfarin?
Warfarin is generally immaterial to the revenue of diversified pharmaceutical companies. It can be strategically important for generic portfolios because it has:
- Low manufacturing complexity.
- Broad clinical recognition.
- Persistent hospital and outpatient demand.
- Multiple available strengths.
- Limited originator patent risk.
Its disadvantages are low gross margins, price competition, monitoring-related clinical friction, and declining use in developed markets.
For investors, warfarin exposure is best assessed through portfolio breadth, supply contracts, and manufacturing reliability. A company with a large generic anticoagulant portfolio may use warfarin to maintain hospital and pharmacy relationships, but warfarin alone is unlikely to drive material earnings growth.
What generic launch scenarios exist for warfarin?
Conventional generic launch risk is already realized. The relevant future scenarios concern substitution and portfolio changes rather than first generic entry.
Base case
Generic warfarin remains widely available. Volume declines in developed markets but remains stable globally. Pricing remains competitive, with modest increases during supply disruptions.
Downside case
DOAC prices fall, reimbursement broadens, and monitoring infrastructure improves. Warfarin use declines faster, particularly in atrial fibrillation and routine VTE treatment.
Upside case
DOAC affordability remains limited in emerging markets. Mechanical-valve procedures increase. Antiphospholipid syndrome and renal-disease use remains durable. Warfarin demand grows modestly in units.
What is the investment outlook for warfarin?
Warfarin is a defensive generic product, not a high-growth pharmaceutical asset. Its value lies in recurring demand, broad manufacturing familiarity, and clinical necessity in selected populations.
The most credible commercial strategy is cost-efficient supply combined with anticoagulation-management services. A standalone branded warfarin relaunch would face weak pricing power unless it offered a clinically meaningful formulation, adherence benefit, or integrated monitoring solution.
Key Takeaways
- The estimated 2025 global warfarin drug market is approximately $0.7 billion-$1.1 billion.
- Base-case global sales are projected at about $0.9 billion in 2025 and $0.92 billion in 2030.
- Developed-market volume should decline as apixaban, rivaroxaban, and other DOACs replace warfarin in eligible patients.
- Mechanical heart valves, selected renal patients, antiphospholipid syndrome, and low-income markets support continued demand.
- Core warfarin patents and originator exclusivity have expired.
- Paragraph IV litigation is not a material risk for conventional generic warfarin.
- Formulation, monitoring, packaging, and digital-dosing patents could create niche opportunities.
- Supply reliability and manufacturing efficiency matter more than patent protection.
- Warfarin is a stable generic revenue product with limited standalone growth potential.
FAQs About Warfarin Market Size, Patents, and Sales
Is warfarin still a commercially important drug?
Yes. Warfarin has low pricing but remains important because it is required or preferred for mechanical heart valves and selected high-risk anticoagulation patients.
Will warfarin sales decline after 2025?
Sales are likely to decline in mature markets, but global revenue should remain broadly stable because emerging-market demand and persistent specialist use offset part of the DOAC substitution.
Does warfarin have biosimilar competition?
No. Warfarin is a chemically synthesized small molecule, so it competes through generic drug approvals rather than the biosimilar pathway.
Can a new warfarin formulation receive patent protection?
Yes. A genuinely novel liquid, extended-release, pediatric, combination, packaging, or drug-device formulation may receive patent protection if it satisfies patentability and regulatory requirements. The active ingredient itself cannot support new composition-of-matter exclusivity.
What is the biggest commercial threat to warfarin?
The biggest threat is continued substitution by DOACs, particularly apixaban and rivaroxaban, in nonvalvular atrial fibrillation and venous thromboembolism patients who do not require INR-guided therapy.
References
-
January, C. T., Wann, L. S., Calkins, H., et al. (2019). 2019 AHA/ACC/HRS focused update of the 2014 guideline for the management of patients with atrial fibrillation. Circulation, 140(6), e285-e292.
-
Stevens, S. M., Woller, S. C., Kreuziger, L. B., et al. (2021). Antithrombotic therapy for VTE disease: Second update of the CHEST guideline and expert panel report. Chest, 160(6), e545-e608.
-
Eikelboom, J. W., Connolly, S. J., Brueckmann, M., et al. (2013). Dabigatran versus warfarin in patients with mechanical heart valves. New England Journal of Medicine, 369(13), 1206-1214.
-
Tektonidou, M. G., Andreoli, L., Limper, M., et al. (2019). EULAR recommendations for the management of antiphospholipid syndrome in adults. Annals of the Rheumatic Diseases, 78(10), 1296-1304.
-
U.S. Food and Drug Administration. (2023). Warfarin sodium tablets prescribing information. FDA.
-
U.S. Food and Drug Administration. (2024). Approved drug products with therapeutic equivalence evaluations: Orange Book. FDA.
-
U.S. Food and Drug Administration. (2024). Drugs@FDA: FDA-approved drugs database. FDA.
More… ↓