Share This Page
Drug Sales Trends for IPRATROPIUM BROMIDE
✉ Email this page to a colleague
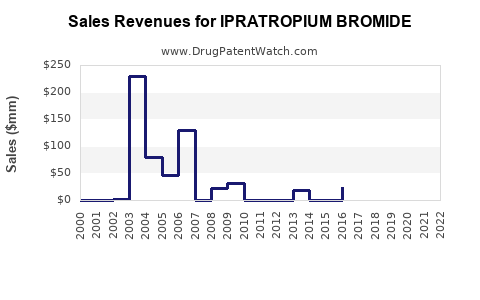
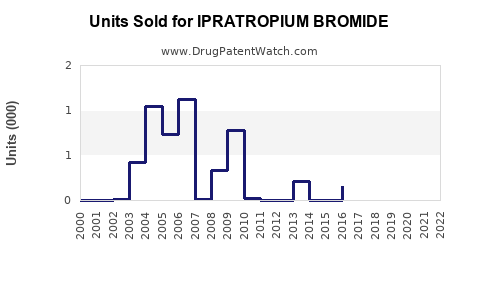
Annual Sales Revenues and Units Sold for IPRATROPIUM BROMIDE
| Drug Name | Revenues (USD) | Units | Year |
|---|---|---|---|
| IPRATROPIUM BROMIDE | ⤷ Start Trial | ⤷ Start Trial | 2022 |
| IPRATROPIUM BROMIDE | ⤷ Start Trial | ⤷ Start Trial | 2021 |
| IPRATROPIUM BROMIDE | ⤷ Start Trial | ⤷ Start Trial | 2020 |
| IPRATROPIUM BROMIDE | ⤷ Start Trial | ⤷ Start Trial | 2019 |
| IPRATROPIUM BROMIDE | ⤷ Start Trial | ⤷ Start Trial | 2018 |
| IPRATROPIUM BROMIDE | ⤷ Start Trial | ⤷ Start Trial | 2017 |
| IPRATROPIUM BROMIDE | ⤷ Start Trial | ⤷ Start Trial | 2016 |
| >Drug Name | >Revenues (USD) | >Units | >Year |
Ipratropium Bromide Market Analysis and Sales Projections, 2024-2029
Ipratropium bromide is a mature, genericized inhaled anticholinergic used mainly for chronic obstructive pulmonary disease (COPD) and acute bronchospasm. The market has limited pricing power, no meaningful small-molecule exclusivity, and substantial substitution from tiotropium, glycopyrrolate, umeclidinium, and fixed-dose inhaled combinations.
The global market for ipratropium-containing products is estimated at approximately $700 million to $1.1 billion in 2024, including standalone inhalers, nebulizer solutions, and combination products such as ipratropium/albuterol. A base-case model projects low single-digit nominal growth through 2029, driven by respiratory-disease prevalence and emerging-market volume, offset by generic price erosion and migration to long-acting maintenance therapies.
What is the current market position of ipratropium bromide?
Ipratropium is a short-acting muscarinic antagonist, or SAMA. It is administered through metered-dose inhalers, nebulizer solutions, and fixed-dose combinations.
The principal commercial uses are:
- COPD maintenance and symptomatic relief
- Acute bronchospasm
- Emergency-department treatment of asthma exacerbations, usually with albuterol
- Hospital and outpatient nebulization
- Pediatric and adult respiratory care in selected markets
Ipratropium has a short duration of action compared with long-acting muscarinic antagonists. Its main commercial value is in low-cost rescue treatment and acute-care protocols rather than premium chronic maintenance therapy.
Major product categories
| Product category | Typical product | Commercial position |
|---|---|---|
| Standalone inhaler | Ipratropium bromide HFA | Mature, genericized |
| Standalone nebulizer | Ipratropium bromide inhalation solution | High-volume institutional and outpatient use |
| Fixed-dose inhaler | Ipratropium/albuterol | Important rescue and COPD segment |
| Fixed-dose nebulizer | Ipratropium/albuterol inhalation solution | Strong hospital and emergency-care use |
| Combination respiratory products | Various regional presentations | Fragmented, country-specific |
Boehringer Ingelheim commercialized Atrovent and Combivent, while generic manufacturers now supply substantial volumes in the United States and international markets. FDA-approved labeling identifies ipratropium products for bronchospasm associated with COPD and, in combination products, for reversible bronchospasm in patients requiring more than one bronchodilator.[1][2]
How large is the ipratropium bromide market?
Public companies generally do not report standalone ipratropium revenue. Revenue is usually bundled into broader respiratory portfolios or disclosed within geographic segments. The following market estimate therefore covers direct product revenue from ipratropium-containing inhalers and nebulizer products rather than a company-reported market total.
Estimated 2024 market by product type
| Segment | Estimated share | Estimated 2024 revenue |
|---|---|---|
| Ipratropium/albuterol combinations | 50%-60% | $350 million-$650 million |
| Standalone nebulizer solution | 20%-30% | $140 million-$300 million |
| Standalone inhaler | 15%-20% | $100 million-$200 million |
| Other regional formulations | 5%-10% | $35 million-$100 million |
| Total direct market | 100% | $700 million-$1.1 billion |
The combination segment is commercially larger because ipratropium is frequently used with albuterol in emergency, hospital, and COPD settings. Standalone ipratropium faces stronger therapeutic substitution from long-acting maintenance products and low-cost generic competition.
Geographic distribution
The United States is likely the largest single national market by revenue because of its large COPD population, extensive nebulizer use, and broad availability of branded and generic combination products. Europe has substantial unit demand but lower prices because of centralized procurement and generic substitution. Latin America, Asia-Pacific, and parts of the Middle East and Africa are more volume-oriented markets, with demand concentrated in low-cost inhalers and nebulizer solutions.
What are the sales projections for ipratropium bromide through 2029?
The base case is a mature market with volume growth offset by price erosion.
Global revenue projection
| Year | Bear case | Base case | Bull case |
|---|---|---|---|
| 2024 | $700 million | $900 million | $1.1 billion |
| 2025 | $680 million | $910 million | $1.13 billion |
| 2026 | $660 million | $920 million | $1.16 billion |
| 2027 | $640 million | $930 million | $1.19 billion |
| 2028 | $620 million | $945 million | $1.22 billion |
| 2029 | $600 million | $960 million | $1.25 billion |
| 2024-2029 CAGR | -3.1% | 1.3% | 2.6% |
These figures represent nominal product revenue. The base case assumes:
- Unit demand growth of approximately 2%-4% annually
- Average selling price erosion of 1%-3% annually
- Continued demand for nebulizer products in hospitals and outpatient settings
- Stable use of ipratropium/albuterol combinations in acute-care protocols
- Gradual substitution toward long-acting muscarinic antagonists
- No major branded relaunch or new delivery technology
The bull case requires stronger emerging-market volume, higher hospital utilization, and slower generic price compression. The bear case assumes accelerated substitution to long-acting inhalers, payer pressure, and further commoditization of nebulizer products.
Which segments will generate the most ipratropium sales?
Ipratropium/albuterol combinations
Combination products should remain the largest revenue segment through 2029. The clinical rationale is straightforward: simultaneous short-acting beta-agonist and anticholinergic bronchodilation is established in acute COPD treatment and is embedded in emergency-care and hospital protocols.[3]
Combivent Respimat and generic equivalents occupy the inhaler segment. DuoNeb and equivalent nebulizer products occupy the institutional and outpatient solution segment. Generic competition limits price growth, but combinations benefit from continued clinical familiarity and reimbursement coverage.
Nebulizer solutions
Nebulizer solutions have stronger volume resilience than standalone inhalers. They are used in hospitals, emergency departments, long-term-care facilities, home care, and among patients who cannot reliably coordinate inhaler actuation and inhalation.
The main risks are:
- Hospital purchasing pressure
- Conversion to albuterol-only protocols
- Increased use of handheld inhalers
- Reimbursement reductions
- Manufacturing interruptions affecting sterile respiratory solutions
Sterile inhalation products can have higher manufacturing barriers than conventional tablets because they require validated aseptic production, container-closure controls, and microbiological quality testing.
Standalone ipratropium inhalers
Standalone inhalers are the weakest growth segment. Short-acting monotherapy is less attractive for chronic maintenance than once-daily or twice-daily long-acting muscarinic antagonists. The segment remains relevant where affordability, acute symptom control, or formulary positioning favors ipratropium.
How does ipratropium compare with competing COPD drugs?
| Drug or class | Duration | Primary role | Commercial threat to ipratropium |
|---|---|---|---|
| Ipratropium | Short acting | Rescue and acute bronchodilation | Reference product |
| Albuterol | Short acting | Rescue bronchodilation | High in monotherapy |
| Tiotropium | Long acting | COPD maintenance | High |
| Glycopyrrolate | Long acting | COPD maintenance | High |
| Umeclidinium | Long acting | COPD maintenance | High |
| LABA/LAMA combinations | Long acting | Maintenance therapy | Very high |
| Inhaled corticosteroid combinations | Long acting | Selected COPD and asthma populations | Moderate |
| Nebulized long-acting bronchodilators | Long acting | Patients requiring nebulization | Increasing |
The principal competitive issue is treatment migration, not direct product replacement. Patients receiving maintenance treatment increasingly use long-acting bronchodilators, while ipratropium remains concentrated in rescue and acute-care use.
Clinical guidelines place short-acting bronchodilators in symptom-relief pathways and recommend long-acting bronchodilators for many patients requiring regular maintenance therapy.[4]
When does ipratropium bromide lose exclusivity?
Ipratropium bromide has lost meaningful composition-of-matter exclusivity in major markets. The drug was introduced decades ago, and current competition is primarily generic and regulatory rather than patent-driven.
U.S. exclusivity profile
| Exclusivity category | Current position |
|---|---|
| New chemical entity exclusivity | Expired |
| Composition-of-matter patent | Expired |
| Orphan-drug exclusivity | Not applicable to the core product |
| Pediatric exclusivity | Not a current commercial barrier |
| Formulation exclusivity | Limited and product-specific |
| Reference-product exclusivity | Expired for legacy products |
| Generic competition | Established |
The commercial protection of any specific inhaler or combination product depends on device, formulation, labeling, manufacturing process, and product-specific FDA listings. The active ingredient itself does not provide a meaningful barrier to generic entry.
What is the Orange Book and Paragraph IV status of ipratropium products?
The FDA Orange Book lists approved drug products and, where applicable, patents and exclusivity associated with reference products.[5] For legacy ipratropium products, the central commercial fact is that approved generic competition already exists. A new Paragraph IV challenge would therefore have limited strategic value unless it targeted a newly approved formulation, device, or combination product with protected commercial share.
Paragraph IV risk is most relevant to:
- New inhaler devices
- Suspension or solution formulations
- Combination products
- Dose-delivery systems
- Patent-protected manufacturing processes
- Product-specific method-of-use claims
A generic applicant can also pursue a Paragraph III certification, a section viii statement, or a standard ANDA pathway depending on the listed patents and proposed labeling. For mature ipratropium products, litigation risk is generally lower than for recently launched respiratory products.
What patents and intellectual-property barriers protect ipratropium products?
The active pharmaceutical ingredient is not the main intellectual-property barrier. Relevant rights, where present, are more likely to concern delivery technology and formulation.
Potentially relevant patent categories
- Metered-dose inhaler valve and actuator systems
- Propellant and suspension chemistry
- Nebulizer container and unit-dose packaging
- Combination-product formulation
- Device dose counters
- Manufacturing and filling processes
- Selected method-of-use claims
Atrovent HFA relied on hydrofluoroalkane propellant technology after the transition away from chlorofluorocarbon inhalers. That transition created historical formulation and device differentiation, but the resulting commercial barriers are no longer equivalent to active composition patents.
The remaining IP risk is product-specific. A market participant should review the current Orange Book entry, FDA approval history, patent certifications, and litigation docket for each branded or generic reference product before making an entry decision.
What is the FDA regulatory status of ipratropium bromide?
Ipratropium is an FDA-approved small-molecule drug. Approved dosage forms include inhalation aerosols and inhalation solutions. Products are regulated through the prescription drug pathway and, for generics, through ANDAs under section 505(j) of the Federal Food, Drug, and Cosmetic Act.
FDA labeling identifies common risks including dry mouth, headache, respiratory irritation, blurred vision, urinary retention, and paradoxical bronchospasm. The labels also warn about use in patients with narrow-angle glaucoma or prostatic hypertrophy.[1][2]
There is no biosimilar pathway for ipratropium. It is a chemically synthesized small molecule, so competition occurs through generic-drug approval rather than 351(k) biosimilar development.
Which companies compete in the ipratropium market?
Competition is fragmented. Relevant participants include:
- Boehringer Ingelheim, through legacy Atrovent and Combivent franchises
- Nephron Pharmaceuticals
- Cipla
- Teva Pharmaceutical Industries
- Viatris and legacy Mylan operations
- Hikma Pharmaceuticals
- Amneal Pharmaceuticals
- Perrigo and regional respiratory manufacturers
- Hospital-focused generic manufacturers
- Country-specific inhalation-product suppliers
Company participation varies by dosage form and geography. A manufacturer may supply the active ingredient or finished product through contract manufacturing without marketing the product under a globally recognized brand.
The strongest commercial positions are likely to come from manufacturers with:
- FDA-approved inhalation facilities
- Reliable sterile-solution capacity
- Metered-dose inhaler manufacturing
- Formulation and device-development capability
- Hospital contracting relationships
- Broad respiratory-product portfolios
What generic launch risks exist for ipratropium bromide?
Generic entry risk is already realized in the principal product categories. The issue for new entrants is commercial sustainability rather than first entry.
Key launch risks
- Price compression: Multiple ANDA holders can reduce reimbursement and pharmacy acquisition prices.
- Device equivalence: Inhalers require reliable dose delivery, patient usability, and regulatory comparability.
- Sterile manufacturing: Nebulizer solutions require controlled aseptic production.
- Contract concentration: Hospitals and group purchasing organizations can favor a small number of suppliers.
- Supply interruptions: A manufacturing problem can create temporary shortages but does not guarantee durable pricing power.
- Combination-product competition: Ipratropium/albuterol products face stronger demand than standalone ipratropium but also attract more competitors.
A new entrant is more likely to achieve acceptable returns through supply reliability, hospital contracting, or a differentiated device than through premium pricing.
What is the commercial outlook and revenue exposure?
Ipratropium is a defensive, low-growth respiratory product with predictable demand but limited strategic upside. Revenue exposure is most attractive for manufacturers that already have respiratory manufacturing infrastructure and can spread fixed costs across albuterol, ipratropium, corticosteroid, and long-acting bronchodilator products.
The strongest investment case is operational:
- High-volume generic supply
- Stable institutional demand
- Portfolio cross-selling
- Capacity utilization for inhalation manufacturing
- Regional expansion in underpenetrated markets
The weakest investment case is a standalone branded relaunch dependent on premium pricing. The market lacks strong exclusivity, and physicians and payers can substitute among short-acting bronchodilator products.
Key Takeaways
- The direct global ipratropium-containing product market is estimated at $700 million-$1.1 billion in 2024.
- A base-case projection reaches approximately $960 million by 2029, representing about 1.3% annual growth.
- Ipratropium/albuterol combinations are the largest commercial segment.
- Nebulizer solutions should have better volume resilience than standalone inhalers.
- Long-acting muscarinic antagonists and LABA/LAMA combinations are the main therapeutic substitutes.
- Core composition and regulatory exclusivity have expired.
- Paragraph IV litigation is unlikely to be a major barrier for established products.
- Manufacturing quality, sterile capacity, device capability, and hospital contracting are more important than active-ingredient patent rights.
- The market is commercially stable but offers limited pricing power and limited innovation-adjusted upside.
FAQs
Is ipratropium bromide still a growing drug market?
The market is mature. Global unit demand can grow with COPD prevalence, but revenue growth is constrained by generic price erosion and substitution toward long-acting maintenance therapies.
Are there ipratropium bromide biosimilars?
No. Ipratropium is a small-molecule drug. Competitors enter through generic-drug approval pathways, not biosimilar applications.
Is ipratropium bromide more profitable as a nebulizer or inhaler product?
Nebulizer products may offer stronger institutional volume, while inhalers can provide better commercial differentiation when supported by device capability. Both segments face generic pricing pressure.
Does Combivent still have patent protection?
The original commercial exclusivity for Combivent has expired. Any remaining protection must be evaluated at the specific product, device, formulation, and Orange Book listing level.
What is the largest risk to future ipratropium sales?
The largest structural risk is gradual migration from short-acting ipratropium products to long-acting muscarinic antagonists and LABA/LAMA maintenance combinations. Acute-care and nebulizer use should limit the rate of decline.
References
-
U.S. Food and Drug Administration. (2023). Atrovent HFA prescribing information. FDA.
-
U.S. Food and Drug Administration. (2023). Ipratropium bromide and albuterol sulfate inhalation solution prescribing information. FDA.
-
Global Initiative for Chronic Obstructive Lung Disease. (2024). Global strategy for the prevention, diagnosis and management of chronic obstructive pulmonary disease: 2024 report. GOLD.
-
National Institute for Health and Care Excellence. (2019, updated 2023). Chronic obstructive pulmonary disease in over 16s: Diagnosis and management. NICE guideline NG115.
-
U.S. Food and Drug Administration. (2024). Approved drug products with therapeutic equivalence evaluations: Orange Book. FDA.
More… ↓
