Share This Page
Drug Sales Trends for entecavir
✉ Email this page to a colleague
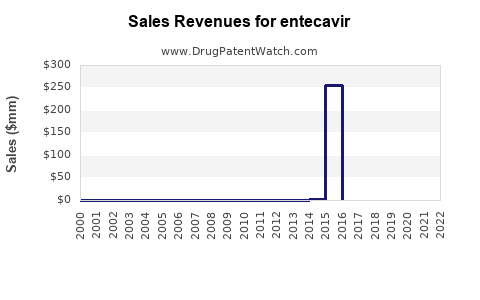
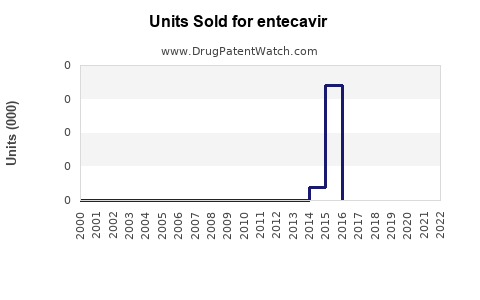
Annual Sales Revenues and Units Sold for entecavir
| Drug Name | Revenues (USD) | Units | Year |
|---|---|---|---|
| ENTECAVIR | ⤷ Start Trial | ⤷ Start Trial | 2022 |
| ENTECAVIR | ⤷ Start Trial | ⤷ Start Trial | 2021 |
| ENTECAVIR | ⤷ Start Trial | ⤷ Start Trial | 2020 |
| ENTECAVIR | ⤷ Start Trial | ⤷ Start Trial | 2019 |
| ENTECAVIR | ⤷ Start Trial | ⤷ Start Trial | 2018 |
| ENTECAVIR | ⤷ Start Trial | ⤷ Start Trial | 2017 |
| >Drug Name | >Revenues (USD) | >Units | >Year |
Entecavir Market Analysis, Sales Forecast, Patent Status, and Competitive Outlook
Entecavir is a mature oral antiviral used for chronic hepatitis B virus infection. The branded product, Baraclude, lost U.S. exclusivity after patent expiry and generic entry. The commercial market is now driven by low-cost generic volume, continued hepatitis B treatment demand in Asia-Pacific, and use in patients for whom tenofovir-based therapy is less suitable. Global annual entecavir sales are estimated at approximately $350 million to $550 million in 2024, with a base-case market of $330 million to $450 million by 2030. Unit demand should remain stable or rise modestly, while average selling prices continue to decline.
What is the current market position of entecavir?
Entecavir is a guanosine nucleoside analogue approved for the treatment of chronic hepatitis B in adults and children at least 2 years old who have evidence of active viral replication and liver disease. The U.S. reference product is Baraclude, originally developed and commercialized by Bristol-Myers Squibb. The FDA approved Baraclude in March 2005. [1]
The drug remains clinically relevant because it has:
- High antiviral potency against hepatitis B virus.
- A generally favorable resistance profile in treatment-naive patients.
- Once-daily oral dosing.
- Generic availability in major markets.
- Established use in patients with renal or bone-related concerns affecting tenofovir selection.
Its commercial limitations are equally clear. Tenofovir disoproxil fumarate, tenofovir alafenamide, and generic competition have reduced entecavir pricing and prescribing share. Entecavir is also less attractive in patients with prior lamivudine exposure because resistance can emerge more readily in that population. [2]
Entecavir market snapshot
| Metric | Current assessment |
|---|---|
| Reference product | Baraclude |
| Active ingredient | Entecavir |
| Main indication | Chronic hepatitis B |
| U.S. approval | 2005 |
| Current U.S. status | Generic-dominated |
| Main dosage forms | 0.5 mg and 1 mg tablets; oral solution |
| Principal demand region | Asia-Pacific |
| Estimated global 2024 sales | $350 million-$550 million |
| Estimated 2030 base-case sales | $330 million-$450 million |
| Market structure | Fragmented generic market |
| Main competitors | TDF, TAF, pegylated interferon, generic entecavir |
The 2024 estimate includes branded and generic product sales across major commercial markets. It is a scenario-based estimate because manufacturers do not report consolidated global entecavir revenue by molecule.
How large is the addressable market for entecavir?
The underlying hepatitis B population is large, but only a subset requires long-term antiviral therapy. The World Health Organization estimates that approximately 254 million people were living with chronic hepatitis B in 2022, with about 1.1 million deaths from hepatitis B-related cirrhosis and liver cancer. [3]
Treatment penetration remains uneven. China, Japan, South Korea, Southeast Asia, the Middle East, and parts of Africa contain the largest pools of potentially treatable patients. Generic entecavir has a stronger commercial position in these markets than in the United States and Western Europe because of:
- High hepatitis B prevalence.
- Long-term treatment requirements.
- Public-sector procurement.
- Lower generic prices.
- Extensive physician familiarity with entecavir.
- Constraints on access to newer branded therapies.
A practical demand model divides the market into three segments:
| Segment | Commercial characteristics | Outlook |
|---|---|---|
| Treatment-naive chronic hepatitis B | Entecavir competes with TDF and TAF | Stable, with gradual share loss |
| Renal or bone-risk patients | Entecavir may be selected over TDF | Defensible niche |
| Lamivudine-exposed patients | Reduced attractiveness because of resistance concerns | Declining share |
Entecavir is not a curative therapy. Patients who achieve viral suppression may remain on treatment for years, creating recurring prescription demand. This supports volume stability even when prices fall.
What are the historical sales and revenue trends for Baraclude?
Baraclude generated peak annual sales of approximately $1 billion or more for Bristol-Myers Squibb before generic erosion. BMS reported Baraclude revenue of roughly $1.1 billion in 2013, followed by declining sales as generic entry approached and occurred. [4]
Historical commercial timeline
| Year | Event | Commercial effect |
|---|---|---|
| 2005 | FDA approval of Baraclude | U.S. commercial launch |
| 2006-2012 | Expansion of chronic hepatitis B treatment | Rapid branded sales growth |
| 2013 | Peak commercial period | Annual sales above $1 billion |
| 2014-2015 | U.S. generic approvals and patent challenges | Pricing pressure begins |
| 2015 onward | Generic substitution expands | Branded revenue contracts sharply |
| 2020-2024 | Mature generic market | Volume remains; price declines continue |
BMS no longer controls the economics of the overall molecule to the extent it did during the branded period. Current value is distributed among generic manufacturers, distributors, public health systems, and regional pharmaceutical companies.
When did entecavir lose exclusivity in the United States?
U.S. market exclusivity ended through a combination of patent expiry, generic approvals, and litigation settlements. The principal composition-of-matter patent associated with entecavir was U.S. Patent No. 5,206,244, assigned to Bristol-Myers Squibb. The patent had an expiration date extended by patent-term adjustment and pediatric exclusivity considerations. Generic entry occurred in the 2014-2015 period. [5]
The principal U.S. commercial effect was the transition from a single branded supplier to multiple ANDA-approved manufacturers. Generic entecavir became available in 0.5 mg and 1 mg tablets, the dominant chronic-treatment strengths.
U.S. exclusivity status
| Protection type | Status |
|---|---|
| New chemical entity exclusivity | Expired |
| Core composition patent | Expired |
| Pediatric exclusivity | Expired |
| Formulation protection | Limited practical relevance after core patent expiry |
| FDA generic pathway | ANDA approvals |
| Current market | Generic competition |
The FDA Orange Book remains the key source for listed patents, exclusivity codes, and reference-product information. [5]
Which companies manufacture or compete with entecavir?
The generic market includes multinational and regional suppliers. Manufacturer participation varies by country and dosage form. Companies that have obtained or marketed entecavir products in major jurisdictions include Teva, Mylan/Viatris, Dr. Reddy’s Laboratories, Aurobindo, Sun Pharma, Cipla, and other regional manufacturers.
The relevant competitor is not only another entecavir tablet. Hepatitis B treatment guidelines position entecavir alongside tenofovir disoproxil fumarate and tenofovir alafenamide. The American Association for the Study of Liver Diseases identifies entecavir, TDF, and TAF as high-potency, low-resistance oral therapies for appropriate patients. [2]
Entecavir versus tenofovir
| Factor | Entecavir | TDF | TAF |
|---|---|---|---|
| Route | Oral | Oral | Oral |
| Generic availability | Broad | Broad | Growing |
| Renal considerations | Dose adjustment required | Greater renal monitoring burden | Lower systemic tenofovir exposure |
| Bone considerations | Generally favorable | More concern | Generally favorable |
| Resistance in treatment-naive patients | Low | Very low | Very low |
| Lamivudine-exposed patients | Less favorable | Usually preferred | Usually preferred |
| Cost position | Low | Low | Higher than older generics in many markets |
| Commercial outlook | Mature, stable niche | High-volume generic competitor | Share growth potential |
TAF is the most important newer competitive threat in markets where reimbursement supports its higher price. TDF remains a powerful low-cost substitute. Entecavir's best defense is not broad clinical superiority; it is physician familiarity, generic affordability, and suitability for selected patients.
What are the projected entecavir sales through 2030?
The base-case forecast assumes modest growth in treated hepatitis B patients, continued generic price erosion, stable use in renal-risk patients, and gradual substitution by TAF and TDF.
Global entecavir sales forecast
| Year | Low case | Base case | High case |
|---|---|---|---|
| 2024 | $350 million | $450 million | $550 million |
| 2025 | $335 million | $440 million | $550 million |
| 2026 | $325 million | $430 million | $545 million |
| 2027 | $315 million | $420 million | $540 million |
| 2028 | $310 million | $410 million | $535 million |
| 2029 | $305 million | $400 million | $530 million |
| 2030 | $300 million | $390 million | $525 million |
These figures represent estimated global product sales, not manufacturer-specific revenue.
Forecast assumptions
The low case assumes accelerated migration to TAF and TDF, aggressive tender pricing, and weaker diagnosis and treatment expansion. The base case assumes stable patient volume with annual price declines of approximately 3% to 5%. The high case assumes continued treatment expansion in Asia-Pacific, slower TAF adoption, and durable entecavir use in renal-risk populations.
The most likely commercial outcome is a declining-value, stable-volume market. The molecule should not be evaluated as a high-growth branded opportunity. It is more relevant as a dependable generic, tender, licensing, or regional manufacturing product.
What patent barriers and manufacturing risks affect entecavir?
Core composition protection no longer creates a meaningful global barrier in most major markets. Commercial barriers are operational rather than patent-based.
Key manufacturing and intellectual-property considerations
- API sourcing and regulatory qualification.
- Bioequivalence for immediate-release tablets and oral solution.
- Stability under hot and humid storage conditions.
- Tablet content uniformity at the low 0.5 mg strength.
- Supply reliability for public tenders.
- Country-specific registration and pharmacovigilance requirements.
- Local manufacturing preferences in China, India, and other emerging markets.
- Competition from established suppliers with lower cost bases.
Manufacturing scale is more important than patent exclusivity. A supplier with a qualified API source, low-cost production, and reliable government-tender access can compete even without differentiated formulation technology.
What is the Paragraph IV and litigation risk for generic entecavir?
The main U.S. Paragraph IV risk occurred before and around generic entry. Generic applicants challenged the remaining Baraclude patent claims, leading to patent litigation and settlement activity involving Bristol-Myers Squibb and ANDA applicants. The commercial result was generic entry in the 2014-2015 period rather than prolonged market protection. [5]
Current Paragraph IV risk is low because the core U.S. patents have expired. A new Paragraph IV event would be more likely to involve:
- A new formulation.
- A pediatric dosage form.
- A fixed-dose combination.
- A modified-release product.
- A method-of-use claim with meaningful commercial scope.
Those opportunities appear limited because chronic hepatitis B treatment is already well served by low-cost immediate-release products.
Are there licensing opportunities for entecavir?
Licensing opportunities are concentrated in regional commercialization, government supply, and manufacturing partnerships rather than proprietary drug discovery.
Potentially attractive structures include:
- In-licensing a registered product for markets where the originator is absent.
- Contract manufacturing for public-sector tenders.
- Regional rights for oral solution or pediatric presentations.
- Supply agreements tied to government hepatitis B programs.
- Authorized generic or private-label distribution.
- API and finished-dose partnerships in Asia, Africa, and Latin America.
A licensee would need to compete on price, registration speed, supply continuity, and local distribution. A conventional exclusive global license would have limited strategic value because generic entry is widespread and the active ingredient has no significant remaining core-patent moat.
How strong is the entecavir patent estate?
The patent estate is weak as a current barrier to conventional tablets. The strongest protection was the original composition patent, which supported the branded monopoly but has expired. Any surviving secondary patents would need to cover a commercially meaningful product and withstand validity and obviousness challenges.
Patent strength assessment
| Category | Strength |
|---|---|
| Core molecule | Low after expiry |
| Standard 0.5 mg and 1 mg tablets | Low |
| Oral solution | Low to moderate, depending on jurisdiction |
| Pediatric formulation | Low to moderate |
| Manufacturing process | Moderate if technically specific, but limited commercial leverage |
| Fixed-dose combination | Potentially moderate |
| Method of treatment | Limited enforcement value for standard prescribing |
| Global protection | Fragmented and largely expired |
The commercial value lies in execution rather than exclusivity.
What generic launch scenarios exist for entecavir?
Three launch scenarios are commercially credible.
Price-led generic entry
A manufacturer enters with standard 0.5 mg and 1 mg tablets, competes through wholesaler discounts, and targets large pharmacy or government channels. This is the lowest-risk strategy but offers limited margins.
Regional tender strategy
A supplier focuses on China, India, Southeast Asia, the Middle East, or Africa. The product competes through local registration, local manufacturing, and public procurement. Volume can be substantial, but tender pricing and payment risk reduce profitability.
Differentiated presentation
A company develops oral solution, pediatric packaging, blister configurations, or a fixed-dose combination. Differentiation may improve access and pricing, but the market is unlikely to support a large premium unless reimbursement or procurement rules favor the product.
What is the FDA regulatory status of entecavir?
The FDA-approved reference product is Baraclude. Generic entecavir products are approved through the abbreviated new drug application pathway and must demonstrate pharmaceutical equivalence and bioequivalence to the reference product. The principal tablet strengths are 0.5 mg and 1 mg. [1, 5]
Entecavir requires dose adjustment in patients with reduced renal function. The FDA label also warns against using entecavir alone in patients with untreated HIV infection because of the potential for HIV resistance. [1]
Key Takeaways
- Entecavir is a mature, generic-dominated hepatitis B product.
- Global 2024 sales are estimated at $350 million to $550 million.
- Base-case 2030 sales are approximately $390 million, with stable volume and falling prices.
- The United States is no longer a branded-growth market.
- Asia-Pacific is the main source of long-term demand.
- TDF and TAF are the most important clinical and commercial competitors.
- Core composition patents and exclusivity have expired in the United States.
- Current value comes from generic scale, tenders, regional licensing, and manufacturing efficiency.
- Entecavir remains defensible in selected patients with renal or bone concerns, but it is less attractive after lamivudine exposure.
- The patent estate provides little protection for standard immediate-release tablets.
FAQs
Is entecavir still commercially attractive after generic entry?
Yes, but primarily as a high-volume, low-margin generic. The best opportunities are in Asia-Pacific, public tenders, regional licensing, and reliable supply rather than premium branded sales.
Can entecavir replace tenofovir in chronic hepatitis B treatment?
It can be used as an alternative in appropriate patients, particularly when renal or bone considerations affect tenofovir selection. It is less suitable after prior lamivudine exposure because of resistance concerns.
Does entecavir have remaining patent protection?
The principal U.S. composition patent has expired. Any remaining secondary protection is unlikely to block conventional generic entecavir tablets on a broad commercial basis.
What is the largest future risk to entecavir revenue?
The largest risk is continued substitution by generic TDF and TAF, combined with government-tender price erosion. TAF is particularly relevant in markets that reimburse newer tenofovir formulations.
Is an entecavir fixed-dose combination commercially viable?
It may be viable in targeted regional markets, but the opportunity is limited by low generic pricing, established single-agent therapy, and the absence of a broad patent barrier.
References
- U.S. Food and Drug Administration. (2021). Baraclude (entecavir) prescribing information.
- Terrault, N. A., Lok, A. S. F., McMahon, B. J., Chang, K. M., Hwang, J. P., Jonas, M. M., Brown, R. S., Bzowej, N. H., & Wong, J. B. (2018). Update on prevention, diagnosis, and treatment of chronic hepatitis B: AASLD 2018 hepatitis B guidance. Hepatology, 67(4), 1560-1599.
- World Health Organization. (2024). Global hepatitis report 2024.
- Bristol-Myers Squibb Company. (2014). Annual report 2013.
- U.S. Food and Drug Administration. (2024). Approved drug products with therapeutic equivalence evaluations: Orange Book.
More… ↓
