Drug Sales Trends for DYAZIDE
Payment Methods and Pharmacy Types for DYAZIDE (2016)
Revenues by Pharmacy Type
Units Sold by Pharmacy Type
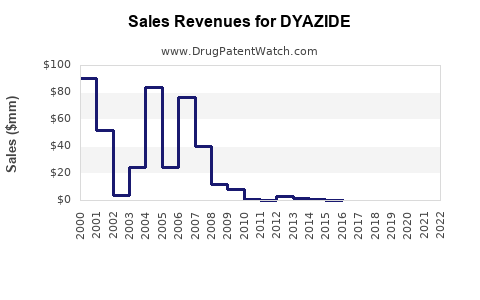
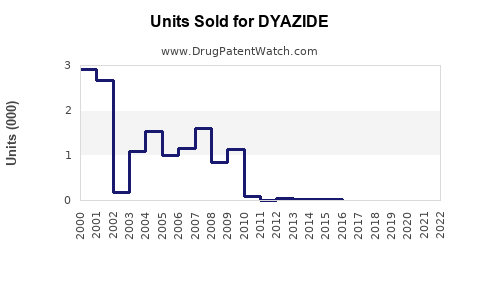
Annual Sales Revenues and Units Sold for DYAZIDE
| Drug Name | Revenues (USD) | Units | Year |
|---|---|---|---|
| DYAZIDE | ⤷ Start Trial | ⤷ Start Trial | 2022 |
| DYAZIDE | ⤷ Start Trial | ⤷ Start Trial | 2021 |
| DYAZIDE | ⤷ Start Trial | ⤷ Start Trial | 2020 |
| >Drug Name | >Revenues (USD) | >Units | >Year |
Dyazide Market Analysis and Sales Projections: Generic Competition, FDA Status, and Revenue Outlook
Dyazide, the branded combination of triamterene and hydrochlorothiazide, is a mature antihypertensive product with negligible brand-sales potential and continuing generic demand. The U.S. market is driven by generic triamterene/hydrochlorothiazide capsules and tablets, not by the Dyazide brand. There is no meaningful remaining patent or regulatory exclusivity barrier to generic supply. A base-case model indicates a relatively stable U.S. molecule market of approximately $45 million to $60 million annually through 2029, with low-single-digit annual erosion from price pressure and therapeutic substitution.
What is Dyazide and how large is its addressable market?
Dyazide combines:
- Triamterene, a potassium-sparing diuretic
- Hydrochlorothiazide, a thiazide diuretic
The product is used for hypertension and edema, particularly when hydrochlorothiazide alone causes clinically significant potassium loss. The principal U.S. strengths are 37.5 mg triamterene/25 mg hydrochlorothiazide and 75 mg triamterene/50 mg hydrochlorothiazide, although availability varies by manufacturer and dosage form.
The commercial market has three layers:
| Market layer | Commercial status | Revenue outlook |
|---|---|---|
| Dyazide branded product | Mature or limited brand presence | Minimal |
| Generic triamterene/HCTZ | Widely available | Stable but price-pressured |
| Competing therapies | HCTZ, chlorthalidone, spironolactone, amiloride and fixed-dose antihypertensives | Structural substitution risk |
The addressable population is narrower than the overall hypertension market. Many patients receive an ACE inhibitor, ARB, calcium-channel blocker or thiazide-like diuretic instead of triamterene/HCTZ. The combination remains useful for patients requiring potassium conservation or a familiar fixed-dose regimen.
What is the FDA regulatory status of Dyazide?
Dyazide was approved by the FDA as a combination prescription drug. The reference product is associated with NDA 018649 in the FDA Drugs@FDA database. FDA labeling identifies the product as a combination of triamterene and hydrochlorothiazide for hypertension and edema indications (U.S. Food and Drug Administration, n.d.-a).
The product has no biologic component and does not create a biosimilar opportunity. Generic manufacturers use the abbreviated new drug application pathway and must demonstrate pharmaceutical equivalence and bioequivalence.
FDA regulatory profile
| Item | Status |
|---|---|
| Active ingredients | Triamterene and hydrochlorothiazide |
| Dosage forms | Capsules and tablets, depending on manufacturer |
| Regulatory pathway for generics | ANDA |
| Biologic status | Not applicable |
| Pediatric exclusivity | No current commercial relevance |
| Orphan-drug exclusivity | None |
| New chemical entity exclusivity | Expired |
| Reference NDA | 018649 |
| Current commercial model | Generic multisource market |
The key regulatory issue is product quality rather than market exclusivity. Manufacturers must control dissolution, content uniformity, impurity levels and stability for the combination product. Triamterene is poorly soluble relative to many conventional antihypertensive ingredients, which can make formulation and bioequivalence work more important than the low retail price suggests.
What patents protect Dyazide and when did exclusivity expire?
No active U.S. patent estate is known to prevent generic entry for triamterene/hydrochlorothiazide. The original product, active ingredients and core combination technology date from the pre-Orange Book era and have long passed ordinary patent terms.
| Protection category | Current commercial impact |
|---|---|
| Active-ingredient patents | Expired |
| Original combination patents | Expired or commercially irrelevant |
| Formulation patents | No known active claim preventing ordinary generic entry |
| Method-of-use patents | No known active patent blocking hypertension or edema use |
| Regulatory exclusivity | Expired |
| Orange Book-listed blocking patents | No meaningful current barrier identified |
The Orange Book remains the controlling source for current listed patents and therapeutic-equivalence information. Historical Dyazide listings should be reviewed against the current FDA edition because discontinued reference products and old patent records may remain visible in historical records without creating a live market barrier (U.S. Food and Drug Administration, n.d.-b).
Are there Paragraph IV challenges involving Dyazide?
Paragraph IV litigation is not a current commercial driver for Dyazide. The product entered the generic market after the relevant patent estate had aged substantially. Generic manufacturers therefore compete primarily on price, supply reliability, wholesaler access and formulary status rather than on patent litigation.
No current, material Paragraph IV dispute is generally associated with the mature triamterene/hydrochlorothiazide market. A new generic entrant would face abbreviated-application requirements, but not the type of patent cliff litigation associated with a recently launched branded drug.
What is the Orange Book status of Dyazide?
The Orange Book classifies therapeutically equivalent generic products through the FDA’s “A” rating system when the products meet applicable equivalence standards. The commercial importance of the Dyazide reference listing is limited because physicians, pharmacies and payers generally substitute generic triamterene/HCTZ.
The market may include multiple approved strengths and manufacturers. The presence of an approved generic does not guarantee uninterrupted supply. Drug shortages, manufacturing changes or product discontinuations can affect individual National Drug Codes even when the molecule remains broadly available.
How strong is the Dyazide patent estate?
The patent estate is commercially weak because it lacks enforceable exclusivity capable of supporting premium pricing or delaying generic competition.
| Patent-strength factor | Assessment |
|---|---|
| Remaining term | None of material commercial value |
| Claim breadth | Historical combination claims are no longer blocking |
| Design-around risk | Low relevance because generic products are already established |
| Litigation leverage | Very low |
| Licensing leverage | Very low |
| Formulation differentiation | Possible at product level, but unlikely to support a durable premium |
| Manufacturing barriers | Moderate technical requirements, low legal barrier |
The strongest residual protection is operational rather than legal. A manufacturer with reliable supply, consistent dissolution performance and strong pharmacy distribution can gain share, but that advantage is vulnerable to price competition.
What companies compete with Dyazide?
The market is fragmented among generic suppliers rather than controlled by a single brand owner. Competition can include large generic manufacturers, contract manufacturers and smaller suppliers with approved triamterene/HCTZ products. The relevant competitor set also includes alternative therapies.
Direct generic competitors
Direct competition comes from manufacturers selling:
- Triamterene/hydrochlorothiazide 37.5 mg/25 mg
- Triamterene/hydrochlorothiazide 75 mg/50 mg
- Capsule and tablet presentations
- Authorized or private-label products distributed through wholesalers and pharmacy chains
Manufacturer participation can change because generic companies periodically discontinue low-margin products. FDA labeling and the Orange Book should be used to confirm current sponsors and marketing status (U.S. Food and Drug Administration, n.d.-b).
Therapeutic competitors
| Competitor | Competitive effect |
|---|---|
| Hydrochlorothiazide monotherapy | Lower-cost substitute, but lacks potassium-sparing component |
| Chlorthalidone | Competes in hypertension; often favored for longer duration |
| Indapamide | Alternative thiazide-like diuretic |
| Spironolactone | Potassium-sparing alternative, particularly in resistant hypertension |
| Amiloride/HCTZ | Closest pharmacologic alternative |
| ACE inhibitor or ARB combinations | Can replace diuretic-based regimens |
| Calcium-channel blockers | Compete for first-line hypertension use |
Clinical guidelines generally emphasize overall cardiovascular-risk reduction and individualized therapy rather than continued use of a specific branded combination. This limits pricing power for Dyazide-related products (Whelton et al., 2018).
What are Dyazide sales and revenue projections?
Public financial filings do not provide a reliable standalone revenue series for Dyazide. The branded product is not reported as a significant revenue line by a major innovator. The figures below are an analytical estimate for the U.S. retail market for triamterene/hydrochlorothiazide products, including generic equivalents. They are not reported Dyazide brand sales.
U.S. sales projection, base case
| Year | Estimated market revenue | Annual change | Market interpretation |
|---|---|---|---|
| 2024 | $55 million | Base year | Mature generic market |
| 2025 | $54 million | -1.8% | Continued price compression |
| 2026 | $53 million | -1.9% | Stable prescription demand |
| 2027 | $51 million | -3.8% | Therapeutic substitution and lower prices |
| 2028 | $50 million | -2.0% | Limited volume growth |
| 2029 | $48 million | -4.0% | Ongoing generic erosion |
The model assumes stable treated prevalence, modest decline in combination-product use, annual generic price erosion of approximately 2% to 4%, and no material supply disruption. Gross manufacturer revenue would be lower than retail-market value after wholesaler, pharmacy and payer discounts.
Scenario analysis
| Scenario | 2029 U.S. market revenue | Key assumptions |
|---|---|---|
| Upside | $65 million | Supply shortages among competitors, stable prescribing, limited price erosion |
| Base | $48 million | Moderate volume decline and recurring generic price reductions |
| Downside | $30 million | Faster migration to chlorthalidone, ARB combinations and other diuretics |
Brand Dyazide revenue would likely remain immaterial under all three scenarios unless a company relaunched the product with a differentiated delivery system, adherence program or specialty distribution strategy. Such a relaunch would face substantial pricing and reimbursement resistance.
What factors will drive future Dyazide demand?
Demand-supporting factors
- Continued hypertension prevalence
- Use in patients who develop hypokalemia on hydrochlorothiazide
- Familiarity among primary-care prescribers
- Low generic acquisition cost
- Fixed-dose convenience
- Periodic shortages of alternative diuretics
Demand-reducing factors
- Preference for chlorthalidone or indapamide in some hypertension guidelines
- Increasing use of ACE inhibitor, ARB and calcium-channel-blocker combinations
- Hyperkalemia concerns in patients with chronic kidney disease or renin-angiotensin-system therapy
- Renal-function monitoring requirements
- Availability of separate-component prescribing
- Generic reimbursement pressure
The safety profile limits use in some populations. Triamterene can increase potassium levels, particularly in renal impairment or when combined with ACE inhibitors, ARBs, potassium supplements or potassium-sparing drugs. Hydrochlorothiazide can contribute to hyponatremia, hyperuricemia, glucose effects and photosensitivity. These risks support monitoring but do not eliminate the product’s role.
What generic launch risks exist for triamterene/hydrochlorothiazide?
A new entrant would face low legal risk but meaningful commercial risk.
| Risk | Impact |
|---|---|
| Low selling price | Limits return on formulation and regulatory investment |
| Crowded supplier base | Makes pharmacy access difficult |
| Contract-manufacturing dependence | Increases supply and quality exposure |
| Small market size | Reduces launch economics |
| Price-based tenders | Compresses margins rapidly |
| Bioequivalence failure | Can delay approval or launch |
| Dissolution variability | Creates product-quality risk |
| Pharmacy substitution | Makes brand-building difficult |
The most viable strategy is a low-cost, reliable generic platform with more than one manufacturing source. A branded relaunch would require a clinically meaningful formulation or adherence advantage, not simply a return to the Dyazide name.
What licensing deals or partnerships affect Dyazide?
No major current licensing transaction is a central driver of the U.S. Dyazide market. Historic commercialization rights may have changed as the original product moved through predecessor companies and generic suppliers, but the mature product does not depend on an active innovation license.
Potential transaction value is more likely to arise from:
- Acquisition of an approved ANDA
- Purchase of a portfolio of low-volume cardiovascular generics
- Contract manufacturing agreements
- Authorized-generic distribution
- Regional supply arrangements
Any valuation should focus on net sales, manufacturing cost, supply continuity, regulatory history and customer concentration. Patent royalties are unlikely to be a material cost.
What is the competitive outlook for Dyazide through 2029?
Dyazide is a harvest-and-defend generic asset, not an exclusivity-driven growth product. Volume should remain sufficiently stable for established suppliers with efficient manufacturing, but revenue growth is unlikely. The principal commercial opportunity is operational: maintain availability, limit quality deviations and secure low-cost distribution.
The market does not support substantial investment in traditional brand promotion. An entrant seeking growth would need to differentiate through a formulation, dosage convenience, packaging, adherence service or channel strategy. Even then, payer substitution would cap pricing.
Key Takeaways
- Dyazide contains triamterene and hydrochlorothiazide and is used for hypertension and edema.
- The U.S. market is primarily generic; branded Dyazide sales are not a significant reported commercial category.
- Core patents and regulatory exclusivity have expired.
- No current Paragraph IV dispute or active patent estate is a material barrier to entry.
- The estimated U.S. triamterene/HCTZ market is approximately $55 million in 2024, declining to about $48 million by 2029 in the base case.
- Generic suppliers compete on price, supply reliability and pharmacy access.
- Chlorthalidone, indapamide, spironolactone, amiloride/HCTZ and ACE inhibitor or ARB combinations create ongoing substitution pressure.
- The main investment risk is low margin, not patent litigation.
- A branded relaunch would require clinically meaningful differentiation to justify development or commercial spending.
FAQs
Is Dyazide still available in the United States?
Triamterene/hydrochlorothiazide remains available through generic products. Availability of the Dyazide-branded product itself may vary by channel and manufacturer.
Is triamterene/HCTZ a profitable generic drug?
It can provide recurring revenue for efficient suppliers, but low prices, multiple competitors and pharmacy substitution limit margins.
Does Dyazide have a biosimilar competitor?
No. Dyazide is a chemically synthesized small-molecule drug, so competitors enter through ANDAs rather than the biosimilar pathway.
Can a company obtain new patent protection for a Dyazide formulation?
A genuinely novel formulation, delivery system or manufacturing process could potentially support new patent claims. A basic repackage of triamterene and hydrochlorothiazide would not create meaningful exclusivity.
What is the largest commercial threat to Dyazide?
The largest threat is therapeutic substitution combined with generic price erosion. Chlorthalidone, indapamide, ACE inhibitor or ARB combinations and other antihypertensive regimens can reduce demand for fixed-dose triamterene/HCTZ.
References
U.S. Food and Drug Administration. (n.d.-a). Drugs@FDA: Dyazide, NDA 018649. https://www.accessdata.fda.gov/scripts/cder/daf/
U.S. Food and Drug Administration. (n.d.-b). Approved drug products with therapeutic equivalence evaluations: Orange Book. https://www.accessdata.fda.gov/scripts/cder/ob/
U.S. Food and Drug Administration. (n.d.-c). DailyMed: Triamterene and hydrochlorothiazide prescribing information. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/
Whelton, P. K., Carey, R. M., Aronow, W. S., Casey, D. E., Collins, K. J., Dennison Himmelfarb, C., DePalma, S. M., Gidding, S., Jamerson, K. A., Jones, D. W., MacLaughlin, E. J., Muntner, P., Ovbiagele, B., Smith, S. C., Spencer, C. C., Stafford, R. S., Taler, S. J., Thomas, R. J., Williams, K. A., Williamson, J. D., & Wright, J. T. (2018). 2017 ACC/AHA/AAPA/ABC/ACPM/ADA/AGS/APhA/ASH/ASPC/NMA/PCNA guideline for the prevention, detection, evaluation, and management of high blood pressure in adults. Hypertension, 71(6), e13-e115. https://doi.org/10.1161/HYP.0000000000000065
More… ↓
