Drug Sales Trends for PHOSLYRA
Payment Methods and Pharmacy Types for PHOSLYRA (2015)
Revenues by Pharmacy Type
Units Sold by Pharmacy Type
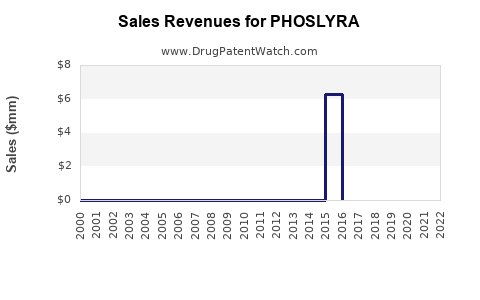
Annual Sales Revenues and Units Sold for PHOSLYRA
| Drug Name | Revenues (USD) | Units | Year |
|---|---|---|---|
| PHOSLYRA | ⤷ Start Trial | ⤷ Start Trial | 2022 |
| PHOSLYRA | ⤷ Start Trial | ⤷ Start Trial | 2021 |
| PHOSLYRA | ⤷ Start Trial | ⤷ Start Trial | 2020 |
| PHOSLYRA | ⤷ Start Trial | ⤷ Start Trial | 2019 |
| >Drug Name | >Revenues (USD) | >Units | >Year |
PHOSLYRA Market Analysis, Sales Projections, Patent Position, and Competitive Outlook
PHOSLYRA is a calcium acetate oral solution used to control serum phosphate in adults with end-stage renal disease undergoing dialysis. Its commercial opportunity is a narrow formulation niche within the much larger phosphate-binder market. The product’s main advantages are liquid administration and reduced tablet burden. Its constraints are low differentiation from generic calcium acetate, calcium-loading concerns, limited public sales disclosure, and competition from sevelamer, iron-based binders, lanthanum, and sucroferric oxyhydroxide.
Standalone PHOSLYRA revenue is not publicly reported. A reasonable U.S. scenario range is approximately $10 million to $75 million in annual net sales, depending on treated patient volume, payer mix, and realized net price. A higher outcome would require substantial penetration among dialysis patients who cannot use or tolerate solid oral binders.
What is PHOSLYRA and how large is its target market?
PHOSLYRA is an oral liquid formulation of calcium acetate. The product is supplied as a 667 mg/5 mL solution, equivalent to approximately 169 mg of elemental calcium per 5 mL. It is administered with meals to bind dietary phosphate in the gastrointestinal tract [1].
The primary target population is adults with chronic kidney disease on dialysis, particularly patients with:
- Dysphagia or difficulty swallowing tablets and capsules
- Enteral feeding requirements
- High tablet burden from multiple chronic medicines
- Poor adherence to solid phosphate binders
- A clinical need for calcium acetate when non-calcium binders are unsuitable
The U.S. dialysis population is approximately 550,000 to 600,000 patients, based on recent United States Renal Data System estimates [2]. A large majority require phosphate-binder therapy, but PHOSLYRA addresses only a fraction of that group because most patients can use tablets, capsules, or chewable products.
Estimated PHOSLYRA addressable market
| Market segment | Estimated U.S. patients | Relevance to PHOSLYRA |
|---|---|---|
| Total dialysis population | 550,000-600,000 | Broad disease population |
| Patients using phosphate binders | 400,000-520,000 | Core treated market |
| Patients with formulation-related adherence issues | 40,000-100,000 | Primary opportunity |
| Patients likely to receive an oral liquid | 5,000-30,000 | Commercially realistic niche |
| High-value institutional or specialty users | 2,000-10,000 | Hospitals, dialysis networks, long-term care |
The commercial market is therefore defined by formulation need rather than by the full phosphate-binder population.
What is the FDA regulatory status of PHOSLYRA?
PHOSLYRA received U.S. approval through NDA 022256. The product’s initial U.S. approval was in 2011. The approved indication is reduction of serum phosphorus in patients with end-stage renal disease on dialysis [1, 3].
The product is an approved small-molecule oral solution, not a biologic. Biosimilar development is therefore irrelevant. Any competing product would generally pursue an abbreviated or full generic-drug pathway depending on the formulation, equivalence requirements, and FDA reference-product designation.
Key regulatory characteristics
| Attribute | PHOSLYRA |
|---|---|
| Active ingredient | Calcium acetate |
| Dosage form | Oral solution |
| Strength | 667 mg/5 mL |
| FDA application | NDA 022256 |
| Initial U.S. approval | 2011 |
| Primary indication | Hyperphosphatemia in dialysis patients |
| Product class | Phosphate binder |
| Biosimilar exposure | None |
| Main regulatory competition | Generic calcium acetate products and alternative phosphate binders |
FDA labeling warns about hypercalcemia, gastrointestinal adverse events, and interactions caused by phosphate binding. The label also requires administration with meals and separation from certain orally administered medicines where clinically appropriate [1].
What patents protect PHOSLYRA and when does it lose exclusivity?
PHOSLYRA’s commercial protection is limited. The active ingredient, calcium acetate, is an established compound with no meaningful composition-of-matter exclusivity. The principal potential protection would arise from the liquid formulation, manufacturing process, or regulatory exclusivity associated with the original NDA.
Public FDA records do not indicate a durable, high-value patent barrier comparable to those protecting innovative specialty drugs. PHOSLYRA has been marketed since 2011, placing the product well beyond the ordinary five-year new-chemical-entity exclusivity period. Any remaining protection would need to come from specific formulation or process patents, not from the active ingredient.
Patent and exclusivity assessment
| Protection category | PHOSLYRA position |
|---|---|
| Composition-of-matter patent | Not commercially relevant for calcium acetate |
| New chemical entity exclusivity | Expired |
| Orphan-drug exclusivity | Not a principal protection |
| Pediatric exclusivity | No material current effect identified |
| Formulation patents | Potentially relevant but not clearly a durable market barrier |
| Method-of-use patents | Limited value because phosphate binding is an established use |
| Regulatory exclusivity | Original exclusivity period has expired |
| Generic substitution risk | High |
The practical loss-of-exclusivity event occurred years ago. The key commercial question is not when PHOSLYRA loses exclusivity, but whether the liquid formulation retains enough clinical and distribution value to support a premium over generic calcium acetate.
How strong is the PHOSLYRA patent estate?
The patent estate appears weak to moderate from a commercial perspective.
Calcium acetate is a long-established active ingredient. A challenger does not need to reproduce a complex biologic process or develop a difficult delivery device. The principal technical challenge is matching the liquid product’s quality attributes, including concentration, stability, uniformity, taste, microbiological control, packaging, and dosing accuracy.
A generic manufacturer could still encounter formulation-development costs, FDA review requirements, and limited market economics. Those barriers may delay entry without creating durable exclusivity.
Technical barriers to generic PHOSLYRA
- Demonstrating pharmaceutical equivalence for an oral liquid
- Controlling calcium acetate concentration during shelf life
- Managing precipitation or crystallization
- Establishing container-closure compatibility
- Validating microbial limits and preservative performance, if applicable
- Reproducing or improving palatability
- Supporting accurate dosing across household and clinical measuring devices
- Meeting supply requirements for dialysis-provider networks
These are manufacturing and regulatory execution risks, not high barriers to scientific replication.
Are there Paragraph IV challenges or PHOSLYRA patent lawsuits?
No major, widely reported Paragraph IV litigation campaign has established PHOSLYRA as a contested patent asset. The absence of prominent litigation is consistent with an older product whose principal ingredient is generic and whose formulation value is limited.
A Paragraph IV filing would become commercially relevant only if an active, Orange Book-listed patent covered the specific oral-solution formulation. Generic calcium acetate capsules and tablets would not necessarily need to challenge every liquid-formulation claim because they may compete through a different dosage form.
Litigation outlook
| Issue | Assessment |
|---|---|
| Historic patent litigation | No major widely reported dispute identified |
| Paragraph IV risk | Possible but not the central market issue |
| Settlement exposure | No major public settlement defining market entry identified |
| Injunction risk | Low relative to innovative branded drugs |
| Main competitive threat | Non-infringing generic calcium acetate and alternative binders |
| Litigation value | Limited unless a liquid-specific patent is enforceable |
What is the PHOSLYRA competitive landscape?
PHOSLYRA competes in two markets: calcium acetate products and the broader phosphate-binder category.
Direct calcium acetate competitors
The closest competitors are generic calcium acetate capsules and tablets, along with calcium acetate products historically marketed under brands such as PhosLo. These products generally have lower cost and broader pharmacy availability.
PHOSLYRA’s differentiation is administration format. It does not offer a new phosphate-binding mechanism.
Broader phosphate-binder competitors
| Product | Active ingredient | Main commercial advantage | Main limitation |
|---|---|---|---|
| PHOSLYRA | Calcium acetate | Liquid dosing; lower pill burden | Calcium loading; niche use |
| Generic calcium acetate | Calcium acetate | Low cost; broad availability | Solid dosage form |
| Renvela and generics | Sevelamer carbonate | Non-calcium binder; strong clinical familiarity | High pill burden; gastrointestinal effects |
| Velphoro | Sucroferric oxyhydroxide | Lower pill burden; non-calcium mechanism | Brand pricing; taste and tolerability issues |
| Auryxia | Ferric citrate | Phosphate reduction and iron delivery | Iron-related monitoring and adverse effects |
| Fosrenol and generics | Lanthanum carbonate | Non-calcium binder; chewable option | Cost and gastrointestinal tolerability |
PHOSLYRA is most competitive when a patient cannot reliably swallow tablets, requires liquid medication, or receives care in an institutional setting where administration convenience has value.
What are the PHOSLYRA sales projections?
Because the manufacturer does not publicly report PHOSLYRA revenue as a separate line item, projections must be based on patient count and realized net revenue per treated patient.
U.S. scenario model
| Scenario | Treated patients | Annual net revenue per patient | Estimated annual sales |
|---|---|---|---|
| Low | 5,000 | $1,000 | $5 million |
| Base | 15,000 | $2,000 | $30 million |
| High | 30,000 | $2,500 | $75 million |
| Upside institutional | 50,000 | $3,000 | $150 million |
The base case is approximately $30 million in annual U.S. net sales. This assumes that PHOSLYRA remains concentrated in patients with swallowing, feeding-tube, adherence, or institutional administration needs.
A more conservative commercial model, using a lower net price and limited specialty distribution, produces annual sales of $10 million to $20 million. A $100 million-plus outcome would require broad formulary placement, strong dialysis-network contracting, or a significant increase in liquid-binder adoption.
Five-year projection
| Year | Low case | Base case | High case |
|---|---|---|---|
| Year 1 | $6 million | $25 million | $55 million |
| Year 2 | $7 million | $28 million | $65 million |
| Year 3 | $8 million | $30 million | $75 million |
| Year 4 | $9 million | $32 million | $85 million |
| Year 5 | $10 million | $35 million | $95 million |
The model assumes modest patient growth, stable reimbursement, and no major loss of distribution. Generic price pressure would reduce net revenue per patient, while broader coverage for patients unable to swallow solid dosage forms would increase treated volume.
What drives PHOSLYRA revenue growth?
The strongest revenue drivers are:
- Increased identification of dialysis patients with dysphagia or enteral feeding needs.
- Adoption by dialysis organizations and long-term-care facilities.
- Improved access through specialty pharmacies.
- Payer recognition of liquid administration as a medically necessary alternative.
- Reduced dependence on compounded or extemporaneous calcium acetate liquids.
- Prescriber preference for a standardized FDA-approved oral solution.
The main revenue constraints are generic substitution, formulary restrictions, calcium-related safety concerns, and the availability of lower-cost tablets and capsules.
What licensing deals and commercial partnerships affect PHOSLYRA?
No major publicly reported licensing transaction has established a separate valuation benchmark for PHOSLYRA. Its commercial performance is more likely to depend on distribution agreements, dialysis-provider contracting, specialty-pharmacy access, and manufacturer supply capacity than on a traditional technology license.
Dialysis operators can influence product uptake through formulary decisions and clinical protocols. A contract with a large dialysis network could materially increase volume but would likely pressure net pricing.
What generic launch risks exist for PHOSLYRA?
Generic entry risk is high in principle but may be commercially limited by the small size of the liquid market.
A generic competitor could enter through:
- An equivalent calcium acetate oral solution
- A different concentration with an approved labeling strategy
- A liquid calcium acetate product marketed to institutional providers
- A lower-cost product distributed through dialysis networks
The first generic entrant would face a niche market with limited volume but could capture substantial share if it achieves a 20% to 40% price discount. PHOSLYRA could preserve share through supply reliability, established prescribing, patient-support services, and contracts with dialysis organizations.
How does PHOSLYRA compare with competing phosphate binders?
PHOSLYRA has a strong administration advantage but a weak mechanism-of-action advantage.
| Factor | PHOSLYRA position |
|---|---|
| Patient convenience | Strong for patients unable to swallow solids |
| Pill burden | Strong relative to tablets, depending on dose volume |
| Calcium safety | Weaker than non-calcium binders |
| Price competitiveness | Strong against branded binders; weaker against generic calcium acetate |
| Clinical differentiation | Limited |
| Patent protection | Weak |
| Generic vulnerability | High |
| Dialysis-network fit | Potentially strong |
| Specialty-pharmacy fit | Moderate to strong |
| Global expansion potential | Limited by reimbursement and liquid-drug logistics |
The product is best viewed as a formulation-driven specialty product, not as a protected branded pharmaceutical with broad market expansion potential.
Key Takeaways
- PHOSLYRA is an FDA-approved calcium acetate oral solution for dialysis patients with hyperphosphatemia.
- Its commercial value comes from liquid administration, not novel pharmacology.
- The product has no meaningful active-ingredient exclusivity and appears to have limited durable patent protection.
- Generic calcium acetate and non-calcium phosphate binders create substantial competitive pressure.
- Standalone sales are not publicly disclosed.
- A reasonable U.S. base-case projection is about $25 million to $35 million in annual net sales.
- A realistic broad range is approximately $10 million to $75 million, with upside above $100 million requiring major institutional or dialysis-network adoption.
- Biosimilar risk does not apply because PHOSLYRA is a small-molecule oral solution.
- The largest commercial opportunity is among patients with dysphagia, feeding tubes, high tablet burden, or institutional medication-administration needs.
FAQs
Is PHOSLYRA the same as calcium acetate?
PHOSLYRA contains calcium acetate but is supplied as an oral liquid. Generic calcium acetate is more commonly supplied as capsules or tablets.
Is PHOSLYRA still commercially protected?
Its original new-drug exclusivity has expired. Any remaining protection would depend on specific formulation or process rights rather than calcium acetate itself.
Can generic manufacturers make a liquid version of PHOSLYRA?
Yes. A manufacturer could develop an equivalent calcium acetate oral solution and seek FDA approval, subject to applicable pharmaceutical-equivalence and bioequivalence requirements.
Does PHOSLYRA have a biosimilar competitor?
No. Biosimilar regulation applies to biologic products. PHOSLYRA is a small-molecule drug.
Who is the best patient for PHOSLYRA?
The strongest target is a dialysis patient who cannot swallow solid dosage forms, uses enteral feeding, has substantial pill burden, or needs a standardized liquid phosphate binder.
References
- U.S. Food and Drug Administration. (2023). PHOSLYRA (calcium acetate) oral solution prescribing information. FDA.
- United States Renal Data System. (2023). 2023 USRDS annual data report: Epidemiology of kidney disease in the United States. National Institute of Diabetes and Digestive and Kidney Diseases.
- U.S. Food and Drug Administration. (n.d.). Drugs@FDA: PHOSLYRA, NDA 022256. FDA.
More… ↓
