Share This Page
Drug Sales Trends for AUVI-Q
✉ Email this page to a colleague
Payment Methods and Pharmacy Types for AUVI-Q (2013)
Revenues by Pharmacy Type
Units Sold by Pharmacy Type
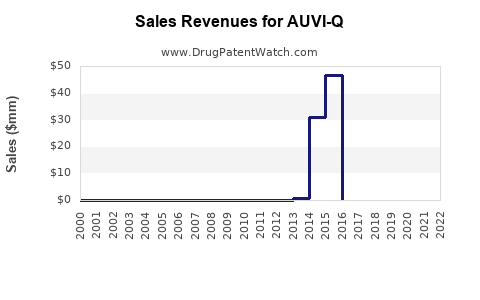
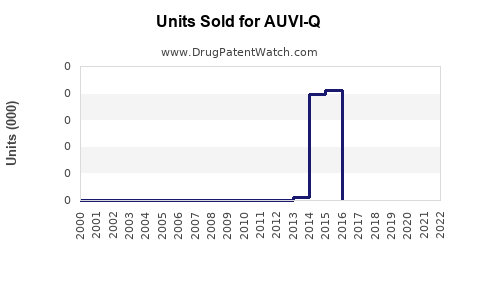
Annual Sales Revenues and Units Sold for AUVI-Q
| Drug Name | Revenues (USD) | Units | Year |
|---|---|---|---|
| AUVI-Q | ⤷ Start Trial | ⤷ Start Trial | 2022 |
| AUVI-Q | ⤷ Start Trial | ⤷ Start Trial | 2021 |
| AUVI-Q | ⤷ Start Trial | ⤷ Start Trial | 2020 |
| AUVI-Q | ⤷ Start Trial | ⤷ Start Trial | 2019 |
| AUVI-Q | ⤷ Start Trial | ⤷ Start Trial | 2018 |
| >Drug Name | >Revenues (USD) | >Units | >Year |
AUVI-Q Market Analysis and Sales Projections
AUVI-Q is a differentiated epinephrine auto-injector marketed by Kaléo for emergency treatment of anaphylaxis. Its commercial position depends on device usability, pediatric dosing, payer access, and competition from EpiPen, authorized generics, Symjepi, and the newer epinephrine nasal spray neffy. AUVI-Q has a defensible delivery-device franchise, but its premium pricing and limited public financial disclosure constrain visibility into product-level profitability.
The base-case outlook is modest U.S. revenue growth through 2028, driven by pediatric demand, device replacement, institutional prescribing, and market expansion from patients who remain undertreated. A reasonable scenario range is approximately $170 million to $320 million in annual U.S. AUVI-Q revenue by 2028, based on modeled net sales rather than reported company guidance.
What is AUVI-Q and how does it compete?
AUVI-Q contains epinephrine and is approved for the emergency treatment of severe allergic reactions, including anaphylaxis. The product provides audio and visual instructions, a compact form factor, automatic needle retraction, and a 0.1 mg pediatric dose for infants and young children weighing approximately 7.5 kg to 15 kg. The 0.15 mg and 0.3 mg strengths address larger pediatric and adult patients, respectively. [1]
AUVI-Q product profile
| Attribute | AUVI-Q |
|---|---|
| Active ingredient | Epinephrine |
| Dosage form | Single-use prefilled auto-injector |
| U.S. sponsor | Kaléo, Inc. |
| Original FDA approval | 2012 |
| NDA | 201739 |
| Key strengths | 0.1 mg, 0.15 mg, 0.3 mg |
| Primary indication | Emergency treatment of anaphylaxis |
| Prescription status | Prescription-only |
| Primary market | United States |
| Principal differentiation | Voice guidance, compact design, needle shielding, 0.1 mg pediatric dose |
AUVI-Q competes in a market where clinical efficacy is broadly similar across products because all deliver epinephrine. Commercial differentiation therefore depends on ease of use, training, insurance coverage, availability, shelf life, replacement behavior, and procurement contracts.
How large is the U.S. epinephrine auto-injector market?
The U.S. market is large but difficult to measure because prescriptions include two-pack configurations, school and emergency-stock programs, Medicaid purchases, cash transactions, and replacement devices. Food allergy prevalence, insect-sting allergy, medication allergy, and idiopathic anaphylaxis create recurring demand.
The market has four main segments:
- Household prescriptions for patients with diagnosed allergy.
- Pediatric prescriptions, often requiring two devices at home and two at school.
- Institutional stock programs for schools, restaurants, workplaces, and public venues.
- Replacement demand caused by expiration, loss, temperature exposure, or use during an emergency.
The patient base is structurally recurring. Epinephrine auto-injectors generally have labeled expiration periods of about 18 months, creating a replacement cycle that is shorter than many chronic medicines. Device demand can therefore grow even when the diagnosed patient population is stable.
Market drivers
| Driver | Effect on AUVI-Q |
|---|---|
| Rising food-allergy diagnosis | Expands the treated population |
| School stocking laws and policies | Increases institutional demand |
| Pediatric 0.1 mg availability | Supports infant and toddler use |
| Two-device prescribing | Increases units per patient |
| Product recalls or shortages | Can shift prescriptions between brands |
| High out-of-pocket cost | Limits conversion and refill persistence |
| Generic EpiPen availability | Creates price pressure |
| Neffy nasal epinephrine | Adds a non-injectable alternative |
Public sources do not provide a separately audited AUVI-Q market share or product revenue figure. Kaléo is privately held and does not publish the level of segment reporting available from large public pharmaceutical companies.
What are AUVI-Q sales and revenue projections?
AUVI-Q revenue should be modeled using prescriptions, devices per prescription, realized net price, and payer mix. The following projection is an analyst scenario, not company guidance.
Base-case AUVI-Q U.S. projection
| Year | Estimated devices sold | Estimated net revenue per device | Estimated net sales |
|---|---|---|---|
| 2024 | 650,000 | $235 | $153 million |
| 2025 | 715,000 | $240 | $172 million |
| 2026 | 790,000 | $245 | $194 million |
| 2027 | 870,000 | $250 | $218 million |
| 2028 | 955,000 | $255 | $244 million |
This base case assumes approximately 10% annual unit growth through 2028 and low-single-digit net price growth. It also assumes that AUVI-Q retains a premium position while expanding access through insurance coverage, copay assistance, and institutional programs.
AUVI-Q revenue scenarios
| Scenario | 2028 devices | Net revenue per device | 2028 net sales |
|---|---|---|---|
| Downside | 600,000 | $225 | $135 million |
| Base case | 955,000 | $255 | $244 million |
| Upside | 1,200,000 | $265 | $318 million |
The downside scenario reflects sustained generic substitution, limited reimbursement, and meaningful uptake of neffy. The upside scenario requires strong pediatric adoption, wider institutional stocking, improved payer access, and limited disruption from competing delivery formats.
What could increase AUVI-Q revenue?
AUVI-Q has several sources of potential revenue expansion:
- Increased prescribing of two devices per patient.
- Greater use in schools and public-access programs.
- Adoption of the 0.1 mg dose in younger children.
- Conversion from conventional EpiPen-style devices based on usability.
- Refill programs tied to expiration reminders.
- Better commercial coverage in Medicaid and employer-sponsored plans.
- Use in patients who have delayed or avoided carrying injectable epinephrine.
The strongest near-term opportunity is likely replacement and adherence rather than a large increase in first-time diagnosis. Patients and caregivers often carry multiple devices, which increases annual unit demand but also raises affordability concerns.
How does AUVI-Q compare with EpiPen, generic epinephrine, Symjepi, and neffy?
Competitive comparison
| Product | Manufacturer or sponsor | Delivery format | Competitive position |
|---|---|---|---|
| AUVI-Q | Kaléo | Voice-guided auto-injector | Premium usability and pediatric positioning |
| EpiPen | Viatris | Conventional auto-injector | Established brand recognition |
| Authorized or generic EpiPen products | Multiple suppliers | Conventional auto-injector | Lower-price alternative |
| Symjepi | Adamis/South Lake | Prefilled syringe device | Compact format, limited commercial scale |
| neffy | ARS Pharmaceuticals | Nasal spray | Needle-free alternative, regulatory entrant |
EpiPen has the deepest historical brand recognition and broadest prescriber familiarity. Generic epinephrine auto-injectors compete primarily on price and formulary placement. AUVI-Q competes by offering a different user experience rather than a different pharmacologic mechanism.
Neffy introduces the first major delivery-format challenge to auto-injectors. FDA approved neffy in August 2024 for emergency treatment of allergic reactions, including anaphylaxis, in adults and children who weigh at least 30 kg. [2] The product is less directly competitive with AUVI-Q’s 0.1 mg pediatric segment because the initial approval did not cover the smallest children. Its commercial impact depends on patient confidence, repeat dosing requirements, nasal absorption in real-world emergencies, payer coverage, and clinician willingness to move away from injectable epinephrine.
How does AUVI-Q compare with generic epinephrine?
Generic products have a structural cost advantage because they do not need to support the same level of branded device differentiation. AUVI-Q can maintain pricing power only if payers and caregivers value its instructions, size, needle protection, and pediatric dosing.
The most exposed segment is price-sensitive adult prescribing where a conventional generic auto-injector is clinically acceptable. The most defensible segments are young children, caregivers with concerns about needle use, schools, and patients who benefit from guided instructions.
What FDA regulatory status and Orange Book information apply to AUVI-Q?
AUVI-Q is approved under FDA NDA 201739. FDA labeling identifies epinephrine auto-injection for emergency allergic reactions and includes the 0.1 mg, 0.15 mg, and 0.3 mg dosage strengths. [1]
The Orange Book is the relevant FDA source for approved-product information, therapeutic equivalence, and listed patent or exclusivity information. [3] AUVI-Q is a drug-device combination product, so commercial protection may arise from a combination of drug approval rights, device patents, manufacturing know-how, trademarks, human-factors design, and regulatory barriers.
Regulatory factors affecting competition
- ANDA applicants must demonstrate pharmaceutical equivalence and bioequivalence or satisfy applicable FDA requirements for the device combination.
- Device usability and human-factors validation can increase development complexity.
- A competing product may match epinephrine delivery while avoiding AUVI-Q’s specific mechanical and software design.
- The 0.1 mg strength gives AUVI-Q a regulatory and commercial position in younger pediatric patients.
- Neffy competes through a different delivery route and does not require an auto-injector device.
What patents protect AUVI-Q?
AUVI-Q protection is primarily associated with its auto-injector architecture, electronic guidance, needle shielding, dose delivery, packaging, and related device functionality. Public patent records should be reviewed together with the FDA Orange Book, USPTO Patent Center, and litigation filings because patent scope and expiry can differ by jurisdiction and patent family.
Patent-estate assessment
| Protection category | Relevance to AUVI-Q | Strength assessment |
|---|---|---|
| Auto-injector mechanics | Protects dose delivery and actuation structures | Moderate to strong, depending on claim scope |
| Electronic voice guidance | Protects user instructions and device control | Moderate |
| Needle shielding and retraction | Supports safety differentiation | Moderate |
| Pediatric 0.1 mg presentation | Creates commercial differentiation | Limited as a standalone patent barrier |
| Cartridge and packaging design | Can complicate design-around efforts | Moderate |
| Manufacturing process and assembly | May create know-how barriers | Moderate |
| Trademark and trade dress | Supports brand recognition | Commercially useful, not a generic barrier |
The practical patent strength is lower than the theoretical number of patents because competitors may design around individual claims. AUVI-Q’s strongest barrier is likely the combined product system: device engineering, human-factors data, regulatory documentation, manufacturing capability, and commercial recognition.
When does AUVI-Q lose exclusivity?
AUVI-Q does not have a single exclusivity date that determines all generic entry. FDA regulatory exclusivity, patent protection, device design protection, and commercial know-how expire or weaken on different timelines.
The original product approval dates to 2012, so the standard five-year new chemical entity exclusivity period would not be the current barrier. The active commercial question is whether listed patents or later-added protections remain enforceable and whether a competing product can obtain FDA approval without infringing them.
No single public date should be treated as the definitive end of AUVI-Q exclusivity without a current Orange Book and patent-family review. Generic or competing-device entry can occur before every patent expires if an applicant certifies non-infringement, invalidity, or non-applicability and prevails against litigation risk.
Generic launch scenarios
| Scenario | Likely timing logic | Commercial effect |
|---|---|---|
| Design-around auto-injector | Requires FDA approval and distinct device architecture | Moderate pressure |
| Direct patent challenge | May trigger Hatch-Waxman litigation | Potential 30-month delay under applicable conditions |
| Generic conventional epinephrine | Competes mainly on price | High pressure in commoditized segments |
| Nasal epinephrine substitution | Depends on clinical adoption and payer coverage | Selective pressure |
| Institutional procurement shift | Driven by contract pricing | Potentially rapid volume loss |
Which companies are challenging AUVI-Q?
Publicly visible competition is broader than a single named Paragraph IV challenger. The relevant competitive set includes Viatris and suppliers of EpiPen-equivalent products, manufacturers of generic epinephrine auto-injectors, Adamis/South Lake with Symjepi, and ARS Pharmaceuticals with neffy.
A confirmed Paragraph IV challenge should be established from FDA Paragraph IV records, district-court complaints, or settlement filings. Generic competition alone does not prove that a specific company has filed a Paragraph IV certification against AUVI-Q.
What patent litigation affects AUVI-Q?
The principal litigation risk is a potential ANDA dispute involving a competing epinephrine auto-injector or a challenge to device-related patents. Such litigation could involve:
- Patent validity.
- Claim construction for mechanical components.
- Electronic instruction systems.
- Needle-shielding mechanisms.
- Drug-device combination claims.
- Orange Book listing accuracy.
- Settlement terms and launch dates.
A current case-by-case litigation conclusion requires live court-docket and Orange Book data. No definitive active AUVI-Q Paragraph IV case should be assumed solely from the existence of generic epinephrine products.
Are biosimilars a risk to AUVI-Q?
No. AUVI-Q contains epinephrine, a small-molecule active ingredient, and is not a biologic. Biosimilar competition under the Public Health Service Act is therefore not the relevant pathway.
The applicable risks are abbreviated new drug applications, 505(b)(2) applications, competing drug-device combinations, and alternative delivery systems such as nasal epinephrine.
What licensing deals and manufacturing barriers matter?
AUVI-Q’s commercial value depends on Kaléo’s ability to manufacture, assemble, package, and distribute a reliable drug-device product at scale. Device products have more operational failure points than conventional tablets, including cartridge filling, assembly tolerances, activation force, electronic components, labeling, packaging, and supply-chain quality controls.
Licensing and partnership arrangements may affect:
- Contract manufacturing capacity.
- International commercialization.
- School and institutional distribution.
- Payer access and copay support.
- Device technology rights.
- Supply continuity during recalls or shortages.
Kaléo’s private ownership limits visibility into current licensing economics and product-level gross margin. There is no basis for assigning material royalty expense or milestone obligations without a disclosed agreement.
What is the geographic coverage of AUVI-Q?
AUVI-Q’s principal commercial opportunity is the United States. The product’s regulatory, reimbursement, and competitive position is country-specific. A U.S. approval does not create automatic coverage in Europe, Canada, Japan, or other markets.
International expansion would require local regulatory approvals, pharmacovigilance infrastructure, manufacturing validation, reimbursement negotiations, and country-specific device labeling. The U.S. market should therefore remain the central basis for valuation unless Kaléo discloses a broader commercialization strategy.
How strong is the AUVI-Q patent estate?
AUVI-Q has a commercially meaningful but not unassailable patent position. Its defensibility is stronger at the system level than at the level of individual mechanical features.
The estate is strongest where patents are combined with:
- Proprietary device integration.
- Human-factors evidence.
- A pediatric 0.1 mg presentation.
- Manufacturing know-how.
- Brand familiarity.
- Institutional contracts.
- Switching friction among caregivers and schools.
The estate is weaker against a product that uses a materially different delivery mechanism, such as a nasal spray, or a conventional generic that avoids AUVI-Q’s distinctive features.
Key Takeaways
- AUVI-Q is a differentiated epinephrine auto-injector, not a differentiated drug molecule.
- Its main commercial advantages are voice guidance, compact design, needle shielding, and the 0.1 mg pediatric strength.
- Generic EpiPen-equivalent products create the greatest price pressure.
- Neffy is the most important new-format competitor following FDA approval in 2024.
- Kaléo does not publicly report audited AUVI-Q product revenue, so projections require scenario modeling.
- A base-case model produces approximately $244 million in U.S. net sales by 2028.
- The downside case is approximately $135 million, while an upside case reaches about $318 million.
- AUVI-Q has no biosimilar risk because epinephrine is a small-molecule drug.
- Patent protection is relevant but should be assessed with current Orange Book, USPTO, and litigation records.
- The primary investment risks are price erosion, payer exclusion, competing delivery formats, manufacturing interruptions, and uncertain private-company disclosure.
FAQs
Is AUVI-Q more expensive than EpiPen?
AUVI-Q has historically occupied a premium positioning relative to generic epinephrine auto-injectors. The effective patient cost depends on insurance coverage, copay assistance, pharmacy contracting, and whether the prescription is filled as a branded or generic product.
Does AUVI-Q have a generic equivalent?
Conventional generic epinephrine auto-injectors compete with AUVI-Q, but a generic product with the same user interface and device architecture would face separate regulatory and patent considerations. Generic competition does not necessarily replicate AUVI-Q’s voice-guided design or 0.1 mg presentation.
Is AUVI-Q still available after the EpiPen shortage period?
AUVI-Q is marketed as a separate product from EpiPen. Availability depends on manufacturer supply, pharmacy inventory, wholesaler allocation, and regional demand. FDA shortage data should be checked for current market conditions.
Can schools stock AUVI-Q without a student-specific prescription?
State laws and institutional policies govern stock epinephrine programs. Some jurisdictions permit schools to maintain emergency epinephrine under standing orders or similar mechanisms. Requirements vary by state and institution.
What is the main long-term threat to AUVI-Q sales?
The main long-term threat is substitution by lower-cost generic auto-injectors and alternative delivery systems, especially nasal epinephrine. AUVI-Q can limit the impact through pediatric dosing, usability differentiation, payer access, and institutional contracts.
References
-
U.S. Food and Drug Administration. (2024). AUVI-Q prescribing information and NDA 201739. FDA Drugs@FDA.
-
U.S. Food and Drug Administration. (2024, August 9). FDA approves first epinephrine nasal spray for emergency treatment of allergic reactions, including anaphylaxis. https://www.fda.gov/
-
U.S. Food and Drug Administration. (2024). Approved drug products with therapeutic equivalence evaluations: Orange Book. https://www.fda.gov/drugs/drug-approvals-and-databases/approved-drug-products-therapeutic-equivalence-evaluations-orange-book
More… ↓
