Share This Page
Drug Sales Trends for lisinopril
✉ Email this page to a colleague
Payment Methods and Pharmacy Types for lisinopril (2007)
Revenues by Pharmacy Type
Units Sold by Pharmacy Type
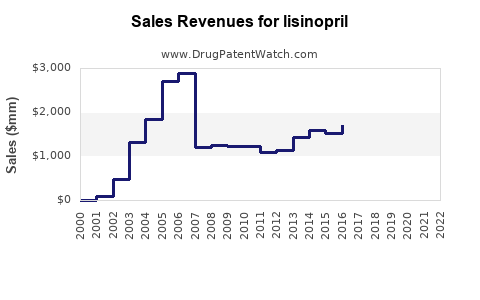
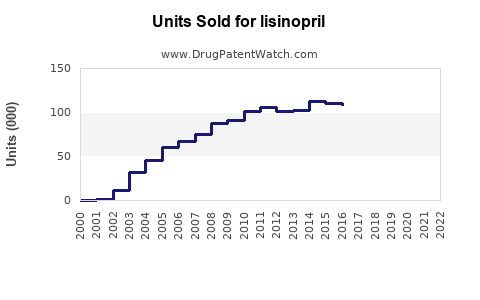
Annual Sales Revenues and Units Sold for lisinopril
| Drug Name | Revenues (USD) | Units | Year |
|---|---|---|---|
| LISINOPRIL | ⤷ Start Trial | ⤷ Start Trial | 2022 |
| LISINOPRIL | ⤷ Start Trial | ⤷ Start Trial | 2021 |
| LISINOPRIL | ⤷ Start Trial | ⤷ Start Trial | 2020 |
| LISINOPRIL | ⤷ Start Trial | ⤷ Start Trial | 2019 |
| LISINOPRIL | ⤷ Start Trial | ⤷ Start Trial | 2018 |
| >Drug Name | >Revenues (USD) | >Units | >Year |
Lisinopril Market Analysis, Sales Projections, Patent Status, and Generic Competition
Lisinopril is a mature, low-cost generic ACE inhibitor with high prescription volume and limited manufacturer pricing power. The core product patents expired years ago, FDA-approved generic competition is extensive, and no biosimilar pathway applies. The market should remain commercially durable because lisinopril is established in hypertension and heart-failure treatment, but revenue will decline gradually as reimbursement pressure and therapeutic substitution continue.
A base-case model projects global manufacturer net sales of lisinopril products at approximately $220 million to $300 million in 2025, declining to $160 million to $220 million by 2030. U.S. volume should remain comparatively stable while unit prices decline.
How large is the lisinopril market?
Lisinopril is one of the most widely used ACE inhibitors in the United States. It is prescribed primarily for hypertension, heart failure and post-myocardial-infarction treatment. The drug is available as a tablet and oral solution, both generally supplied through abbreviated new drug applications, or ANDAs.
The market has three distinct revenue layers:
- Manufacturer net sales from generic lisinopril tablets.
- Pharmacy and wholesaler revenue, which is higher than manufacturer revenue.
- Combination-product revenue, principally lisinopril/hydrochlorothiazide.
Public sources do not provide a single audited global revenue figure for all lisinopril manufacturers. The following estimates are an analyst model based on generic pricing, prescription persistence, market maturity and competitive intensity.
| Metric | 2025 estimate | 2030 base-case estimate | Direction |
|---|---|---|---|
| Global manufacturer net sales | $220 million-$300 million | $160 million-$220 million | Declining |
| U.S. manufacturer net sales | $120 million-$170 million | $85 million-$125 million | Declining |
| Global prescription volume | 180 million-240 million prescriptions | 175 million-235 million | Broadly stable |
| Average generic price | Low and highly variable | 15%-30% below 2025 level | Declining |
| Combination-product share | 10%-20% of related ACE-inhibitor revenue | 10%-18% | Stable to modestly lower |
The main commercial distinction is between volume and revenue. Lisinopril volume is resilient because of its low cost and long-standing clinical use. Revenue is weaker because numerous suppliers compete for the same prescriptions.
What are the main lisinopril indications and market drivers?
Lisinopril is approved for hypertension, acute myocardial infarction in appropriate patients and heart failure. The FDA label identifies the drug as an angiotensin-converting enzyme inhibitor that suppresses formation of angiotensin II and reduces aldosterone secretion (U.S. Food and Drug Administration [FDA], 2023).
Hypertension
Hypertension is the largest indication by prescription volume. Generic lisinopril remains attractive because it is familiar to prescribers, available in several strengths and inexpensive under retail, Medicaid and Medicare formularies.
Market growth is constrained by:
- Availability of angiotensin receptor blockers, or ARBs.
- Use of fixed-dose combinations.
- Patient switching caused by cough or angioedema.
- Increasing use of newer agents in patients with diabetes, chronic kidney disease or cardiovascular risk.
- Generic substitution at the pharmacy counter.
Heart failure
Lisinopril remains clinically relevant in heart failure with reduced ejection fraction, although newer guideline-directed therapies have reduced its strategic importance in treatment algorithms. Sacubitril/valsartan, sodium-glucose cotransporter-2 inhibitors, mineralocorticoid receptor antagonists and beta blockers compete for treatment priority in appropriate patients (Heidenreich et al., 2022).
Lisinopril retains an economic advantage in lower-income populations and in health systems with strict formulary controls.
Post-myocardial-infarction use
Use after myocardial infarction is established but represents a smaller share of total demand than hypertension. The indication supports continued prescribing in hospital and primary-care settings.
When did lisinopril lose exclusivity?
Lisinopril lost meaningful U.S. market exclusivity in the early 2000s. The original Zestril and Prinivil products were developed before the current generic market structure, and multiple generic manufacturers entered after expiration of the core patent and regulatory exclusivity.
| Asset | Product | Original innovator | Exclusivity position |
|---|---|---|---|
| Lisinopril tablets | Zestril | Astra/Zeneca lineage | Core exclusivity expired |
| Lisinopril tablets | Prinivil | Merck lineage | Core exclusivity expired |
| Lisinopril oral solution | Generic products | Multiple ANDA sponsors | No material branded barrier |
| Lisinopril/hydrochlorothiazide | Zestoretic and generics | Astra/Zeneca lineage | Core exclusivity expired |
The principal historical U.S. composition patent associated with lisinopril was U.S. Patent No. 4,374,829. Any patent-term-adjustment or patent-term-extension analysis must be conducted by patent and product because the effective expiration date can vary. That historical patent does not create a current barrier to ordinary generic lisinopril tablets.
What is the Orange Book status of lisinopril?
Lisinopril tablets are listed through multiple approved generic products in FDA databases. The Orange Book provides therapeutic-equivalence information for approved drug products, while FDA’s Drugs@FDA and ANDA records identify approval pathways and product sponsors (FDA, 2025a; FDA, 2025b).
The commercial Orange Book position is straightforward:
- Lisinopril is a small-molecule drug.
- Generic products are generally approved through ANDAs.
- AB-rated tablet products can be substituted where state law and payer rules permit.
- There is no active reference-product exclusivity protecting ordinary lisinopril tablets.
- The market is not dependent on one generic supplier.
The product has no biosimilar exposure because biosimilars apply to biologic reference products, not chemically synthesized lisinopril.
How many patents cover lisinopril?
No active core patent estate is known to block the commercial sale of standard lisinopril tablets in the United States. Historical patents covered the active pharmaceutical ingredient and branded products. Later patents may have covered specific formulations, manufacturing processes or combination products, but these do not generally create a broad market barrier for conventional lisinopril tablets.
| Patent category | Current commercial effect |
|---|---|
| Core lisinopril composition patents | Expired |
| Original branded-product patents | Expired or commercially irrelevant |
| Lisinopril/hydrochlorothiazide patents | Expired core protection |
| Oral-solution formulation patents | Limited product-specific relevance |
| Manufacturing-process patents | Potentially relevant to a supplier, not the overall market |
| Method-of-use patents | No broad barrier for established indications |
Patent strength is therefore low from an innovator perspective and moderate only at the level of individual generic suppliers that may possess process know-how, manufacturing capacity or regulatory data.
Are there current Paragraph IV challenges for lisinopril?
Paragraph IV litigation is not a meaningful current market driver for standard lisinopril tablets. Paragraph IV challenges were relevant during the original generic-entry period, when applicants sought to invalidate or avoid branded patents. That phase ended after the core exclusivity expired and numerous generic products entered.
Current competitive issues are more likely to involve:
- ANDA approval timing.
- FDA manufacturing inspections.
- Product-quality observations.
- Drug-supply contracts.
- State substitution rules.
- Reimbursement and wholesaler access.
A new Paragraph IV dispute would require a currently enforceable listed patent covering a relevant product or use. The ordinary lisinopril tablet market does not depend on such a patent.
Which companies compete in the lisinopril market?
The U.S. market has historically included large generic manufacturers and contract suppliers such as Viatris, Teva, Sandoz, Dr. Reddy’s Laboratories, Lupin, Zydus, Amneal and several private-label distributors. The exact active supplier set changes as companies discontinue low-margin products or transfer applications.
Competition is fragmented. No single manufacturer has a durable monopoly because:
- The drug is chemically straightforward.
- Multiple facilities can manufacture the active ingredient and finished tablets.
- Pharmacists can substitute AB-rated products.
- Large payers can shift volume among suppliers.
- Retail prices are highly transparent.
The strongest commercial positions typically belong to companies with efficient tablet operations, reliable API procurement, national wholesaler contracts and the ability to tolerate low margins.
What sales projections are reasonable for lisinopril through 2030?
Base-case projection
The base case assumes stable clinical demand, modest prescription erosion and continuing price compression.
| Year | Global manufacturer net sales | U.S. manufacturer net sales | Key assumption |
|---|---|---|---|
| 2025 | $220 million-$300 million | $120 million-$170 million | Mature generic market |
| 2026 | $210 million-$285 million | $115 million-$160 million | 3%-5% price decline |
| 2027 | $195 million-$270 million | $105 million-$150 million | Continued payer pressure |
| 2028 | $185 million-$250 million | $100 million-$140 million | Stable volume, lower price |
| 2029 | $175 million-$235 million | $92 million-$132 million | Increased therapeutic substitution |
| 2030 | $160 million-$220 million | $85 million-$125 million | Mature-market floor |
Scenario analysis
| Scenario | 2030 global sales | Operating conditions |
|---|---|---|
| Upside | $230 million-$300 million | Stable volume, supply disruptions, limited price erosion |
| Base case | $160 million-$220 million | 1%-2% annual volume decline and 4%-7% annual price erosion |
| Downside | $110 million-$160 million | Faster substitution, aggressive contracting and excess generic capacity |
The downside scenario does not require clinical obsolescence. It can occur through ordinary generic-market economics: lower reimbursement, fewer profitable suppliers and increased use of ARBs or newer heart-failure therapies.
What is the revenue exposure for manufacturers?
Lisinopril is usually a portfolio product rather than a strategic growth asset. For a diversified generic company, it is likely to represent a small percentage of total revenue. Its value comes from recurring demand, manufacturing scale and portfolio breadth.
Revenue exposure is higher for:
- Small regional manufacturers.
- Contract manufacturers dependent on a limited number of products.
- API suppliers with concentrated customer bases.
- Private-label distributors that compete mainly on price.
A supply interruption can temporarily raise prices, but sustained margin expansion is unlikely because additional generic capacity can enter when economics improve.
What formulations are protected by lisinopril patents?
The commercially relevant formulations include standard immediate-release tablets, oral solution and lisinopril/hydrochlorothiazide combination tablets. Historical formulation or process patents may have provided narrower protection, but they do not materially constrain standard generic tablets today.
Standard tablets
The most important commercial strengths are 2.5 mg, 5 mg, 10 mg, 20 mg and 40 mg. These products are simple immediate-release formulations and have low technical barriers.
Oral solution
Lisinopril oral solution has a smaller market and may require greater attention to stability, taste, packaging and dosing accuracy. It can provide niche value but does not support a large premium absent limited competition.
Combination products
Lisinopril/hydrochlorothiazide products address adherence and blood-pressure control. Their patents and exclusivity have expired, but combination products can preserve some commercial value through convenience and formulary positioning.
What manufacturing and intellectual-property barriers exist?
Manufacturing barriers are low to moderate. Lisinopril is not a complex biologic, sterile injectable or highly specialized delivery system. The main barriers are operational:
- Consistent API quality.
- Control of impurities and degradation products.
- Tablet content uniformity.
- Stability over the labeled shelf life.
- FDA compliance at API and finished-dose facilities.
- Reliable supply during demand or capacity shocks.
The intellectual-property barrier is low. The more meaningful barrier is regulatory execution. A company with an approved ANDA, inspected manufacturing site and dependable supply contracts has a stronger commercial position than a company with a nominally identical product but limited production reliability.
What licensing deals affect lisinopril?
The major licensing history is tied to the original branded products and legacy commercialization arrangements involving Astra/Zeneca and Merck. Those arrangements do not materially affect present generic pricing.
Current lisinopril economics are driven by ordinary supply agreements, contract manufacturing and private-label distribution. Publicly disclosed licensing deals are not a major source of differentiation in the mature market.
What generic launch risks exist?
A new lisinopril generic launch faces limited patent risk but substantial commercial risk.
Regulatory risk
FDA approval requires adequate bioequivalence, manufacturing compliance and product-quality controls. Deficiencies can delay approval or trigger site-related restrictions.
Pricing risk
A new supplier can enter a market with low barriers but face immediate price competition. Launch volume may be insufficient to offset validation, inventory and commercial-distribution costs.
Supply risk
API or finished-dose interruptions can create short-term opportunities, but buyers generally favor suppliers with established reliability. Temporary shortages do not guarantee durable share.
Reimbursement risk
Pharmacy benefit managers, Medicare plans, Medicaid programs and wholesalers can compress margins rapidly. A product with FDA approval may still lack economically attractive access.
How does lisinopril compare with competing drugs?
| Drug class | Representative products | Price position | Clinical-commercial effect |
|---|---|---|---|
| ACE inhibitors | Lisinopril, enalapril, ramipril | Very low | Mature, durable demand |
| ARBs | Losartan, valsartan, irbesartan | Low | Substitute when ACE-inhibitor cough occurs |
| ARNI | Sacubitril/valsartan | Much higher | Competes in selected heart-failure patients |
| SGLT2 inhibitors | Dapagliflozin, empagliflozin | Higher | Expands treatment alternatives in heart failure and diabetes |
| Calcium-channel blockers | Amlodipine | Very low | Major hypertension substitute |
| Thiazide diuretics | Hydrochlorothiazide, chlorthalidone | Very low | Common combination or alternative therapy |
Lisinopril is more exposed to ARBs in hypertension than to premium heart-failure products on a prescription-for-prescription basis. Its low price limits direct revenue competition, but guideline-driven substitution can gradually reduce volume.
Key Takeaways
- Lisinopril is a mature generic market with high volume and low pricing power.
- Core U.S. patent protection expired in the early 2000s.
- No biosimilar risk applies because lisinopril is a small-molecule drug.
- Current commercial competition is based on price, supply reliability, FDA compliance and payer access.
- Modeled global manufacturer net sales are approximately $220 million to $300 million in 2025.
- Base-case global sales decline to $160 million to $220 million by 2030.
- Prescription volume should remain relatively durable, but revenue will fall through generic price erosion.
- Combination products and oral solution provide niche opportunities, not broad exclusivity.
- Major current Paragraph IV litigation is not a central market risk.
- Lisinopril is more valuable as a stable portfolio product than as a growth asset.
FAQs
Is lisinopril still profitable for generic manufacturers?
Yes, but profitability depends on scale, supply reliability and manufacturing cost. Large-volume suppliers can earn acceptable returns, while smaller manufacturers may find margins unattractive.
Can a company obtain new exclusivity for a lisinopril product?
A new formulation, delivery system or approved indication could potentially support patent protection or regulatory exclusivity, but ordinary immediate-release tablets do not offer a realistic path to meaningful new exclusivity.
Does lisinopril have an active Orange Book patent?
Standard lisinopril tablets are not commercially blocked by an active core Orange Book patent. Product-specific listings should be checked in the current FDA Orange Book for the relevant strength and dosage form.
Will ARBs eliminate lisinopril demand?
No. ARBs will continue to take share from ACE inhibitors in patients who develop cough or cannot tolerate ACE inhibition, but lisinopril’s low price, clinical familiarity and broad availability support continued use.
Is lisinopril a good licensing or acquisition target?
It is generally a low-growth, low-complexity asset. It may be attractive when bundled with a broader generic portfolio, manufacturing platform or distribution network, but it is unlikely to justify a premium valuation as a standalone product.
References
-
Heidenreich, P. A., Bozkurt, B., Aguilar, D., Allen, L. A., Byun, J. J., Colvin, M. M., Deswal, A., Drazner, M. H., Dunlay, S. M., Evers, L. R., Fang, J. C., Fedson, S. E., Fonarow, G. C., Hayek, S. S., Hernandez, A. F., Khazanie, P., Kittleson, M. M., Lee, C. S., Link, M. S., ... Yancy, C. W. (2022). 2022 AHA/ACC/HFSA guideline for the management of heart failure. Circulation, 145(18), e895-e1032.
-
U.S. Food and Drug Administration. (2023). Lisinopril prescribing information. FDA.
-
U.S. Food and Drug Administration. (2025a). Approved drug products with therapeutic equivalence evaluations: Orange Book. FDA.
-
U.S. Food and Drug Administration. (2025b). Drugs@FDA and abbreviated new drug application records. FDA.
-
U.S. Patent and Trademark Office. (1983). U.S. Patent No. 4,374,829: Lisinopril and related compounds. USPTO.
More… ↓
