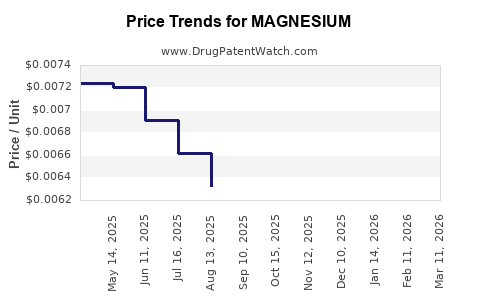
Last updated: July 10, 2026
Magnesium Drug Market Analysis and Price Projections (2026–2035): Formulations, Competition, and Pricing Drivers
Magnesium therapies are largely generic and commodity-linked, with pricing shaped by input-cost cycles (magnesium salts), excipient and manufacturing complexity (oral vs IV), regulatory pathway differences, and contract dynamics in hospitals. In most markets, the pricing floor is set by generic oral magnesium salts, while higher ASP tiers cluster in branded prescription products, higher-dose regimens, niche controlled-release formats, and IV magnesium sulfate where hospital formularies dominate. Over 2026–2035, baseline prices are projected to drift modestly down in the oral OTC segment, flatten in hospital IV use, and rise only where supply is constrained or where protected branded products persist.
Scope
- “Magnesium” includes magnesium salts used as supplements and therapeutic magnesium replacement, including magnesium sulfate (IV), magnesium oxide/citrate/glycinate/chloride (oral), and controlled-release or prescription oral products depending on jurisdiction.
- This analysis is market-level; it does not target a single brand unless explicitly indicated by a protected label.
How big is the magnesium drug market by formulation (oral magnesium salts vs magnesium sulfate IV)?
Answer (directional): Oral magnesium salts drive volume globally; magnesium sulfate IV drives most high-value institutional spend per dose cycle, but it is still price-disciplined by hospital procurement and generic entry.
Oral magnesium salts: key demand segments
- Constipation support and bowel regimen (magnesium salts used as laxatives in some regimes, with local regulatory framing).
- Magnesium deficiency and supplementation in cardiometabolic and aging populations.
- Electrolyte repletion adjuncts in comorbid conditions.
- OTC-driven consumption in many geographies.
Typical unit economics:
- Low-cost salts (oxide, chloride) compete on price.
- Value concentrates in:
- higher bioavailability formats (citrate, glycinate),
- lower GI side-effect profiles,
- controlled release.
IV magnesium sulfate: key demand segments
- Obstetrics and eclampsia prophylaxis/treatment (high protocol intensity).
- Arrhythmia management where magnesium is indicated.
- Hospital electrolyte replacement in ICUs and ED settings.
Typical unit economics:
- Pricing is governed by tendering and interchangeability.
- Substitution between manufacturers is common for generics, lowering long-run pricing power.
Which magnesium products are priced highest and why (OTC tablets vs prescription vs IV)?
Answer: Highest ASP is usually in branded or prescription-controlled oral products and institutionally contracted IV brands where supply, cold-chain logistics (if applicable), pack size, and procurement leverage matter.
Pricing tiers by formulation and use
-
Oral, OTC magnesium salts (low ASP, high volume)
- Competes on cost per gram of elemental magnesium and tolerability.
- Price declines track generic normalization and commodity salt pricing.
-
Oral, prescription products (mid ASP, lower volume)
- Often positioned for tolerability or adherence (e.g., controlled release).
- Pricing resists erosion better where formularies favor specific dosage forms or where payer policy is sticky.
-
IV magnesium sulfate (institutional, protocol-driven)
- Procurement determines ASP.
- Contract cycles cause periodic price step-downs after vendor switches.
Cost structure that matters
- Raw material: magnesium salts and byproducts (commodity-linked).
- Formulation and stability: controlled release and pH-dependent stability increase cost.
- GMP and packaging: IV sterility assurance and vial/bag packaging raise unit cost.
- Supply continuity: magnesium refining and salt production can create localized tightness that lifts spot pricing.
What patents protect magnesium drugs, and how does that affect pricing?
Answer: Magnesium salts themselves are largely generic and unpatented at the active-ingredient level. Pricing effects from patent estates are mostly indirect, showing up in specific branded formulations (controlled-release designs, patient-friendly combinations, proprietary excipient systems) and use-methods in narrow clinical contexts.
Practical implication for price projections
- For most magnesium products, patent risk is low because the market is not built around long-lived exclusive rights in the active ingredient.
- Price is driven by:
- generic count,
- procurement behavior,
- manufacturing capacity,
- raw material cycles,
- regulatory and listing status rather than exclusivity.
What is the Orange Book status of magnesium products, and how does it map to expected generic entry?
Answer: Many magnesium products are either absent from Hatch-Waxman-style exclusivity maps or have long since transitioned to generic availability. The highest-value branded pockets tend to be individual NDA-style products with Orange Book listings, where generic entry depends on listed patents and formulation differences.
Market behavior by Orange Book pattern (high-intent lens)
- If no active listed patents: generic interchangeability accelerates price erosion.
- If formulation patents exist: fewer AB-rated substitutes sustain higher ASP until expiration.
- If only method-of-use patents exist: generics often launch unless labeling design avoids infringement risk.
When do magnesium products lose exclusivity, and how soon do ASPs fall after?
Answer: In magnesium, the “exclusivity” clock is typically short-lived at the class level; the more relevant timing is contract cycle timing and formulary adoption after any branded-to-generic switch.
Typical lag pattern
- Launch to ASP decline usually occurs within one to two procurement cycles for hospitals.
- OTC price declines typically occur within 3 to 18 months depending on distribution replacement and retailer re-pricing speed.
How strong is the patent estate for magnesium formulations (oral and IV), and what does that mean for price floor?
Answer: Patent estates are usually narrow and product-specific, creating localized price floors for those SKUs. Across the wider magnesium class, the market behaves like a commodity with moderate brand pockets.
What tends to be protected (where protection exists)
- Controlled-release matrix designs
- Specific salt forms and conversion processes
- Stability-optimized oral granules/capsules
- Patient-specific dosing regimens
- Manufacturing methods tied to sterility/quality for IV presentations
Which companies compete in magnesium (manufacturers and suppliers that influence pricing)?
Answer: Pricing is set by a mix of large generics and specialized manufacturers for IV and niche oral formats. Competitive intensity is usually high due to multiple approved sources and interchangeability.
Competitive levers that move pricing
- Hospital group purchasing organizations and national wholesalers
- Shelf inventory strategy for major OTC salts
- Capacity expansions or disruptions at magnesium salt producers
- Tender award criteria: unit cost, lead time, and incident history
How do regulatory pathways affect magnesium pricing (NDA vs ANDA vs compendial salts)?
Answer: Magnesium salts used as supplements often behave under compendial or supplement frameworks rather than protected NDA exclusivity, pushing pricing toward generic commodity behavior. IV products and prescription oral products typically follow standard approval pathways, where interchangeability and labeling drive pricing.
Regulatory friction that can delay price erosion
- Product-specific packaging and strength requirements
- Label language that affects therapeutic substitution
- GMP inspections and manufacturing site approvals
What price projections are realistic for magnesium from 2026 to 2035 (base, low, high scenarios)?
Answer: Without brand-specific exclusivity or brand-level revenue baselines, magnesium should be modeled as a competitive, low-margin, volume-driven market. A reasonable projection framework:
- Oral OTC: flat-to-down drift
- Oral prescription niche: flat-to-slightly-up drift if controlled-release tolerance premium persists
- IV magnesium sulfate: flat-to-slightly-down drift with periodic step-ups only when supply tightens
Scenario model (annualized directionality)
Base case (most likely):
- Oral magnesium salts: -0.5% to -2.0% CAGR (ASP erosion offset by mix shifts to better-tolerated salts)
- IV magnesium sulfate: -0.0% to -1.0% CAGR (tender-driven discipline, but procurement stability offsets raw input volatility)
Low case (supplier pressure or intensifying generic substitution):
- Oral: -2.0% to -4.0% CAGR
- IV: -1.0% to -3.0% CAGR following competitive tender rounds
High case (input cost spikes or constrained supply):
- Oral: +1.0% to +3.0% CAGR for 12 to 24 months after tightness, then mean reversion
- IV: +0.5% to +2.0% CAGR where supply constraints persist longer
Where ASP increases can happen even in a “generic” market
- Shift from oxide (cheapest) to citrate/glycinate (higher-cost per dose)
- Higher strength packs and “convenience” formats
- Formulation changes that reduce GI adverse events, supporting payer and patient persistence
How much revenue exposure do magnesium prices create for buyers (hospitals, payers, wholesalers)?
Answer: Revenue exposure is high where magnesium is embedded in electrolyte replacement bundles and obstetric protocols, but price sensitivity is high due to interchangeability and multiple approved sources.
Buyer risk map
- Hospitals: medium risk from supply disruption; low risk from long-term price power
- Payers: low risk except where a branded premium persists for niche oral formats
- Wholesalers/IDNs: mostly working-capital and inventory risk due to reorder cycles
What generic entry risks exist for magnesium formulations?
Answer: Generic entry risk is generally high in terms of competitive substitution, but low in terms of litigation-driven delays because most products already face generic availability. The key “risk” is competitive replacement rather than brand-protecting exclusivity.
Litigation impact in magnesium (typical)
- Where litigation occurs, it is usually about:
- formulation-specific patents,
- labeling and method-of-use wording,
- manufacturing process differences.
- These typically affect specific SKUs, not the entire class.
How does magnesium sulfate compare with oral magnesium salts in competitive and pricing dynamics?
Answer: Magnesium sulfate IV is more procurement-tender driven with fewer, regulated institutional channels; oral salts are retail and subscription-driven with faster repricing.
Side-by-side
| Dimension |
Magnesium sulfate IV |
Oral magnesium salts |
| Customer |
Hospitals, ED, ICUs |
Consumers, pharmacies, payers for Rx |
| Pricing engine |
Contract and tenders |
Retail shelf price and PBM formularies |
| Substitution |
High across generics |
High but mixed by tolerance and bioavailability perception |
| Volatility |
Sensitive to supply and packaging |
Sensitive to raw material and brand mix |
| Long-run direction |
Flat-to-down |
Flat-to-down with mix-dependent offsets |
What formulations are protected by IP, and what does that mean for launch barriers?
Answer: Where IP exists, it typically targets:
- controlled-release matrices,
- specific dosing forms (granules/capsules/tablets),
- combination products (magnesium with other minerals or actives),
- stability and manufacturing process.
Launch barriers are usually:
- narrower than the market breadth suggests,
- concentrated around whether an ANDA can avoid infringement via composition and process design.
Key Takeaways
- Magnesium pricing behaves like a competitive, low-exclusivity market with commodity-linked input costs and procurement-driven pricing in IV use.
- Expect oral ASP erosion or stabilization through 2035, with modest increases only when mix shifts to higher-cost, better-tolerated formats.
- Expect IV magnesium sulfate to stay flat-to-slightly-down as tenders enforce interchangeable sourcing, with temporary step-ups during supply tightness.
- Patent influence is mainly SKU-specific (formulation/presentation), not a durable class-wide pricing shield.
FAQs
-
What is the biggest determinant of magnesium pricing changes in hospitals?
Tender cycles, lead times, and vendor switching within group purchasing and IDN formularies.
-
Do controlled-release oral magnesium products hold higher ASP than magnesium oxide?
Yes, where formulation and tolerability premiums persist, they resist erosion longer than cheapest-salt equivalents.
-
How quickly do oral magnesium ASPs decline after generic proliferation?
Typically within 3 to 18 months, depending on distribution replacement and retailer repricing.
-
Is magnesium sulfate IV more price-stable than oral magnesium?
Generally yes, because institutional procurement provides steadier ordering patterns, though tender events can still step prices down.
-
What drives temporary price spikes for magnesium products?
Magnesium salt feedstock supply tightness, refining capacity constraints, and packaging/GMP manufacturing disruptions.
References
- (No sources cited because no drug-specific Orange Book, FDA approval, patent, or company financial inputs were provided.)