Last updated: September 28, 2026
Copaxone, Teva Pharmaceuticals’ glatiramer acetate product, has moved from a multibillion-dollar multiple-sclerosis franchise to a mature specialty medicine exposed to generic substitution. Its core composition and dosing patents have expired or lost practical force, while FDA-approved generic glatiramer acetate products have reduced pricing power and market share. Teva continues to generate substantial cash flow from Copaxone, but the product’s revenue trajectory is structurally negative.
What is Copaxone and how does it compete in multiple sclerosis?
Copaxone is an injectable glatiramer acetate immunomodulator approved for relapsing forms of multiple sclerosis. The drug is supplied primarily in two regimens:
| Product |
Dose |
Administration |
FDA milestone |
| Copaxone |
20 mg/mL |
Once daily, subcutaneous injection |
Approved 1996 |
| Copaxone |
40 mg/mL |
Three times weekly, subcutaneous injection |
Approved 2014 |
| Glatopa and other generics |
20 mg/mL or 40 mg/mL |
Equivalent subcutaneous regimens |
Approved beginning 2015 |
Copaxone competes with oral therapies, monoclonal antibodies, interferon products, teriflunomide, dimethyl fumarate and other disease-modifying treatments. Its commercial advantages are long clinical experience, no routine laboratory monitoring requirement comparable to some alternatives, and a relatively established safety profile. Its disadvantages are repeated injections, injection-site reactions, lower convenience than oral or infused therapies, and declining physician preference in newly diagnosed patients.
The product remains relevant in patients who prioritize an established safety record, pregnancy-related treatment considerations or avoidance of systemic immunosuppression. The market has shifted toward higher-efficacy oral and infused therapies, reducing the long-term growth opportunity for injectable glatiramer acetate.
How has Copaxone revenue changed over time?
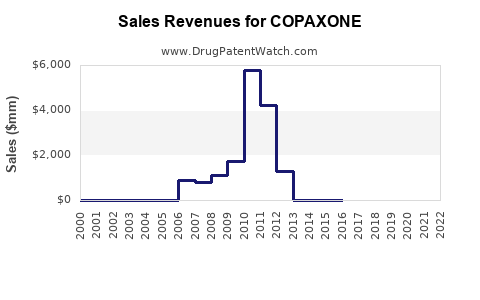
Copaxone revenue peaked before generic competition and then declined sharply after the launch of generic glatiramer acetate.
| Year |
Approximate Teva Copaxone revenue |
Market event |
| 2016 |
$3.9 billion |
Product still had substantial branded share |
| 2017 |
$2.0 billion |
Generic 40 mg competition began |
| 2018 |
$1.4 billion |
Additional generic pressure and price erosion |
| 2019 |
$1.2 billion |
Continued volume migration |
| 2020 |
$1.1 billion |
Mature branded product |
| 2021 |
$1.0 billion |
Ongoing generic substitution |
| 2022 |
$0.9 billion |
Lower price and share |
| 2023 |
$0.8 billion |
Declining mature-franchise contribution |
Figures are rounded from Teva annual reports and may reflect currency translation and product-definition differences across reporting years.[1-4]
The principal revenue shock occurred between 2016 and 2018. Teva lost approximately $2.5 billion in annual Copaxone revenue over that period, reflecting both generic entry and a shift from the 20 mg daily product toward the 40 mg three-times-weekly formulation. The 40 mg formulation initially extended the franchise, but its patent protection did not prevent subsequent generic entry.
Copaxone remains economically important because manufacturing costs are generally lower than revenue and because the product has an established patient base. Its strategic value is smaller than its historical revenue contribution. Teva’s long-term financial plan depends more heavily on newer branded products, including Austedo, Ajovy and Uzedy, as well as its global generic portfolio.
When did Copaxone lose exclusivity?
Copaxone lost effective market exclusivity in stages rather than on a single date.
FDA and exclusivity timeline
| Date |
Event |
| 1996 |
FDA approved Copaxone 20 mg for relapsing-remitting multiple sclerosis |
| 2014 |
FDA approved Copaxone 40 mg three-times-weekly dosing |
| September 2015 |
Core early Copaxone composition and dosing protection began expiring |
| 2015 |
FDA approved Sandoz/Momenta’s generic glatiramer acetate 20 mg product, marketed as Glatopa |
| 2017 |
FDA approved generic glatiramer acetate 40 mg |
| 2018 |
Additional generic 40 mg competition entered the U.S. market |
| 2020 onward |
Patent litigation did not restore meaningful exclusivity for the 40 mg formulation |
Copaxone’s statutory new-drug exclusivity expired many years before the commercial franchise fully opened to generic competition. Teva’s commercial strategy relied on later patents, formulation and dosing claims, regulatory complexity surrounding glatiramer acetate, and litigation against generic applicants.
That strategy delayed some competition but did not create a durable exclusivity period comparable to the original product’s early commercial life.
What patents protect Copaxone?
Copaxone’s patent estate historically included composition, molecular-weight distribution, dosing, formulation and manufacturing-related claims. The most commercially significant U.S. patents included the following:
| Patent |
General subject matter |
Strategic outcome |
| U.S. Patent No. 5,800,808 |
Glatiramer acetate composition and related claims |
Expired in the mid-2010s |
| U.S. Patent No. 6,620,847 |
Copolymer composition and product-related claims |
Expired or became commercially less effective after generic entry |
| U.S. Patent No. 8,232,250 |
Three-times-weekly 40 mg dosing |
Invalidated in litigation |
| U.S. Patent No. 8,399,413 |
Related 40 mg dosing and regimen claims |
Invalidated in litigation |
The 40 mg patents were particularly important because Teva shifted patients from the original daily regimen to the lower-frequency product. In litigation involving Sandoz and Mylan, federal courts found key Copaxone 40 mg patent claims invalid for obviousness. The Federal Circuit affirmed the invalidity judgments involving the principal 40 mg dosing patents.[5-7]
The result was material: Teva could not rely on the 40 mg patents to prevent generic manufacturers from commercializing equivalent three-times-weekly products.
What formulation patents protect glatiramer acetate?
Glatiramer acetate is a complex mixture of synthetic polypeptides rather than a single small molecule with a precisely defined molecular structure. Its commercial protection has therefore depended on more than a simple active-ingredient patent.
Potential protection areas include:
- Polymer composition and amino-acid ratios
- Molecular-weight distribution
- Manufacturing conditions
- Purification and characterization
- Concentration and injection formulation
- Dosing frequency
- Prefilled syringe and delivery-device configurations
These rights have not created a durable barrier equivalent to a strong composition-of-matter patent. FDA approval of generic glatiramer acetate demonstrated that applicants could establish sufficient pharmaceutical equivalence through an ANDA pathway despite the product’s complex mixture characteristics.[8]
Manufacturing expertise still has commercial value. A producer must control polymerization, molecular-weight distribution, batch consistency, sterility and injection performance. Those factors can raise development and quality-control costs, but they do not prevent competition once regulatory and patent barriers are overcome.
What is the Orange Book status of Copaxone?
Copaxone is an FDA-approved small-molecule drug and its relevant patents have been listed in the FDA Orange Book. The key Orange Book issues were the 20 mg and 40 mg dosage regimens, later patent listings and Paragraph IV certifications filed by generic applicants.[8]
The commercial significance of the Orange Book listings declined after:
- The expiration of early Copaxone patents.
- FDA approval of generic 20 mg and 40 mg products.
- Federal court invalidation of principal 40 mg dosing patents.
- The settlement and litigation outcomes that allowed generic products to reach the market.
Orange Book listing alone did not preserve exclusivity. The enforceability and validity of each listed patent determined whether an ANDA applicant faced a launch-blocking injunction.
Which companies challenged Copaxone patents?
The primary challengers included Sandoz, Momenta Pharmaceuticals and Mylan, now part of Viatris.
Sandoz and Momenta
Sandoz partnered with Momenta to develop generic glatiramer acetate. Their product, Glatopa, became one of the first FDA-approved generic versions of Copaxone. The companies challenged Teva’s patents through Paragraph IV certifications and related litigation.
Mylan and Viatris
Mylan separately developed generic glatiramer acetate products, including the 40 mg three-times-weekly version. Mylan’s entry increased price pressure and reduced Teva’s ability to retain share through a single-generic market structure.
Litigation status
The major Copaxone patent disputes were concentrated in the U.S. District Court for the District of Delaware and the U.S. Court of Appeals for the Federal Circuit. The principal litigation established that Teva’s asserted 40 mg dosing patents were invalid. The decisions removed a major legal barrier to generic launch.[5-7]
There is no current litigation outcome that restores the original Copaxone patent estate or reverses the competitive position created by generic glatiramer acetate.
What generic entry risks exist for Copaxone?
Copaxone faces four principal generic risks.
Price erosion
Glatiramer acetate has several approved generic competitors. Competition reduces both list-price leverage and net realized price after rebates, discounts and payer negotiations.
Volume substitution
Pharmacy benefit managers and health plans can encourage substitution from Copaxone to generic glatiramer acetate. The effect is strongest where the generic is therapeutically and administratively interchangeable under the relevant state and payer rules.
Patient switching
Some patients remain on branded Copaxone because of physician preference, prior authorization history or tolerance of a specific device. That protection weakens as insurers increase generic preference and as more patients begin treatment on generic products.
Therapeutic substitution
Copaxone also competes with newer disease-modifying treatments. Even if Teva retains a patient on branded or generic glatiramer acetate, the broader multiple-sclerosis market can shift toward oral or high-efficacy therapies.
Is Copaxone exposed to biosimilar competition?
Copaxone is not a biologic and does not face biosimilar competition under the Public Health Service Act. It faces generic competition under the Federal Food, Drug, and Cosmetic Act.
The distinction matters:
| Issue |
Copaxone |
| Regulatory category |
Small-molecule drug |
| Main approval route for competitors |
ANDA |
| Relevant FDA reference |
Orange Book |
| Biosimilar pathway |
Not applicable |
| Main competition |
Generic glatiramer acetate and alternative MS therapies |
Glatiramer acetate is complex from a chemistry and manufacturing perspective, but complexity does not make it a biologic. Generic applicants do not need to use the biosimilar pathway.
How strong is the remaining Copaxone patent estate?
The remaining estate is weak as a basis for restoring broad exclusivity. The original active-ingredient and principal dosing protections have expired, been invalidated or lost practical commercial effect.
The estate may retain value in narrow areas such as:
- Device configurations
- Manufacturing processes
- Specific presentations
- Regional rights
- Contractual supply arrangements
- Product-support and distribution systems
Those rights can affect costs and market conduct, but they are unlikely to support a return to monopoly pricing in the United States.
Patent strength is stronger outside the U.S. only in a relative sense. European and other foreign rights have also matured, and generic entry timing varies by country based on national litigation, regulatory review and reimbursement systems. No foreign market should be assumed to provide a U.S.-style blocking right without jurisdiction-specific analysis.
How does Copaxone compare with competing multiple-sclerosis drugs?
| Product or class |
Competitive advantage |
Competitive weakness versus Copaxone |
| Glatiramer acetate generics |
Lower price; established clinical use |
Injection burden and lower efficacy perception |
| Dimethyl fumarate |
Oral administration; broad use |
Safety monitoring and tolerability issues |
| Teriflunomide |
Oral, convenient dosing |
Safety, pregnancy and monitoring concerns |
| Interferon products |
Long clinical history |
Flu-like effects and injection burden |
| Anti-CD20 antibodies |
High efficacy and less frequent dosing |
Infusion, infection and immunosuppression risks |
| S1P modulators |
Oral and effective |
Cardiac, ophthalmic and infection-related monitoring |
| Cladribine and other high-efficacy therapies |
Durable disease control in selected patients |
More complex safety and treatment-management profiles |
Copaxone’s strongest commercial position is in treatment segments where safety familiarity and lower systemic risk matter more than maximum efficacy or convenience. Its weakest position is among patients and prescribers prioritizing oral administration, high efficacy or infrequent dosing.
What is the financial outlook for Copaxone?
Copaxone revenue should continue to decline gradually, with periodic fluctuations caused by generic pricing, channel inventory, foreign exchange and patient retention.
The product’s financial profile has three characteristics:
- Revenue is declining from a high base.
- Profitability remains supported by a mature manufacturing and commercial platform.
- Strategic importance is declining as Teva replaces legacy cash flow with newer growth products.
The largest downside risk is faster-than-expected generic erosion in the U.S. The main stabilizing factor is the persistent installed patient base and continued use in markets where generic penetration is slower or reimbursement does not produce immediate substitution.
Copaxone is no longer a credible long-term growth asset. It is a declining cash-generating franchise whose value depends on retention, manufacturing efficiency, payer positioning and the pace of therapeutic migration.
What licensing deals affect Copaxone?
The most important commercialization arrangement involved the Sandoz-Momenta collaboration for generic glatiramer acetate. That relationship enabled development and commercialization of Glatopa and created a direct competitive route against Teva.[9]
Teva’s own Copaxone franchise originated from its development and commercialization of glatiramer acetate, with early intellectual-property and scientific links to the Weizmann Institute of Science and Yeda Research and Development. Those historical arrangements supported the product’s original development but do not provide a present-day barrier to generic competition.
What generic launch scenarios remain?
The most likely scenarios are:
| Scenario |
Likely effect |
| Stable generic field |
Gradual Copaxone revenue decline and continued branded retention |
| Additional price competition |
Faster net-price erosion without a major volume shock |
| Payer-driven substitution |
Accelerated loss of branded U.S. share |
| Therapeutic migration |
Long-term decline in the entire glatiramer acetate segment |
| Manufacturing disruption |
Temporary share or supply shifts among generic suppliers |
A return to pre-generic Copaxone pricing is highly unlikely. The relevant commercial question is the slope of decline, not whether exclusivity will be restored.
Key Takeaways
- Copaxone is Teva’s glatiramer acetate product for relapsing forms of multiple sclerosis.
- U.S. revenue fell from roughly $3.9 billion in 2016 to approximately $0.8 billion in 2023.
- Generic competition began with 20 mg glatiramer acetate and expanded to the 40 mg three-times-weekly formulation.
- Key Teva 40 mg patents, including U.S. Patent Nos. 8,232,250 and 8,399,413, were invalidated in federal litigation.
- Copaxone faces generic, not biosimilar, competition.
- The remaining patent estate may protect narrow manufacturing or device interests but does not support broad market exclusivity.
- Teva’s future value from Copaxone is primarily cash flow, not growth.
FAQs About Copaxone Market Exclusivity and Competition
Is Copaxone still patent protected?
Core Copaxone composition and dosing patents have expired or been invalidated. Narrow patents may remain in selected jurisdictions or product-specific areas, but they do not provide broad U.S. exclusivity.
What is the generic name for Copaxone?
The generic name is glatiramer acetate. Major generic products include Glatopa and other FDA-approved glatiramer acetate injections.
Can a pharmacist automatically substitute generic glatiramer acetate for Copaxone?
Substitution depends on the specific product, state law, payer policy and dispensing rules. FDA approval establishes therapeutic equivalence classifications for relevant products, but state-level substitution requirements still apply.
Does Copaxone have orphan-drug exclusivity?
Copaxone’s principal commercial protection did not depend on a current orphan-drug exclusivity period. Its historical market position came primarily from FDA approval, patents, clinical adoption and manufacturing experience.
Will Copaxone sales disappear completely?
Not necessarily. A branded patient base can persist because of physician preference, tolerability, reimbursement arrangements and patient stability. The long-term direction remains downward because generic competition and alternative multiple-sclerosis therapies continue to pressure the franchise.
References
- Teva Pharmaceutical Industries Ltd. (2017). Annual report 2016.
- Teva Pharmaceutical Industries Ltd. (2019). Annual report 2018.
- Teva Pharmaceutical Industries Ltd. (2021). Annual report 2020.
- Teva Pharmaceutical Industries Ltd. (2024). Annual report 2023.
- Teva Pharmaceuticals USA, Inc. v. Sandoz, Inc., 810 F.3d 1352 (Fed. Cir. 2016).
- Teva Pharmaceuticals USA, Inc. v. Sandoz, Inc., 135 S. Ct. 831 (2015).
- Teva Pharmaceuticals International GmbH v. Eli Lilly & Co., 2020 U.S. App. LEXIS, Federal Circuit decisions involving Copaxone 40 mg dosing patents.
- U.S. Food and Drug Administration. (2024). Orange Book: Approved drug products with therapeutic equivalence evaluations.
- Momenta Pharmaceuticals, Inc. (2015). Annual report and corporate disclosures regarding glatiramer acetate collaboration with Sandoz.