Epinephrine - Generic Drug Details
What are the generic sources for epinephrine and what is the scope of patent protection?
Epinephrine
is the generic ingredient in thirty-five branded drugs marketed by Sterling, Armstrong Pharms, Wyeth Cons, Forest Labs, Viatris, Impax, Teva Pharms Usa, Ph Health, Am Regent, Amneal, Apotex, Baxter Hlthcare Corp, Bpi Labs, Deva Hlding, Fresenius Kabi Usa, Gland, Hikma, Intl Medication Sys, Zydus Pharms, Kaleo Inc, Adamis Pharms Corp, Hospira, Ars Pharms Operation, 3M, Astrazeneca, Dentsply Pharm, Deproco, Septodont Inc, Carlisle, B Braun Medical, Belmora Llc, Eastman Kodak, West-ward Pharms Int, Abbott, Bel Mar, Dell Labs, Intl Medication, Watson Labs, Pharmaton, Septodont, Vyteris, Iomed, and Empi, and is included in seventy-five NDAs. There are twenty-eight patents protecting this compound and three Paragraph IV challenges. Additional information is available in the individual branded drug profile pages.Thirty-three suppliers are listed for this compound. There are two tentative approvals for this compound.
Summary for epinephrine
| International Patents: | 239 |
| US Patents: | 28 |
| Tradenames: | 35 |
| Applicants: | 40 |
| NDAs: | 72 |
| Finished Product Suppliers / Packagers: | 33 |
| Raw Ingredient (Bulk) Api Vendors: | 88 |
| Clinical Trials: | 824 |
| Patent Applications: | 6,198 |
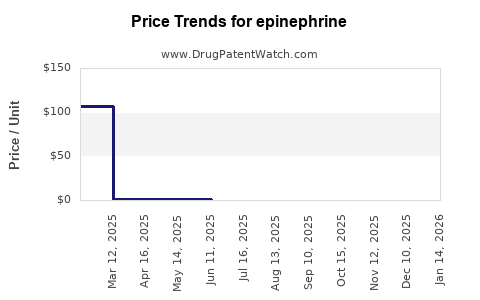
| Drug Prices: | Drug price trends for epinephrine |
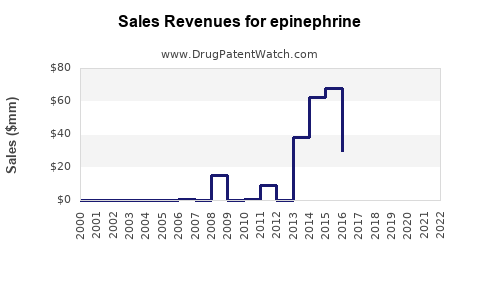
| Drug Sales Revenues: | Drug sales revenues for epinephrine |
| Patent Litigation and PTAB cases: | See patent lawsuits and PTAB cases for epinephrine |
| What excipients (inactive ingredients) are in epinephrine? | epinephrine excipients list |
| DailyMed Link: | epinephrine at DailyMed |
Recent Clinical Trials for epinephrine
Identify potential brand extensions & 505(b)(2) entrants
| Sponsor | Phase |
|---|---|
| University of California, San Francisco | PHASE2 |
| Hospital del Trabajador de Santiago | NA |
| Goldman, Butterwick, Fitzpatrick and Groff | PHASE4 |
Generic filers with tentative approvals for EPINEPHRINE
| Applicant | Application No. | Strength | Dosage Form |
| ⤷ Start Trial | ⤷ Start Trial | EQ 1MG BASE/ML (EQ 1MG BASE/ML) | SOLUTION;INTRAMUSCULAR, INTRAVENOUS, SUBCUTANEOUS |
| ⤷ Start Trial | ⤷ Start Trial | EQ 4MG BASE/250ML (EQ 16MCG BASE/ML) | SOLUTION;INTRAVENOUS |
| ⤷ Start Trial | ⤷ Start Trial | EQ 16MG BASE/250ML (EQ 64MCG BASE/ML) | SOLUTION;INTRAVENOUS |
The 'tentative' approval signifies that the product meets all FDA standards for marketing, and, but for the patents / regulatory protections, it would approved.
Pharmacology for epinephrine
| Drug Class | Catecholamine alpha-Adrenergic Agonist beta-Adrenergic Agonist |
| Mechanism of Action | Adrenergic alpha-Agonists Adrenergic beta-Agonists |
Medical Subject Heading (MeSH) Categories for epinephrine
Anatomical Therapeutic Chemical (ATC) Classes for epinephrine
Paragraph IV (Patent) Challenges for EPINEPHRINE
| Tradename | Dosage | Ingredient | Strength | NDA | ANDAs Submitted | Submissiondate |
|---|---|---|---|---|---|---|
| NEFFY | Nasal Spray | epinephrine | 1 mg/spray | 214697 | 1 | 2025-12-29 |
| NEFFY | Nasal Spray | epinephrine | 2 mg/spray | 214697 | 1 | 2025-06-30 |
| EPINEPHRINE | Injection | epinephrine | 1 mg/mL | 205029 | 1 | 2020-08-13 |
| ADRENALIN | Injection | epinephrine | 30 mg/30 mL | 204640 | 1 | 2018-08-20 |
| ADRENALIN | Injection | epinephrine | 1 mg/mL ampules | 204200 | 1 | 2016-03-09 |
| EPIPEN JR. | Injection (Auto- injector) | epinephrine | 0.15 mg/0.3 mL and 0.3 mg/0.3 mL | 019430 | 1 | 2009-07-20 |
US Patents and Regulatory Information for epinephrine
| Applicant | Tradename | Generic Name | Dosage | NDA | Approval Date | TE | Type | RLD | RS | Patent No. | Patent Expiration | Product | Substance | Delist Req. | Exclusivity Expiration |
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Kaleo Inc | AUVI-Q | epinephrine | SOLUTION;INTRAMUSCULAR, SUBCUTANEOUS | 201739-002 | Aug 10, 2012 | BX | RX | Yes | Yes | 8,226,610 | ⤷ Start Trial | Y | ⤷ Start Trial | ||
| Ars Pharms Operation | NEFFY | epinephrine | SPRAY;NASAL | 214697-002 | Mar 5, 2025 | RX | Yes | Yes | 11,918,655 | ⤷ Start Trial | ⤷ Start Trial | ||||
| Amneal | EPINEPHRINE | epinephrine | SOLUTION;INTRAMUSCULAR, INTRAVENOUS, SUBCUTANEOUS | 217485-001 | Oct 14, 2025 | AP | RX | No | No | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | |||
| Ph Health | ADRENALIN | epinephrine | SOLUTION;INTRAMUSCULAR, INTRAVENOUS, SUBCUTANEOUS | 204640-001 | Dec 18, 2013 | AP | RX | Yes | Yes | 9,295,657 | ⤷ Start Trial | ⤷ Start Trial | |||
| Intl Medication Sys | EPINEPHRINE | epinephrine | SOLUTION;INTRAVENOUS | 211363-001 | Aug 15, 2022 | RX | Yes | Yes | ⤷ Start Trial | ⤷ Start Trial | ⤷ Start Trial | ||||
| Kaleo Inc | AUVI-Q | epinephrine | SOLUTION;INTRAMUSCULAR, SUBCUTANEOUS | 201739-003 | Nov 17, 2017 | RX | Yes | No | 8,206,360 | ⤷ Start Trial | Y | ⤷ Start Trial | |||
| >Applicant | >Tradename | >Generic Name | >Dosage | >NDA | >Approval Date | >TE | >Type | >RLD | >RS | >Patent No. | >Patent Expiration | >Product | >Substance | >Delist Req. | >Exclusivity Expiration |
Expired US Patents for epinephrine
| Applicant | Tradename | Generic Name | Dosage | NDA | Approval Date | Patent No. | Patent Expiration |
|---|---|---|---|---|---|---|---|
| Kaleo Inc | AUVI-Q | epinephrine | SOLUTION;INTRAMUSCULAR, SUBCUTANEOUS | 201739-002 | Aug 10, 2012 | 8,926,594 | ⤷ Start Trial |
| Viatris | EPIPEN | epinephrine | INJECTABLE;INTRAMUSCULAR, SUBCUTANEOUS | 019430-001 | Dec 22, 1987 | 8,048,035 | ⤷ Start Trial |
| Kaleo Inc | AUVI-Q | epinephrine | SOLUTION;INTRAMUSCULAR, SUBCUTANEOUS | 201739-002 | Aug 10, 2012 | 9,737,669 | ⤷ Start Trial |
| Kaleo Inc | AUVI-Q | epinephrine | SOLUTION;INTRAMUSCULAR, SUBCUTANEOUS | 201739-003 | Nov 17, 2017 | 7,731,686 | ⤷ Start Trial |
| Impax | TWINJECT | epinephrine | INJECTABLE;INTRAMUSCULAR, SUBCUTANEOUS | 020800-001 | May 30, 2003 | 7,621,891 | ⤷ Start Trial |
| Kaleo Inc | AUVI-Q | epinephrine | SOLUTION;INTRAMUSCULAR, SUBCUTANEOUS | 201739-002 | Aug 10, 2012 | 7,731,686 | ⤷ Start Trial |
| >Applicant | >Tradename | >Generic Name | >Dosage | >NDA | >Approval Date | >Patent No. | >Patent Expiration |
International Patents for epinephrine
| Country | Patent Number | Title | Estimated Expiration |
|---|---|---|---|
| Australia | 2016233682 | Epinephrine formulations | ⤷ Start Trial |
| Canada | 2978464 | FORMULATIONS D'EPINEPHRINE (EPINEPHRINE FORMULATIONS) | ⤷ Start Trial |
| China | 107614017 | 肾上腺素制剂 (EPINEPHRINE FORMULATIONS) | ⤷ Start Trial |
| European Patent Office | 3268045 | FORMULATIONS D'ÉPINÉPHRINE (EPINEPHRINE FORMULATIONS) | ⤷ Start Trial |
| Japan | 2018507915 | エピネフリン製剤 | ⤷ Start Trial |
| South Korea | 20180034307 | 에피네프린 제형 | ⤷ Start Trial |
| >Country | >Patent Number | >Title | >Estimated Expiration |
Supplementary Protection Certificates for epinephrine
| Patent Number | Supplementary Protection Certificate | SPC Country | SPC Expiration | SPC Description |
|---|---|---|---|---|
| 3678649 | 2025C/508 | Belgium | ⤷ Start Trial | PRODUCT NAME: COMBINATIE VAN EPINEPHRINE EN DODECYLMALTOSIDE, IN ALLE VORMEN BESCHERMD DOOR HET BASISOCTROOI; AUTHORISATION NUMBER AND DATE: EU/1/24/1846 20240823 |
| 3678649 | PA2025507 | Lithuania | ⤷ Start Trial | PRODUCT NAME: VISU FORMU EPINEFRINO IR DODECILMALTOZIDO DERINYS SAUGOMASPAGRINDINIO PATENTO; REGISTRATION NO/DATE: EU/1/24/1846 20240822 |
| 3678649 | 122025000010 | Germany | ⤷ Start Trial | PRODUCT NAME: KOMBINATION AUS EPINEPHRIN AND DODECYLMALTOSID, IN ALLEN DEM SCHUTZ DES GRUNDPATENTS UNTERLIEGENDEN FORMEN; REGISTRATION NO/DATE: EU/1/24/1846 20240822 |
| 3678649 | CA 2025 00007 | Denmark | ⤷ Start Trial | PRODUCT NAME: KOMBINATION AF EPINEPHRIN ELLER ET SALT DERAF, OG DODECYLMATOSID; REG. NO/DATE: EU/1/24/1846 20240823 |
| 3678649 | LUC00378 | Luxembourg | ⤷ Start Trial | PRODUCT NAME: COMBINAISON D'EPINEPHRINE ET DE DODECYLMALTOSIDE, SOUS TOUTES SES FORMES PROTEGEES PAR LE BREVET DE BASE; AUTHORISATION NUMBER AND DATE: EU/1/24/1846 20250211 |
| 3678649 | C20250011 | Finland | ⤷ Start Trial | |
| >Patent Number | >Supplementary Protection Certificate | >SPC Country | >SPC Expiration | >SPC Description |
Epinephrine Market Dynamics, Financial Trajectory, Patent Risk, and Competitive Outlook
More… ↓
Make Better Decisions: Try a trial or see plans & pricing
Drugs may be covered by multiple patents or regulatory protections. All trademarks and applicant names are the property of their respective owners or licensors. Although great care is taken in the proper and correct provision of this service, thinkBiotech LLC does not accept any responsibility for possible consequences of errors or omissions in the provided data. The data presented herein is for information purposes only. There is no warranty that the data contained herein is error free. We do not provide individual investment advice. This service is not registered with any financial regulatory agency. The information we publish is educational only and based on our opinions plus our models. By using DrugPatentWatch you acknowledge that we do not provide personalized recommendations or advice. thinkBiotech performs no independent verification of facts as provided by public sources nor are attempts made to provide legal or investing advice. Any reliance on data provided herein is done solely at the discretion of the user. Users of this service are advised to seek professional advice and independent confirmation before considering acting on any of the provided information. thinkBiotech LLC reserves the right to amend, extend or withdraw any part or all of the offered service without notice.
ISSN: 2162-2639

Privacy and Cookies
Terms & Conditions
Site Map
DrugPatentWatch Alternatives
LOE / Major Patent Expirations 2026 - 2027
NCE-1 Patent Challenge Dates 2026 - 2027
Friedman, Yali. "DrugPatentWatch" DrugPatentWatch, thinkBiotech, 2026, www.DrugPatentWatch.com.
See Primary Research Papers Citing DrugPatentWatch